
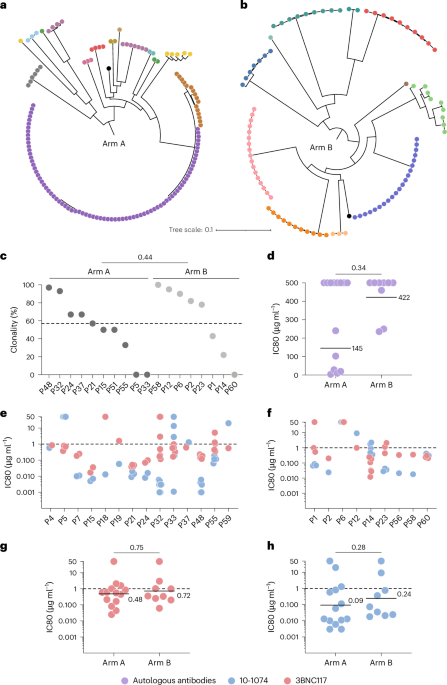
Published in Nature Medicine, findings from the phase 2 RIO trial reveal that adult males living with HIV who received broadly neutralizing antibodies 3BNC117-LS and 10-1074-LS experienced delayed viral rebound and prolonged suppression during an analytical treatment interruption.
The pursuit of HIV remission strategies that liberate patients from lifelong daily antiretroviral therapy (ART) has taken a measured step forward. Clinical researchers evaluating long-acting immunotherapeutic approaches face complex viral dynamics, particularly when patients temporarily halt standard medications under strict medical oversight.
Understanding the RIO Trial Design and Patient Demographics
The RIO study was structured as a double-blind, randomized, placebo-controlled phase 2 trial to assess whether specific long-acting broadly neutralizing antibodies (bNAbs)—namely 3BNC117-LS and 10-1074-LS—could maintain viral suppression. These agents target conserved regions on the HIV envelope glycoprotein, seeking to neutralize diverse viral strains. The trial enrolled 68 adult cisgender male participants aged 18 to 60 across study sites in the United Kingdom and Denmark. Eligible individuals had initiated ART during confirmed primary or early-stage HIV infection, maintained sustained viral suppression, harbored virus sensitive to 10-1074, and agreed to undergo an analytical treatment interruption (ATI).
In Plain English: The Clinical Takeaway
- Analytical Treatment Interruption (ATI): A clinical study design where patients under close medical monitoring safely pause their standard HIV medications to test whether an experimental treatment can control the virus alone.
- Broadly Neutralizing Antibodies (bNAbs): Specialized, lab-produced immune proteins that can latch onto and neutralize many different strains of HIV, acting as an extra layer of immune defense.
- Viral Rebound: The return of measurable HIV levels in the blood after ART has been stopped.
Secondary and Exploratory Outcomes of Broadly Neutralizing Antibodies
By week 20 of the trial, primary and secondary endpoints demonstrated a stark divergence between study arms. According to published data, only eight participants in the bNAb arm experienced study-defined viral rebound, compared with 30 participants in the saline placebo arm. This meant that 75 percent of participants receiving the antibody combination maintained viral suppression at week 20, contrasted with just 11 percent in the placebo group. Participants assigned to the bNAb arm experienced a 91 percent lower hazard of viral rebound than placebo recipients (HR 0.09, 95 percent CI 0.04-0.21; P<0.0001).
Furthermore, exploratory outcomes highlighted that initial reservoir sensitivity to autologous antibodies—meaning the patient’s own latent viral pool responding to immune pressures—correlated with a longer time to viral rebound. At the 20-week mark, 60 percent of the bNAb group maintained an undetectable viral load below 50 copies per mL, while 68 percent remained entirely off standard antiretroviral therapy. For participants who did experience viral rebound and restarted ART, all successfully reattained viral suppression, with 94 percent doing so within 12 weeks. No treatment-related serious adverse events were reported, though adverse events were common across both cohorts.
| Clinical Metric | bNAb Arm (n=34) | Placebo Arm (n=34) |
|---|---|---|
| Participants Without Viral Rebound | 75% | 11% |
| Undetectable Viral Load (<50 copies/mL) | 60% | 6% |
| Remaining Off ART at Week 20 | 68% | 15% |
| Reattained Suppression After Restarting ART | 100% | 100% |
Funding Transparency and Regulatory Context
While these findings offer encouraging mechanistic insights for immunologists, clinical experts emphasize that bNAbs are strictly investigational. As noted by clinical commentators, no patient will receive these experimental infusions in standard clinical practice in the immediate future; rather, the data shape the conceptual framework for next-generation HIV management.
Contraindications & When to Consult a Doctor
Analytical treatment interruptions carry inherent risks if not managed by specialized infectious disease physicians. Patients must never alter or discontinue prescribed antiretroviral regimens independently. Any sign of breakthrough symptoms, unexpected fatigue, or changes in well-being warrant immediate consultation with a primary care provider or treating infectious disease specialist.
The Path Ahead for HIV Remission Research
The RIO trial validates that combining long-acting bNAbs can successfully delay viral rebound during structured treatment interruptions. However, translating these phase II exploratory outcomes into accessible, widespread clinical therapies will require extensive longitudinal evaluation, larger and more diverse trial cohorts, and further refinement of viral resistance profiling. For now, daily or long-acting maintenance antiretroviral therapy remains the gold standard of care for achieving durable viral suppression and protecting immune health.
References
Disclaimer: This article is for informational purposes only and does not constitute medical advice, diagnosis, or treatment recommendations. Always consult a qualified healthcare professional regarding any questions about HIV management or therapeutic options.
- Youtuber Ralral’s Weight Loss and Hidden Obesity: Why Fat Loss Matters More Than the Scale
- Why Diets Fail: Nutrition as Fuel, Not Punishment
- Delaware Primary Election Results 2024: Senate And House Races (newsdirectory3.com)
- Ivonescimab Significantly Improves Overall Survival vs Pembrolizumab in First-Line PD-L1+ NSCLC: HARMONi-2 Results Released at WCLC 2026 (world-today-journal.com)
