
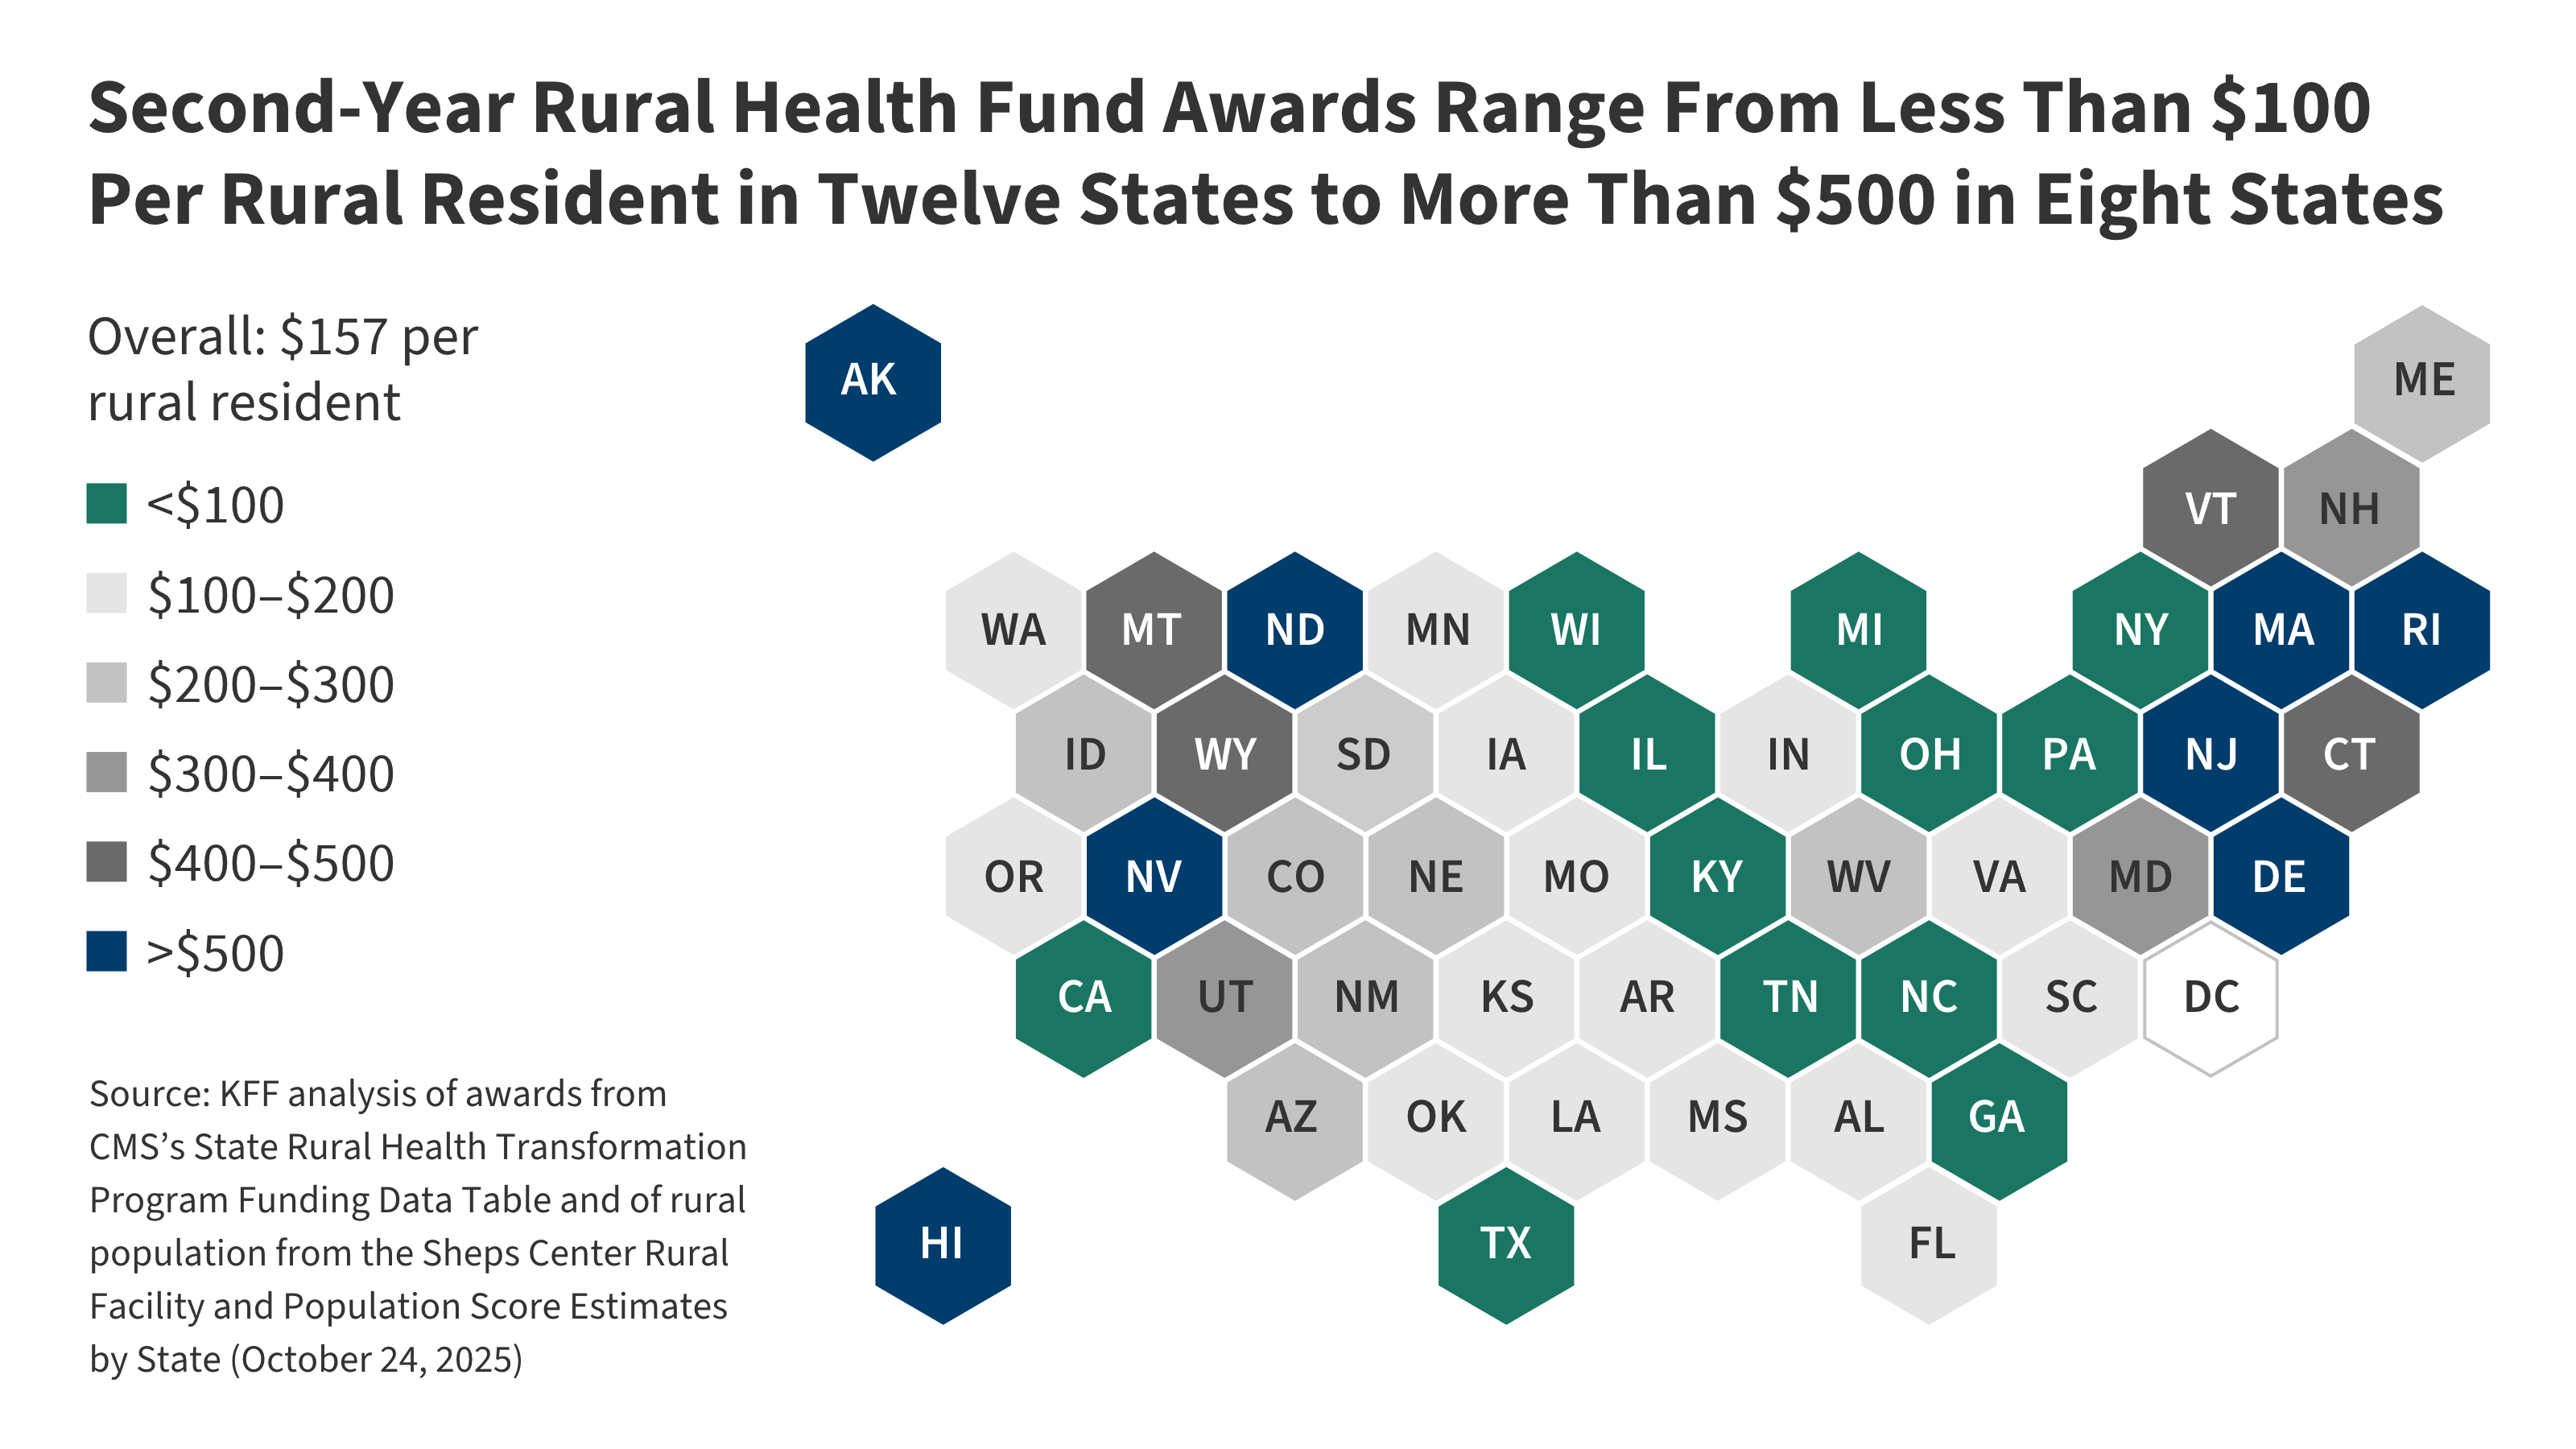
On November 9, 2026, the Centers for Medicare & Medicaid Services (CMS) distributed $10 billion in second-year grants under the $50 billion Rural Health Transformation Program.
While states received an average of $200 million, the funding per rural resident varies drastically—from under $100 in twelve states to over $500 in eight—due to statutory distribution mandates.
Clinical Intelligence for Rural Health Equity
- Fixed Allocation Constraints: By law, 50% of the $50 billion fund is divided equally among all 50 states, meaning rural population density does not dictate the majority of the funding, causing significant disparities in per-capita investment.
- Variable Need Metrics: Only 25% of the total fund is tied to specific measures of state need, such as the volume of rural facilities and Medicaid disproportionate share hospital (DSH) payments, which are vital for maintaining clinical safety nets in underserved regions.
- Delayed Transparency: While states have received their second-year awards, granular data on how these funds reach clinical providers—such as rural clinics or hospitals—will remain opaque until the first quarterly reports are submitted on November 29, 2026.
The Disparity in Federal Rural Funding
The Rural Health Transformation Program, established by the July 2025 budget reconciliation law, was designed to mitigate a projected $911 billion reduction in federal Medicaid spending over ten years. KFF analysis indicates that rural areas are expected to absorb $137 billion of that reduction. Despite these projections, the distribution of the $50 billion offset remains uneven.
Texas, which maintains the nation’s largest rural population at approximately 4.3 million, received $282 million in second-year funding. Conversely, New Jersey, with only 140,000 rural residents, received $142 million. This results in a stark per-resident funding gap: Texas receives roughly $70 per rural resident, while states like Rhode Island receive significantly higher amounts due to the flat-distribution requirement for half of the total fund.
| State | Rural Population (Approx.) | Total 2nd-Year Award | Approx. Award per Rural Resident |
|---|---|---|---|
| Texas | 4.3 million | $282 million | $70 |
| New Jersey | 140,000 | $142 million | $1,030 |
| Rhode Island | Smallest tier | Not specified | $6,390 |
Structural Barriers to Equitable Resource Allocation
The current funding mechanism is locked into a rigid structure. As reported by KFF, 75% of the fund is effectively non-discretionary: 50% is distributed equally across all states regardless of their rural health landscape, and 25% is tied to need metrics calculated once for the life of the program. Only the remaining 25% of the funding is contingent upon state-specific initiatives and policy progress.
This "one-size-fits-all" approach to the initial 50% allocation creates challenges for states with high rural disease burdens. According to clinical consensus, rural populations often face higher rates of chronic conditions such as diabetes and cardiovascular disease, necessitating strong primary care infrastructure.
Without a mechanism to scale funding to actual patient volumes or facility needs, the program may struggle to address the specific socioeconomic determinants of health in the most sparsely populated areas.
Fiscal Policy Effects Impact Patient Access to Care
While this funding program is a fiscal policy rather than a clinical intervention, its downstream effects impact patient access to care.
Limited Transparency Remains Until Quarterly Reports Arrive
The path toward full transparency remains limited. While CMS maintains that it will release state progress reports upon request, there is no mandate for proactive public disclosure. The data available through the CMS State Rural Health Transformation Program provides a baseline, but it does not account for how these dollars are obligated at the facility level.
Stakeholders await the November 29, 2026, deadline for the first round of quarterly reports, which will provide the first real-world look at how states are deploying their initial year of funding. Further insight into the efficacy of these investments—and whether they successfully mitigate the impacts of the 2025 reconciliation law—will not be fully clear until late 2027.
