
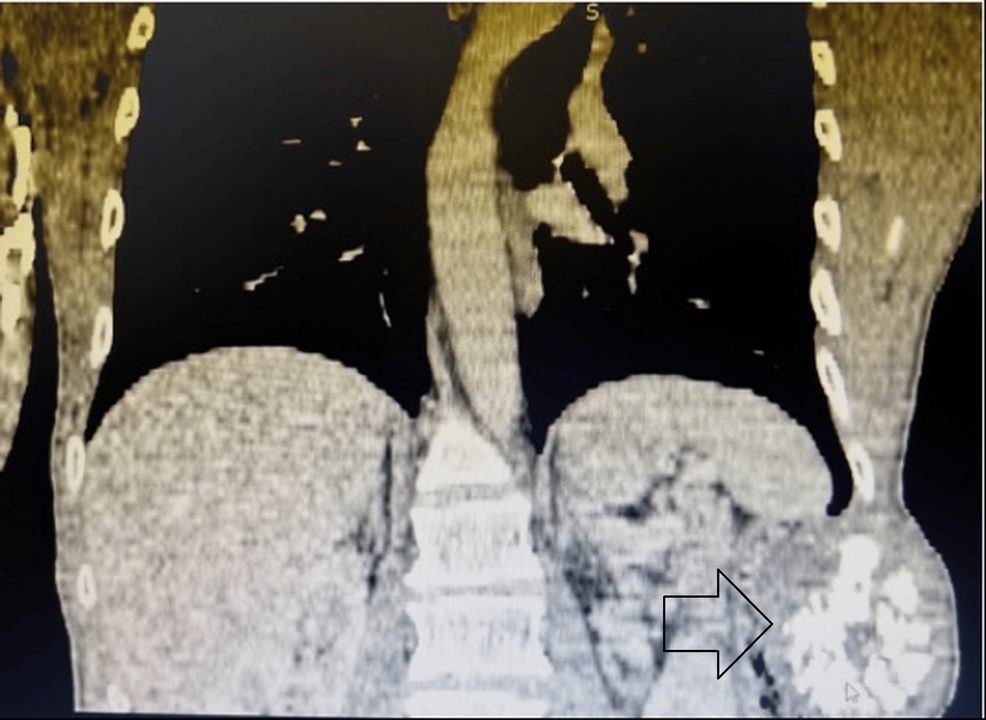
Chest wall chondrosarcoma is an uncommon primary malignant bone tumor managed through surgical resection and rigid skeletal reconstruction, as demonstrated in recent clinical reports examining titanium fixation systems and synthetic meshes for complex thoracic wall defects.
Surgical management of chest wall tumors requires balancing complete oncological clearance with the preservation of respiratory mechanics. When tumors invade costal margins and adjacent soft tissues, extensive defects demand durable stabilization to protect intrathoracic organs and prevent paradoxical chest wall motion.
In Plain English: The Clinical Takeaway
- Oncological Clearance: Surgeons aim for wide negative margins to prevent local disease recurrence, as chondrosarcomas show limited response to chemotherapy and radiation.
- Skeletal Reconstruction: Advanced titanium rib fixation systems, such as the STRATOS system, restore structural stability and protect intrathoracic organs following multi-rib resection.
- Multidisciplinary Planning: Comprehensive imaging and coordinated team evaluations guide the extent of en bloc resection and subsequent soft-tissue repair.
Titanium Bars and Mesh Stabilize Thoracic Wall Defects
Extensive resections of the thoracic wall compromise respiratory mechanics. Cureus reported the case of a 62-year-old man with a grade 1 chondrosarcoma involving the left tenth and eleventh ribs, managed via posterolateral thoracotomy and an approximate 1-cm gross surgical margin.
Rigid skeletal stabilization of the resulting 11-12 cm by 8 cm defect was achieved using two 12-cm titanium bars from the Strasbourg Thoracic Osteosyntheses System, secured with three costal clips to the adjacent ribs, alongside a reinforcing polypropylene mesh.
A parallel surgical video presented by Parsa Radfar, Andrei Gritsiuta, Margaux Marinelli, and Roman Petrov from the University of Texas Medical Branch demonstrated a similar approach for a left lateral chest wall chondrosarcoma involving the costal margin.
As detailed in abstracts published on ECTSS, their procedure utilized wide en bloc resection of the involved ribs, diaphragm, and external oblique muscle, followed by rigid STRATOS titanium rib fixation. This technique achieved a complete R0 resection while minimizing paradoxical chest wall motion and preserving pulmonary function.
Pathological Findings and Clinical Outcomes
Histopathological examination remains critical for establishing definitive diagnoses in primary thoracic malignancies. Cureus reported that the surgical specimen measured 10 by 9.5 by 5.8 cm, revealing a mitotic rate of 9 mitoses/mm² and positive surgical margins classified as pT2 NX MX. Positive margins showed difficulty in achieving local disease control, even when patients recovered well and were discharged on postoperative day three.
In a separate report from the Caribbean published on PMC, clinicians managed a grade 2 conventional chondrosarcoma arising from the third rib in a 61-year-old female. That case utilized a single-stage procedure involving wide en-bloc resection, polypropylene mesh reconstruction, and a latissimus dorsi muscle flap.
The patient achieved good cosmesis and pulmonary function without recurrence at a three-year follow-up, emphasizing the value of multidisciplinary team discussions in managing delayed diagnoses and complex thoracic presentations.
| Case Parameter | Cureus Case Report | PMC Caribbean Case Report |
|---|---|---|
| Patient Age and Sex | 62-year-old man | 61-year-old female |
| Tumor Location | Left 10th and 11th ribs | Right 3rd rib |
| Histological Grade | Grade 1 chondrosarcoma | Grade 2 chondrosarcoma |
| Reconstructive Material | STRATOS titanium system and polypropylene mesh | Polypropylene mesh and latissimus dorsi flap |
Imaging and Surgical Risks Require Multidisciplinary Coordination
Advanced imaging, including computed tomography and magnetic resonance imaging, is essential to differentiate benign cartilaginous tumors from malignant chondrosarcomas. Surgical resection and rigid reconstruction carry inherent risks, including pulmonary complications, wound infection, and local recurrence if surgical margins are positive. Adjuvant radiotherapy may be indicated when positive margins are identified, though treatment plans require careful coordination by a multidisciplinary oncology team.
Long-term clinical follow-up is necessary for all patients undergoing thoracic wall resection and reconstruction to monitor for local recurrence and assess long-term respiratory mechanics.
References
- Cureus: Chest Wall Chondrosarcoma: Surgical Resection and Reconstruction Using the Strasbourg Thoracic Osteosyntheses System (STRATOS) and Polypropylene Mesh: A Case Report
- ECTSS: En Bloc Resection of Giant Chest Wall Chondrosarcoma with STRATOS Reconstruction (Parsa Radfar, Andrei Gritsiuta, Margaux Marinelli, Roman Petrov)
- PMC: Case report on the approach to surgical management for a chest wall chondrosarcoma
