
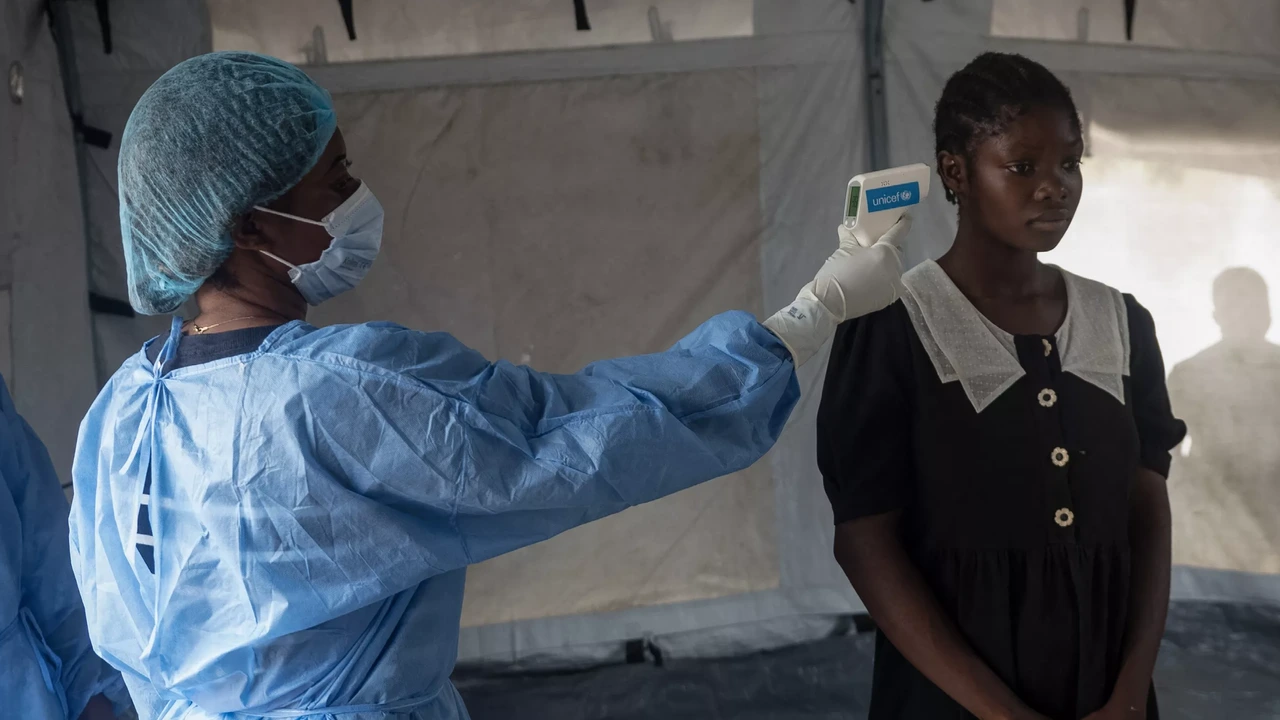
The death toll from the ongoing ebola outbreak in the Democratic Republic of Congo has surpassed 5,000, with over 10,000 confirmed cases recorded since May. This escalation marks the second-deadliest ebola epidemic in recorded history, trailing only the 2014–2016 West Africa outbreak.
In Plain English: The Clinical Takeaway
- Transmission Vectors: The virus spreads primarily through direct contact with infected bodily fluids, including blood, saliva, vomit, and sweat.
- The Bundibugyo Strain: This specific outbreak is driven by the Bundibugyo variant, an ebola species for which no approved treatment or vaccine exists.
- Monitoring Gaps: Approximately 80% of new patient transmissions occur outside of tracked contact tracing chains, complicating containment efforts.
Epidemiological Trajectory and the High Plateau
Health data indicates that while total confirmed cases have reached 10,351 with 5,026 fatalities—yielding a case fatality rate of nearly 50 percent—the weekly trajectory has stabilized. Infections have maintained a steady rate of 400 to 500 new cases weekly over recent weeks. Physician-researcher Boghuma Titanji described this metric to the Associated Press as a “high plateau” that remains deeply concerning because numbers are failing to decline.

The vast majority of these cases and fatalities are concentrated in the eastern provinces of Ituri and North Kivu. Compounding the clinical challenge, contact-tracing metrics reveal that only one-quarter of new patients are identified through active monitoring of known contacts, leaving the vast majority of viral transmission chains unmapped by public health workers on the ground.
Regional Spread and International Border Restrictions
The geographic footprint of the virus has expanded beyond the borders of the Democratic Republic of Congo. Infections have been documented in Uganda, Kenya, and Nigeria, with Nigeria confirming its first case on October 20. In response to the cross-border transmission risks, the United States government announced travel restrictions taking effect on November 3, barring entry to travelers who have been in Congo within the preceding 21 days.
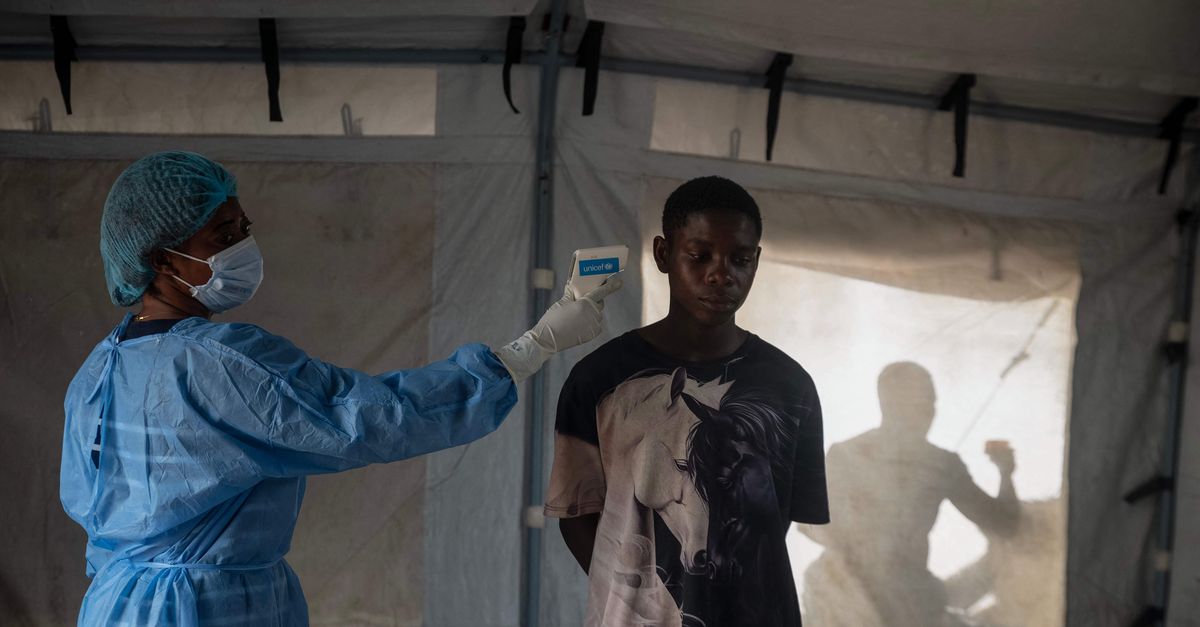
Public health interventions continue to face severe logistical hurdles. The Africa Centers for Disease Control and Prevention (Africa CDC), led by Director Jean Kaseya, stated on October 29 that containment teams are “not winning so far,” hampered by regional conflicts, compromised healthcare infrastructure, and widespread community distrust, alongside international aid funding cuts.
| Outbreak Parameter | Current Epidemic (DRC) | Historical Comparison (2014–2016) |
|---|---|---|
| Affected Regions | DRC (Ituri, North Kivu), Uganda, Kenya, Nigeria | Guinea, Liberia, Sierra Leone |
| Total Confirmed Cases | 10,351 | 28,600 |
| Total Fatalities | 5,026 | Over 11,000 |
| Viral Strain | Bundibugyo-variant | Not specified |
Clinical Trials and Therapeutic Interventions
Therapeutically, the absence of approved countermeasures for the Bundibugyo variant has prompted accelerated clinical evaluations. On October 23, clinical trials commenced in Bunia to test whether the Ervebo vaccine—which is approved for the Zaïre-variant—provides cross-protection against the Bundibugyo strain. Additional vaccine candidates developed by Oxford and Moderna are slated for upcoming trials.
Funding requests to support comprehensive epidemic containment reached 1.1 billion US dollars through United Nations appeals issued in late August. Meanwhile, the European Centre for Disease Prevention and Control (ECDC) reported 10,274 cumulative cases and 4,992 deaths as of October 29.
Contraindications & When to Consult a Doctor
Early clinical manifestations of ebola virus disease include sudden-onset fever, severe fatigue, muscular pain, headache, and sore throat, rapidly progressing to vomiting, diarrhea, impaired kidney and liver function, and in some cases, internal and external bleeding.
Anyone developing these symptoms after potential exposure must immediately isolate and contact public health authorities or specialized medical facilities. Do not visit standard outpatient waiting rooms without prior notification, as specialized infection control protocols and personal protective equipment (PPE) are mandatory to prevent nosocomial (hospital-acquired) transmission.
References
- NOS Nieuws
- NRC Nieuws
- TPO.NL
