
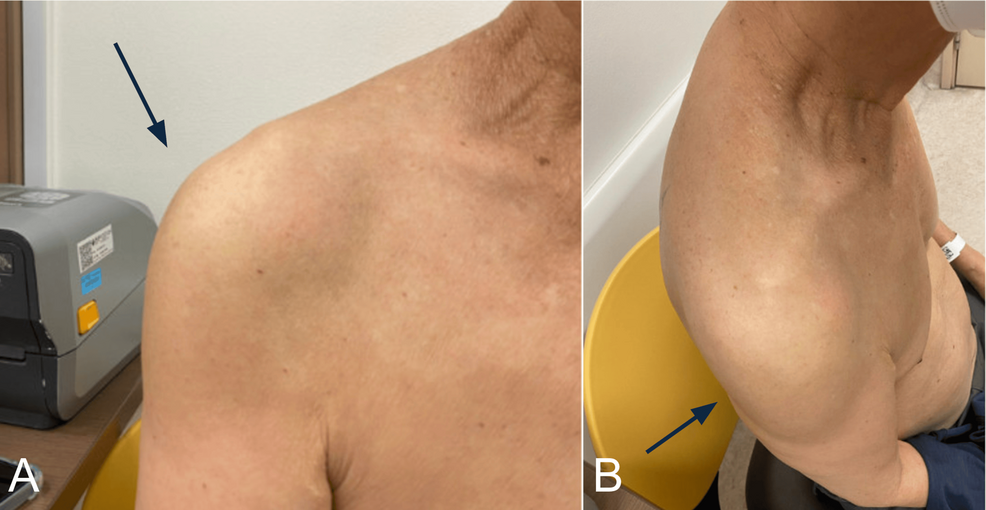
A seventy-year-old male developed severe shoulder inflammation following a pneumococcal polysaccharide vaccine deltoid injection, presenting a rare clinical diagnostic challenge as reported by Cureus.
The case highlights an acute inflammatory response mimicking bacterial infection, which medical professionals categorize as pseudoseptic arthritis. Unlike standard vaccine reactions, this condition involves intra-articular inflammation requiring careful surgical intervention and long-term orthopedic follow-up.
Pseudoseptic Arthritis and Rotator Cuff Complications Affect Recovery
- Pseudoseptic Arthritis: A severe, sterile joint inflammation that looks and feels like a bacterial infection but yields no microorganisms on testing.
- Rotator Cuff Complication: Pre-existing or concurrent tendon tears can create a pathway for inflammation to spread from the shoulder bursa directly into the main joint capsule.
- Long-Term Recovery: While initial inflammatory markers normalize quickly after surgical washouts, severe structural tendon damage may eventually necessitate advanced procedures like reverse shoulder arthroplasty.
Severe Shoulder Pain Follows Pneumococcal Vaccine Injection
The patient presented to the emergency department with a five-day history of severe right shoulder pain, swelling, and restricted movement that began one day after receiving a pneumococcal polysaccharide vaccine injection in his right deltoid. He remained afebrile, yet laboratory investigations revealed a white blood cell count of 23.24 × 10⁹/L, a C-reactive protein level of 112.1 mg/L, and an erythrocyte sedimentation rate of 70 mm/hr, according to Cureus.
Initial medical management involved a provisional diagnosis of cellulitis and septic arthritis, prompting empirical intravenous Augmentin administration. Diagnostic imaging via contrast-enhanced magnetic resonance imaging demonstrated deltoid myositis, long head of the biceps tenosynovitis, subacromial-subdeltoid bursitis, and a high-grade bursal-sided tear of the supraspinatus footprint.
Because initial blood cultures were negative and no fluid collection was easily targetable for arthrocentesis, clinicians considered a complex differential diagnosis that included crystal arthropathy and acute structural rotator cuff pathology.
Surgical Intervention and Histopathological Findings
Clinical deterioration on the fifth day, marked by a C-reactive protein rebound to 257.5 mg/L, led to an urgent open arthrotomy and washout via a deltopectoral approach on day six. Exploration revealed a friable inflammatory soft-tissue mass occupying both the subdeltoid space and the glenohumeral joint, with the supraspinatus defect acting as a direct communication channel between the two compartments.
Intraoperative tissue and fluid cultures yielded no aerobic or anaerobic growth. Histopathological examination confirmed non-specific chronic inflammation, granulation tissue, and fibrinoid debris without malignancy or acute purulent infection, establishing a diagnosis of probable pseudoseptic arthritis. Following surgical debridement, the patient’s pain improved and inflammatory markers declined, allowing for discharge on day thirteen without further antibiotics.
| Clinical Parameter | Initial Presentation | Post-Washout (Day 13) | Four-Week Follow-Up |
|---|---|---|---|
| C-Reactive Protein | 112.1 mg/L | 43.8 mg/L | 2.6 mg/L |
| Active Flexion Range | 90° | Limited | 0° (Pseudoparalysis) |
Progression to Structural Tendon Failure and Final Reconstruction
Although the inflammatory reaction resolved successfully, the patient developed severe functional pseudoparalysis at his four-week outpatient follow-up. Subsequent magnetic resonance imaging at three months demonstrated progression to a complete, retracted full-thickness tear of the subscapularis tendon alongside a full-thickness tear of the supraspinatus tendon. This cascade of structural failures required arthroscopic rotator cuff repair at four months.
Nine months post-repair, persistent limited active range of motion and an ultrasound-confirmed supraspinatus retear prompted a revision strategy. The patient underwent a reverse shoulder arthroplasty. Two months following the reverse arthroplasty, active forward flexion and abduction improved dramatically to 170° and 175°, respectively, as detailed in the Cureus report.
Consult a Doctor for Severe Joint Pain or Swelling
Immediate medical consultation is warranted if an individual experiences acute, severe joint pain, rapid swelling, or systemic inflammatory symptoms following any vaccination or soft-tissue procedure.
References
- Cureus: Pseudoseptic Arthritis of the Shoulder Following Pneumococcal Polysaccharide Vaccine Injection to the Deltoid: A Case Report.
- PubMed Central (PMC): Onset of Frozen Shoulder Following Pneumococcal and Influenza Vaccinations.
- National Institutes of Health (NIH): National Library of Medicine Biomedical Literature Archive.
