
A 51-year-old woman experienced six hospital admissions over ten months for recurrent fever, confusion, and muscle rigidity before clinicians diagnosed probable neuroleptic malignant syndrome linked to promazine toxicity, Cureus reported following presentation data shared at the Society for Acute Medicine Glasgow conference.
In Plain English: The Clinical Takeaway
- Neuroleptic Malignant Syndrome (NMS): A rare, life-threatening reaction to dopamine-blocking medications like antipsychotics that causes severe high fever, rigid muscles, and altered mental status.
- Diagnostic Masking: Working in healthcare can unintentionally alter how clinicians take patient histories, occasionally contributing to delayed recognition of medication toxicity.
Ten Months and Six Hospital Admissions Before Diagnosis
The patient presented to the emergency department with a one-day history of fever reaching 39.4°C, a heart rate of 126 beats per minute, and blood pressure reading 163/68 mmHg. Her prescribed regimen included promazine 50 milligrams three times daily, amitriptyline 75 milligrams at night, diazepam, paracetamol, codeine, and asthma inhalers. Although she normally worked in healthcare, she had been away from employment for several months due to severe physical and mental health difficulties. Initial blood work demonstrated a mildly raised C-reactive protein concentration of 21.5 milligrams per liter and a creatine kinase level of 832 units per liter measured 24 hours after admission. Empirical antibiotics were started for presumed sepsis before reviewing her historical pharmacy records.
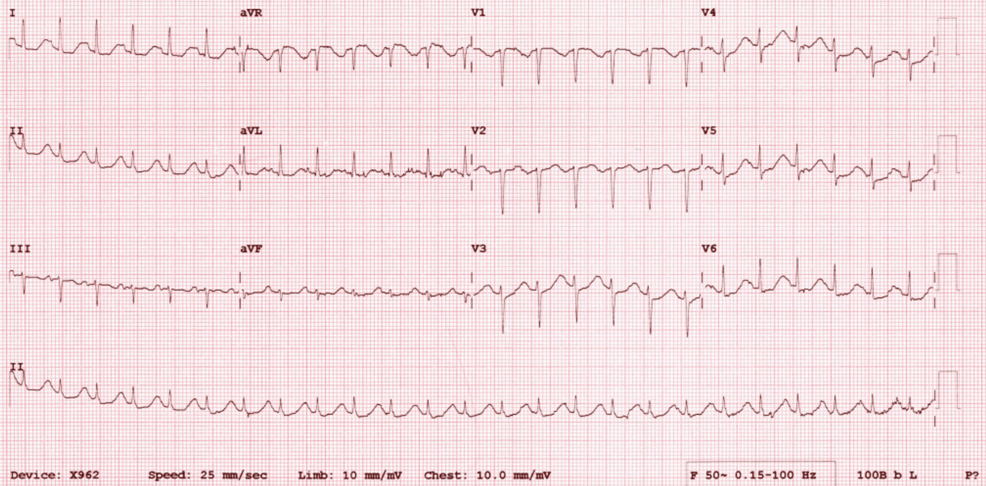
Reviewing her medical background uncovered six distinct hospital presentations across approximately ten months without a unifying diagnosis. Her most severe admission occurred roughly six months prior, featuring extreme agitation, vomiting, muscle rigidity, a temperature exceeding 40°C, and tachycardia at 164 beats per minute. An electrocardiogram revealed sinus tachycardia at 151 beats per minute with a Fridericia-corrected QT interval of 490 milliseconds. That severe episode included a creatine kinase surge to 7,272 units per liter, a white cell count of 24.9 times 10 to the ninth power per liter, and lactate at 5.1 millimoles per liter. She required intensive care admission, vasopressor support, and approximately 10 liters of intravenous fluid replacement within the first 24 hours.
Rule Out Infectious and Autoimmune Etiologies During Evaluations
Extensive evaluations during the earlier severe admission ruled out infectious and autoimmune etiologies. Cerebrospinal fluid analysis showed clear appearance, normal white cell count, negative cultures, and negative viral and bacterial polymerase chain reaction panels for herpes simplex types 1 and 2, varicella zoster, enterovirus, parechovirus, Neisseria meningitidis, and Streptococcus pneumoniae. Autoimmune screens, including antinuclear antibodies, anti-myeloperoxidase, and anti-proteinase 3 antibodies, returned negative results. Free thyroxine was elevated at 23.4 picomoles per liter with a normal thyroid-stimulating hormone of 0.98 milliunits per liter.
| Clinical Parameter | Most Recent Admission | Earlier Severe Admission |
|---|---|---|
| Peak Temperature (°C) | 39.4 | >40.0 |
| Heart Rate (beats/min) | 126 | 164 |
| Creatine Kinase (U/L) | 832 (Day +1) | 7272 (Admission) |
| White Cell Count (×10⁹/L) | 9.5 | 24.9 |
| C-Reactive Protein (mg/L) | 21.5 | 1.9 |
Pharmacy records during the final admission showed that a six-month supply of promazine had been approved and dispensed within the preceding three months. This dispensing pattern supported increased access to the medication, although the exact quantity ingested remained unverified. A non-judgmental clinical discussion regarding additional preparations for sleep and neuropathic pain brought possible medication toxicity into focus. The clinical team established a working diagnosis of probable promazine-associated neuroleptic malignant syndrome compounded by possible concomitant amitriptyline toxicity. Promazine was discontinued three days after admission, leading to symptom resolution.
Examine Medication Reconciliations for Unexplained Systemic Symptoms
Clinicians must perform thorough medication reconciliations and examine dispensing data when recurrent, unexplained systemic symptoms arise in individuals prescribed psychotropic agents.
Sustained Recovery After Medication Withdrawal
Following the discontinuation of promazine, the patient showed rapid clinical improvement, mirroring her recovery trajectories from prior admissions. At a follow-up assessment conducted approximately six months later, she remained off promazine entirely. She reported sustained symptom resolution and experienced zero further hospital attendances during the monitoring period.
References
- Stetefeld H, et al. The Lancet Neurology.
- Gelenberg AJ, et al.
- WHO Guidelines.
