
Sodium-glucose cotransporter 2 (SGLT2) inhibitors, widely used to treat chronic kidney disease and heart failure, are currently not recommended for patients with Autosomal Dominant Polycystic Kidney Disease (ADPKD).
Clinical Care for ADPKD Patients
- No current recommendation: Leading health guidelines, including the 2025 Kidney Disease: Improving Global Outcomes (KDIGO) standards, advise against using SGLT2 inhibitors for ADPKD patients until safety is established.
- Mechanistic uncertainty: SGLT2 inhibitors induce osmotic diuresis, which may trigger a compensatory rise in vasopressin—a hormone known to accelerate cyst growth in polycystic kidneys.
- Conflicting evidence: Recent meta-analyses have reached differing conclusions regarding whether these drugs significantly slow the decline of estimated glomerular filtration rate (eGFR) in this specific patient population.
Conflicting Data on Renal Function and Cyst Growth
The role of SGLT2 inhibitors in ADPKD has become a subject of academic debate as evidence from observational cohorts, case series, and meta-analyses has accumulated. A review highlights that while these medications have transformed care for other forms of chronic kidney disease, their application in ADPKD is complicated by the disease’s unique pathophysiology. The primary concern is that by blocking glucose reabsorption in the proximal tubule, these drugs may inadvertently drive the very hormonal signaling pathways that expand kidney cysts.
The evidence base is currently fragmented. A meta-analysis by Tantush et al. reported a slower eGFR decline, yet the vast majority of the 3,180 patients included were actually diabetics from a single US cohort, not typical ADPKD patients. Conversely, a meta-analysis by Kanbay et al. published in 2026 evaluated 451 patients and found no significant difference in eGFR decline compared to those not taking SGLT2 inhibitors, nor any impact on total kidney volume. The current body of evidence is limited by small sample sizes and a high prevalence of observational designs rather than randomized controlled trials.

Mechanistic Risks in the Nephron
Most ADPKD cysts arise from the distal nephron and collecting duct, whereas SGLT2 inhibitors act on the proximal tubule. Research indicates that SGLT2 inhibition can increase levels of copeptin—a stable marker for vasopressin—in patients with heart failure and non-diabetic kidney disease. Because vasopressin is the primary hormonal driver of cyst growth, there is a theoretical risk that these drugs could counteract the therapeutic goals of current treatments like tolvaptan, which is specifically designed to block vasopressin receptors.
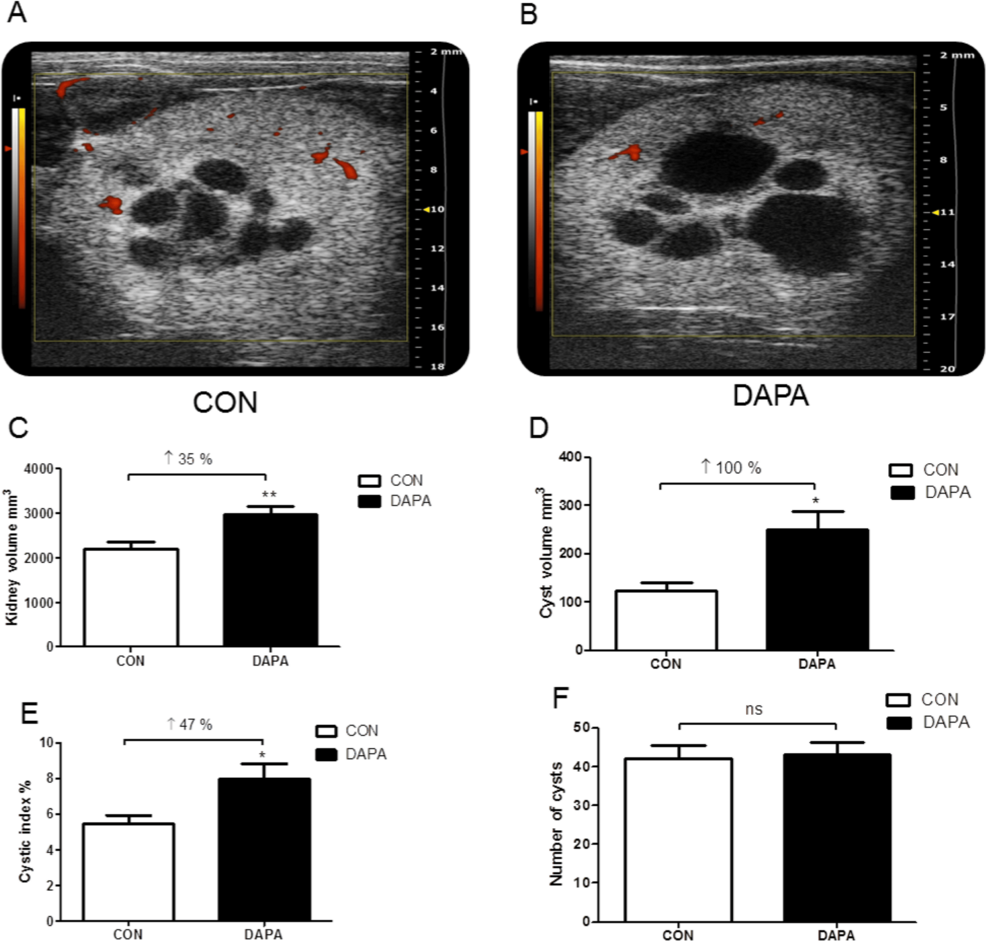
Animal models have provided inconsistent results, further clouding the clinical picture.
| Study/Analysis | Patient N | Key Finding |
|---|---|---|
| Tantush et al. (2026) | 3,180 | Reported slower eGFR decline; heavily weighted by diabetic cohort. |
| Kanbay et al. (2026) | 451 | No significant difference in eGFR vs. control; no change in kidney volume. |
| Kapoor et al. (Preclinical) | N/A | Observed increased cyst volume in PCK rat models. |
Clinical Trials Test SGLT2 Inhibitors for ADPKD
The path forward requires rigorous, stratified clinical trials that account for genotype, disease stage, and the use of existing therapies like tolvaptan. As of November 2026, there are four registered trials investigating the use of SGLT2 inhibitors in ADPKD. Until these trials produce definitive, peer-reviewed results, the consensus among global health authorities remains that the use of these agents in ADPKD should be restricted to strictly controlled experimental settings or cases where the cardiovascular benefits for a specific patient clearly outweigh the unknown renal risks.
Always seek the advice of your physician or other qualified health provider with any questions regarding a medical condition.
