
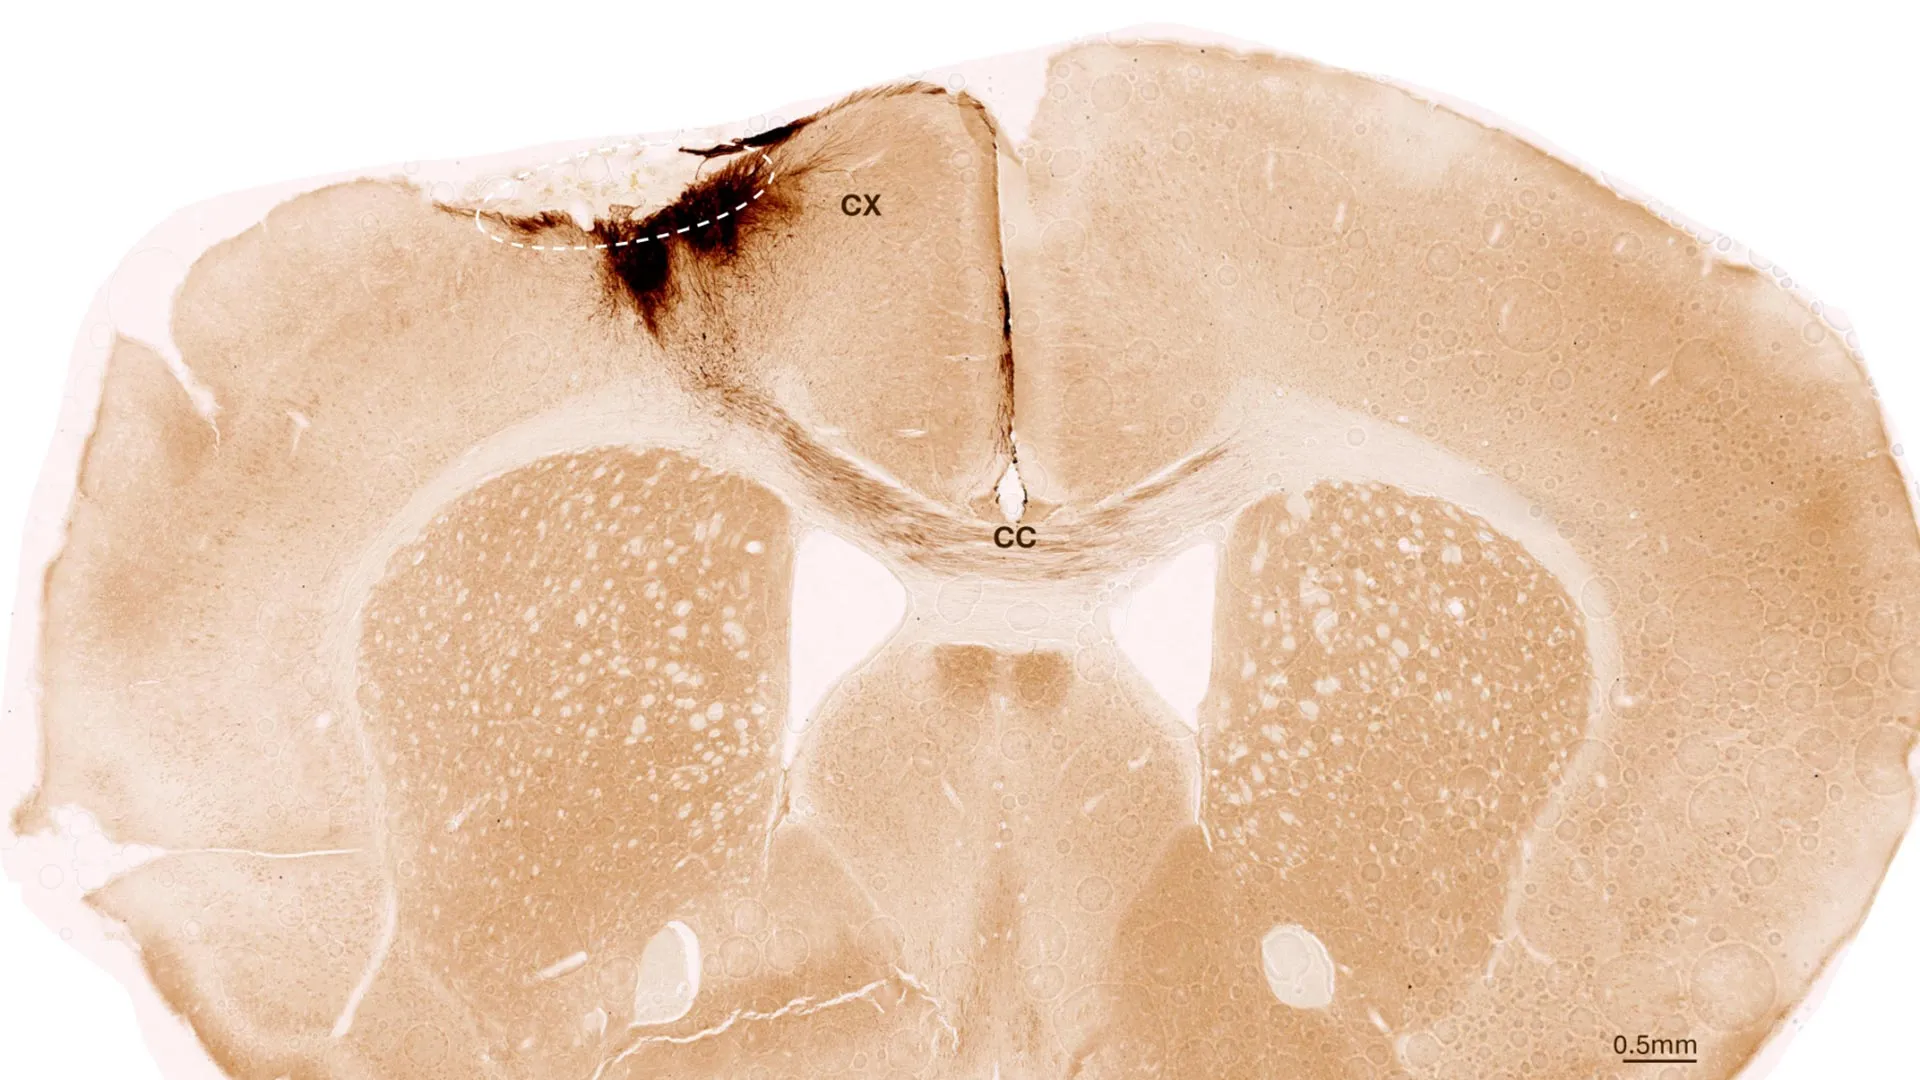
Stem cell transplants successfully regenerated stroke-damaged brain tissue and restored lost motor function in mouse models, according to collaborative research from the University of Zurich and the University of Southern California. The therapy generated new neurons, improved blood vessels, and stabilized the blood-brain barrier.
According to the World Health Organization, roughly 15 million people suffer a stroke annually worldwide. Five million of those individuals die, and another five million sustain permanent disability. Permanent deficits such as aphasia, cognitive impairment, and hemiplegia are traditionally viewed as irreversible. A new collaborative research initiative led by the University of Zurich (UZH) Institute for Regenerative Medicine challenges this paradigm by demonstrating biological repair in ischemic stroke models.
Cellular Mechanisms of Neural Stem Cell Transplantation
The research initiative, spearheaded by Christian Tackenberg, scientific head of the neurodegeneration group at UZH, and postdoctoral researcher Rebecca Weber, focused on the regenerative capacity of neural stem cells. Working alongside Ruslan Rust from the University of Southern California, the team utilized induced pluripotent stem cells (iPSCs). These versatile cells are manufactured by reprogramming mature somatic cells, such as human skin cells, back into an embryonic-like state. This reprogramming strategy holds long-term potential for creating patient-specific grafts that could theoretically minimize immune rejection risks, though the mouse subjects in this study required genetic modification to accept the human-derived tissue.
Researchers induced permanent ischemic strokes in the mice to replicate the oxygen deprivation and cellular necrosis seen in human patients. One week following the stroke induction, the team transplanted the human neural stem cells directly into the peri-infarct area, which is the zone surrounding the primary injury site. Through longitudinal imaging and biochemical analysis, the team tracked the grafts over a five-week evaluation period. The cells survived, integrated into the existing neural architecture, and formed functional synapses with endogenous neurons. Tackenberg noted, “Our findings show that neural stem cells not only form new neurons, but also induce other regeneration processes.”
Systemic Healing and Motor Function Restoration
Beyond replacing lost cells, the transplantation triggered a broader systemic healing cascade that stabilized the microenvironment of the damaged brain. Histological and biochemical assays revealed three major physiological improvements:
- Angiogenesis: The formation of new blood vessels within the injured parenchyma, enhancing oxygen and nutrient delivery.
- Inflammatory Modulation: A measurable dampening of the chronic, neurotoxic inflammatory cascade that typically worsens secondary tissue injury.
- Blood-Brain Barrier Integrity: Restoration of the vital vascular boundary, preventing harmful blood-borne molecules from entering the central nervous system and causing further edema.
To measure functional outcomes, the researchers utilized AI-assisted gait analysis. The evaluation confirmed that the cellular grafts successfully reversed motor coordination deficits caused by the ischemic event. Furthermore, testing established that transplanting the stem cells one week post-stroke yielded better results than immediate transplantation, a timeline that could ease clinical preparation protocols if translated to human medicine.
In Plain English: The Clinical Takeaway
- What was done: Researchers transplanted lab-grown human stem cells into the brains of mice one week after an induced stroke.
- What happened: The stem cells did not just survive; they turned into working neurons, helped build new blood vessels, lowered damaging inflammation, and repaired the barrier protecting the brain.
- Why it matters: This discovery offers a foundational proof-of-concept that brain damage once thought permanent might eventually be repaired, though extensive human clinical trials remain required.
Evaluating Pre-Clinical Stroke Interventions
| Parameter | Standard Acute Intervention | Experimental UZH Stem Cell Approach |
|---|---|---|
| Primary Mechanism | Thrombolysis or mechanical clot retrieval | Neuronal replacement, angiogenesis, and anti-inflammatory modulation |
| Intervention Window | Hours post-stroke (acute phase) | One week post-stroke (sub-acute recovery phase) |
| Target Endpoint | Tissue preservation and survival | Tissue regeneration and motor function reversal |
Contraindications & When to Consult a Doctor
Future Directions and Safety Protocols
Translating these findings from murine models to human clinical trials requires overcoming significant scientific hurdles. Tackenberg emphasized that ongoing work focuses on minimizing risks and refining delivery methods. The research team is currently developing a biological safety switch mechanism designed to prevent uncontrolled cellular proliferation or tumor formation within the brain. Additionally, investigators are exploring endovascular injection techniques—delivering cells through blood vessels rather than direct brain surgery—to make any eventual human therapy safer and more clinically practicable.
References

- World Health Organization (WHO). Stroke, Cerebrovascular accident fact sheets and global disability metrics.
- University of Zurich (UZH) Institute for Regenerative Medicine. Research publications on induced pluripotent stem cells and neural regeneration in stroke models, led by Christian Tackenberg and Rebecca Weber.
- University of Southern California. Collaborative studies on neural stem cell integration and functional motor recovery in ischemic stroke models, featuring Ruslan Rust.
- Center for iPS Cell Research and Application (CiRA), Kyoto University. Protocol development for animal-reagent-free human stem cell manufacturing.
