
Navigating knee pain relief in the “Sibley approach” requires a clinical approach that prioritizes joint preservation over temporary masking agents. According to comprehensive medical guides, accurate diagnosis relies on physical examinations checking swelling, tenderness, and range of motion, supplemented by imaging modalities like X-rays, MRIs, and CT scans when initial clinical evaluations remain inconclusive.
The Bottom Line
- Diagnostic Precision: Clinicians evaluate structural integrity through physical manipulation before ordering imaging like MRIs for soft tissues or X-rays for bone health.
- Protocol Hierarchy: Conservative management—including the RICE method (Rest, Ice, Compression, Elevation)—remains the baseline standard for sprains, overuse injuries, and mild meniscus tears.
- Surgical Intervention: Operations are usually a last resort for severe knee problems or advanced deterioration of the joint, such as complete ACL tears.
Diagnostic Frameworks and Clinical Imaging Protocols
When patients present with acute or chronic joint discomfort, healthcare providers initiate a rigorous physical assessment. Practitioners evaluate the knee for localized warmth, effusion, and tenderness. They test the joint’s mechanical limits by assessing the range of motion and applying stress to internal structures.
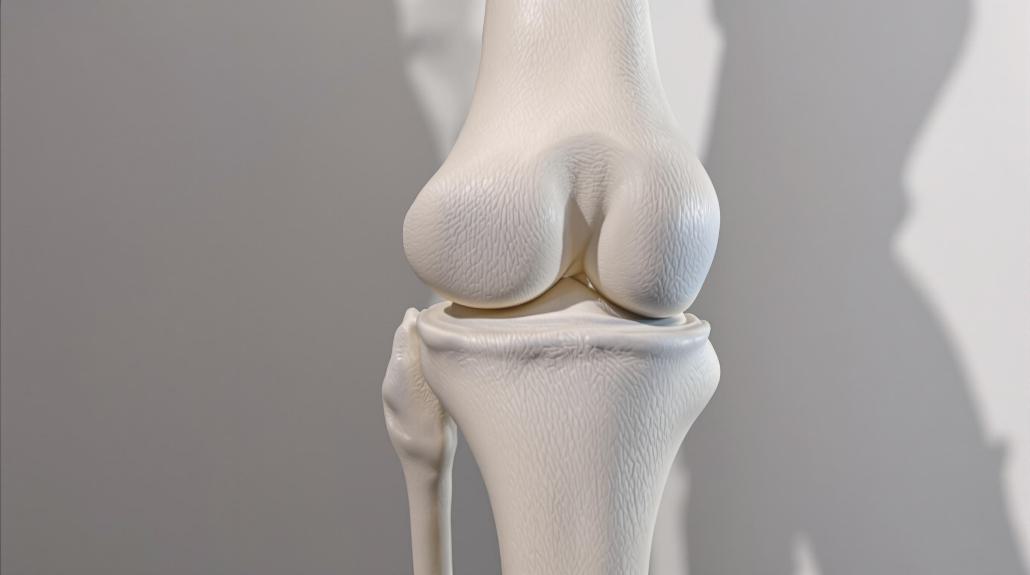
Imaging studies are deployed strategically. X-rays offer an initial view of the skeletal components—the femur, tibia, and patella—highlighting arthritic degradation or bone fractures. When soft tissue damage is suspected, physicians utilize magnetic resonance imaging (MRI) to detect torn ligaments, damaged cartilage, or bone fractures. Computed tomography (CT) scans deliver detailed cross-sectional internal views without making an incision.
Pathology Breakdown: From Sprains to Structural Failures
Knee pathology spans a wide spectrum of severity, demanding targeted intervention strategies. Ligamentous injuries, particularly anterior cruciate ligament (ACL) tears, compromise joint stability. While minor tears may respond to non-surgical rehabilitation, complete tears won’t heal without surgery.
Overuse injuries—including runner’s knee, iliotibial (IT) band syndrome, and patellar tendinitis—stem from repetitive mechanical stress. Similarly, meniscus tears caused by sudden twisting motions under load often heal through conservative protocols like RICE, provided the structural damage remains minor. However, if conservative treatment does not work, it will require surgery.
| Condition | Primary Mechanism | First-Line Treatment |
|---|---|---|
| Knee Sprains | Ligament overstretching/twisting | RICE (Rest, Ice, Compression, Elevation) |
| Osteoarthritis | Wear and tear | Weight management, physical therapy, medication |
| Complete ACL Tear | Tearing of the ACL ligament | Surgery |
| Meniscus Tear | Rotation under weight load | Conservative rest or surgery |
Macroeconomic Pressures and Orthopedic Device Valuations
Evaluating Conservative Management Versus Surgical Pathways
Establishing an individualized treatment plan requires balancing short-term pain relief with long-term joint preservation. For conditions like knee infections, targeted aspirations and antibiotic regimens resolve acute inflammation without entering the operating room. Conversely, chronic degeneration unmanaged by physical therapy shifts the clinical calculus toward surgical options ranging from arthroscopy to total knee replacement.
Patients exhibiting red-flag indicators—such as visible joint deformity, persistent instability, or an inability to bear weight exceeding 24 hours—require immediate specialized evaluation.
Disclaimer: The information provided in this article is for educational and informational purposes only and does not constitute financial advice.
