
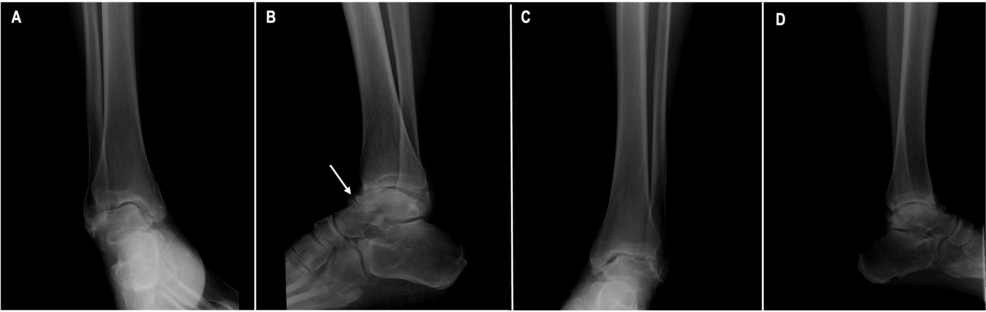
Selective thermal radiofrequency ablation of the deep peroneal articular branches offers a precise, non-surgical pathway for managing refractory ankle osteoarthritis. By targeting the sensory-specific neural pathways identified through diagnostic nerve blocks, clinicians can achieve significant pain reduction in patients who have failed conservative therapies, as detailed in a recent case report published in Cureus.
From Conservative Management to Targeted Neural Ablation
Ankle osteoarthritis presents a distinct therapeutic challenge compared to knee or hip variants, primarily due to the complex, variable nature of its articular innervation. For a 72-year-old patient suffering from recalcitrant, mechanical ankle pain, standard interventions—including physical therapy and intra-articular injections—offered only transient relief.
The transition from pulsed radiofrequency to thermal ablation changes clinical strategy. While pulsed radiofrequency acts as a neuromodulator—attempting to alter pain transmission without causing structural damage—thermal radiofrequency creates a controlled, permanent lesion. In this case, the shift was necessitated by the return of pain, which climbed back to a 7/10 score on the numeric pain rating scale (NPRS) despite repeated pulsed treatments.
The Diagnostic Precision of Perineural Blocks
The success of this procedure hinged on a high-fidelity diagnostic nerve block. Before proceeding to thermal ablation, clinicians performed an ultrasound-guided block of the deep peroneal nerve to confirm the target site. This step is critical because the deep peroneal nerve carries both motor and sensory fibers. Blocking the nerve provided complete, temporary relief during weight-bearing activities without inducing a motor deficit, effectively validating the target before committing to a thermal lesion.
The procedure utilized a 22-gauge, 6-cm radiofrequency cannula with a 10-mm active tip, connected to a Boston Scientific G4 radiofrequency generator. By positioning the cannula deep to the neurovascular bundle along the anterior tibial surface, the clinical team successfully isolated the articular branches while avoiding the motor fibers of the extensor hallucis longus and extensor digitorum longus muscles.
Clinical Outcomes at the Twelve-Month Marker
One year post-ablation, the results demonstrate a sustained therapeutic effect. The patient reported a reduction in pain from 7/10 to 3/10. This outcome highlights the effectiveness of selective denervation for anterior-predominant pain, provided the anatomical targeting is precise.
| Intervention Type | Primary Mechanism | Clinical Result (NPRS) |
|---|---|---|
| Intra-articular Injection | Anti-inflammatory/Lubrication | 5/10 (Partial) |
| Pulsed Radiofrequency | Neuromodulation | 3/10 (Temporary) |
| Thermal Ablation | Selective Denervation | 3/10 (Sustained) |
Residual Pain Persists After Nerve Treatment
The study notes that while thermal ablation effectively mitigated the patient’s nerve-based pain, residual symptoms remained during activities requiring significant ankle dorsiflexion, such as uphill walking. This residual pain is attributed to a prominent anterior osteophyte, a mechanical factor that neural ablation cannot correct. This distinction is vital for clinicians: denervation addresses the nociceptive input, but it does not resolve the structural architecture of the joint.
The case shows that for patients who are not candidates for or who decline arthrodesis or total ankle arthroplasty, targeted neural ablation provides a viable, joint-preserving alternative. However, the requirement for a positive diagnostic block remains the gold standard for patient selection.
The successful application of this technique in a complex, multi-year case suggests that the selective targeting of the deep peroneal articular branches could be integrated into broader pain management protocols for those with Kellgren-Lawrence grade 3 osteoarthritis. The focus remains on identifying the specific neural anatomy of the individual patient to ensure that sensory relief does not come at the cost of motor function.
