
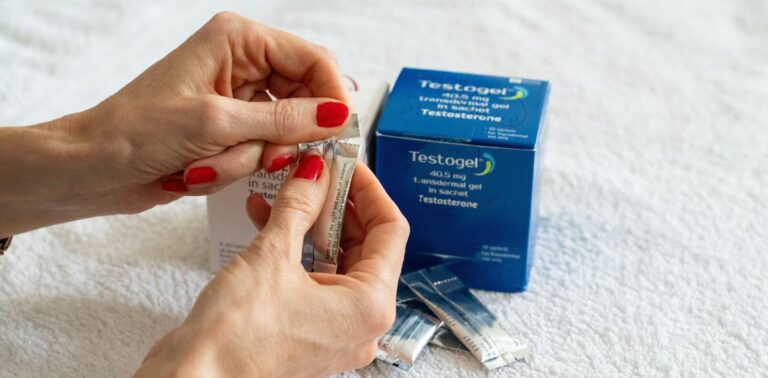
As U.S. regulators evaluate testosterone therapy for menopausal women, new data shows prescriptions increased from 0.4 to 1.8 per 1,000 women between January 2018 and July 2026, driven by off-label use, patient demand, and growing interest in longevity medicine despite clinical guidelines restricting its official use to a single condition.
The appetite for testosterone among women in perimenopause and menopause has surged dramatically across North America. Healthcare analytics firm Truveta tracked an increase in testosterone prescriptions per 1,000 women in the U.S., rising from 0.4 to 1.8 between January 2018 and July 2026. In the US, testosterone prescribing has almost tripled over the past decade, and NHS prescriptions to women in England rose roughly tenfold between 2015 and 2022. Data from a large medical database covering roughly half of all U.S. medical records indicates that women in midlife, specifically ages 45 to 64, accounted for more than 60% of these prescriptions, with the most common reported diagnoses listed as menopause, decreased libido, and hormone replacement therapy according to a study analysis.
Despite this explosive growth, the hormone remains off-label for female patients. Testosterone is not currently FDA-approved for women, although doctors increasingly prescribe it off-label. Neither Health Canada nor U.S. regulators have approved a testosterone product specifically designed for women as regulators began evaluating the landscape in September and called on drugmakers to conduct more woman-specific research. In September 2026, the US Food and Drug Administration held its first-ever public workshop examining evidence gaps and the need for future drug development in this area. The resulting treatment gap has left patients facing unexpected prescription delays and denials at pharmacies while attempting to fill off-label orders.

Hypoactive Sexual Desire Disorder Remains the Sole Guideline-Supported Indication
International clinical guidelines recognize testosterone therapy as an evidence-based treatment for a single condition: hypoactive sexual desire disorder (HSDD), defined as the only condition in women for which there is enough clinical evidence to recommend testosterone therapy following a report that noted sexual desire is shaped by relationships, stress, fatigue and mental health as much as by any single hormone.
Yet clinicians point out that sexual desire is influenced by relationships, stress, fatigue, and mental health rather than operating as a single master switch. Nisha Nigil Haroon emphasized that patients should avoid pellets or oral formulations due to dosing inconsistencies and excessive exposure risks.
Patient Reports from Longevity Platforms and Clinical Realities
Beyond sexual health, many women turn to testosterone seeking relief from broader midlife symptoms. An analysis of 1,220 women in perimenopause or menopause conducted by the physician-led longevity platform Hone Health in September 2026 evaluated patients taking testosterone without estrogen or progesterone using the Menopause Quality of Life Questionnaire. The participants reported perceived improvements across 18 menopause symptoms, with the greatest gains appearing in sexual desire, energy, strength, and stamina.
Kunsman noted that testosterone receptors are distributed throughout the brain, muscles, bones, and cardiovascular system. She added that just because we don’t have testicles doesn’t mean we don’t need testosterone,
advocating for physiological dosing that restores women to an age-optimized range to help maintain lean mass and metabolic health.

However, independent specialists urge caution regarding expectations. Russell Frank, MD, an ob/gyn specializing in menopause at the Jewish General Hospital University Health Centre in Montréal, explained that not every woman will see a benefit from testosterone, and if they do, the benefit may be modest.
Researchers emphasize that observational data from longevity platforms show association rather than direct proof of cause and effect.
The Longevity Push Versus Broader Health Realities
Much of the surging demand is fueled by a broader cultural desire for health span extension and disease prevention. Experts note that popular media frequently frames hormone therapies as promoting longevity, yet there is no compelling evidence that hormone therapy is going to prevent cancer or cognitive decline in naturally menopausal women.
Medical professionals emphasize that comprehensive cardiovascular risk management—including healthy diet, regular exercise, weight control, and blood pressure monitoring, which constitute the American Heart Association Life’s Essential 8—remains vital for protecting long-term brain and heart health.
