
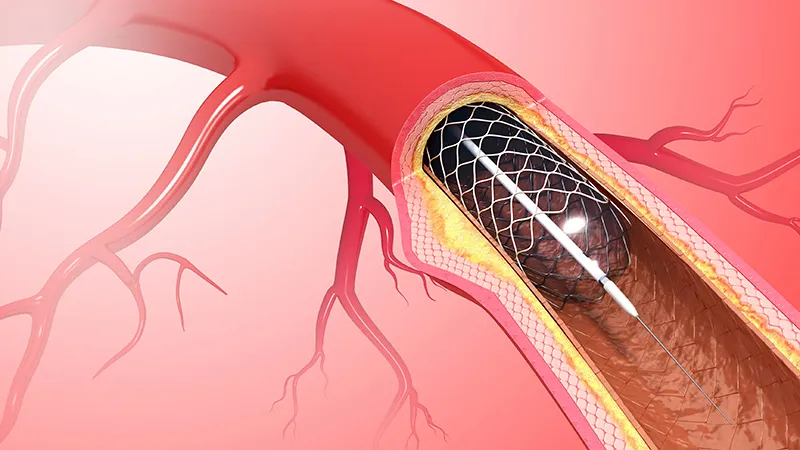
Twenty-five years after the landmark COURAGE trial first challenged the necessity of routine angioplasty for stable coronary artery disease, new long-term data confirms that early elective stenting provides no survival advantage over optimal medical therapy.
The findings, presented at the American Heart Association (AHA) Scientific Sessions 2026, suggest that conservative management continues to provide effective long-term patient outcomes.
Clinical Insights for Patient Management
- Routine Stents Do Not Extend Life: In patients with stable coronary artery disease, elective percutaneous coronary intervention (PCI)—the procedure to open clogged arteries with a stent—does not reduce the risk of death or heart attack compared to medication alone.
- Medication Remains Primary: Optimal medical therapy (OMT), which includes blood pressure control, cholesterol-lowering statins, and antiplatelet drugs, serves as a safe and effective first-line treatment for most stable patients.
- Quality of Life Focus: Clinicians now prioritize PCI as a tool for managing angina (chest pain) and improving physical comfort, rather than as a preventative measure for major cardiac events or mortality.
Long-Term Outcomes in the VA Population
The original COURAGE trial, which initially followed patients for a median of 4.6 years, found no significant difference in hard clinical endpoints between those treated with percutaneous coronary intervention (PCI) and those managed with medication.
Researchers returned to this data 25 years later to determine if a longer observation period would reveal a hidden benefit. Analyzing 959 patients—a subset of the original VA program participants—researchers found that the estimated incidence of deaths at 25 years was 83.9% in the PCI group compared to 82.2% in the TMO group.
"One might expect that this population would have a better chance of seeing a more pronounced treatment effect," Dr. Butala said. Despite this, the hazard ratio for death or myocardial infarction was 1.01, indicating that even in higher-risk patients, the invasive procedure did not alter the long-term trajectory of the disease.
Shifting Standards of Practice
The persistence of these results has fundamentally altered how cardiologists approach elective interventions. Rasha Al-Lamee, MBBS, PhD, a professor of medicine and specialist in interventional medicine at Imperial College Healthcare NHS Trust, told Medscape that the trial serves as a guide on the limitations of the catheterization lab.
While some critics previously argued that the original study did not last long enough or that the patient population was not representative, the 25-year follow-up addresses these concerns by showing no divergence in the Kaplan-Meier survival curves over the duration of the follow-up.
Al-Lamee emphasized that while stenting technology has advanced since the trial began, the fundamental message remains consistent: conservative management is a reasonable, evidence-based choice for stable coronary disease. “These data give me more confidence when I am considering treating a patient conservatively,” she said. The trial has been instrumental in shifting the clinical focus from “can this lesion be stented?” to “will this intervention improve the patient’s quality of life?”
| Metric | PCI Group | Medical Therapy Group |
|---|---|---|
| 25-Year Estimated Mortality | 83.9% | 82.2% |
| Revascularization Rate | 50.4% | 53.5% |
| Hazard Ratio (Death/MI) | 1.01 | Reference |
Patients with Stable Coronary Artery Disease Should Consult Doctors
These findings specifically apply to patients with stable coronary artery disease—those whose chest pain is predictable and manageable with medication. This study does not apply to patients experiencing acute coronary syndromes, such as an active heart attack or unstable angina, where immediate revascularization is a life-saving necessity.
Patients currently on medical therapy should not discontinue their prescribed medications or alter their treatment plans without consulting their cardiologist. If you experience new or worsening chest pain, shortness of breath, or symptoms that deviate from your established baseline, seek professional medical evaluation immediately to determine if your condition has shifted from stable to unstable.
The discussion regarding the role of elective procedures remains open, particularly concerning how current imaging-guided stenting might compare to the older techniques used in the original trial. As Dr. Tariq Muhammad Khan, a cardiac surgeon at the Peshawar Institute of Cardiology, Pakistan, noted, the challenge for future practice is determining which individual patients will truly benefit from intervention based on symptom relief rather than the hope of altering mortality.
References
- Boden WE, et al. Optimal Medical Therapy with or without PCI for Stable Coronary Disease.
- American Heart Association (AHA) Scientific Sessions 2026: Long-term follow-up of the COURAGE trial.
- Butala NM, et al. 25-Year Mortality Outcomes in the COURAGE Trial. Presented at AHA Scientific Sessions 2026.
Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a medical condition.
