
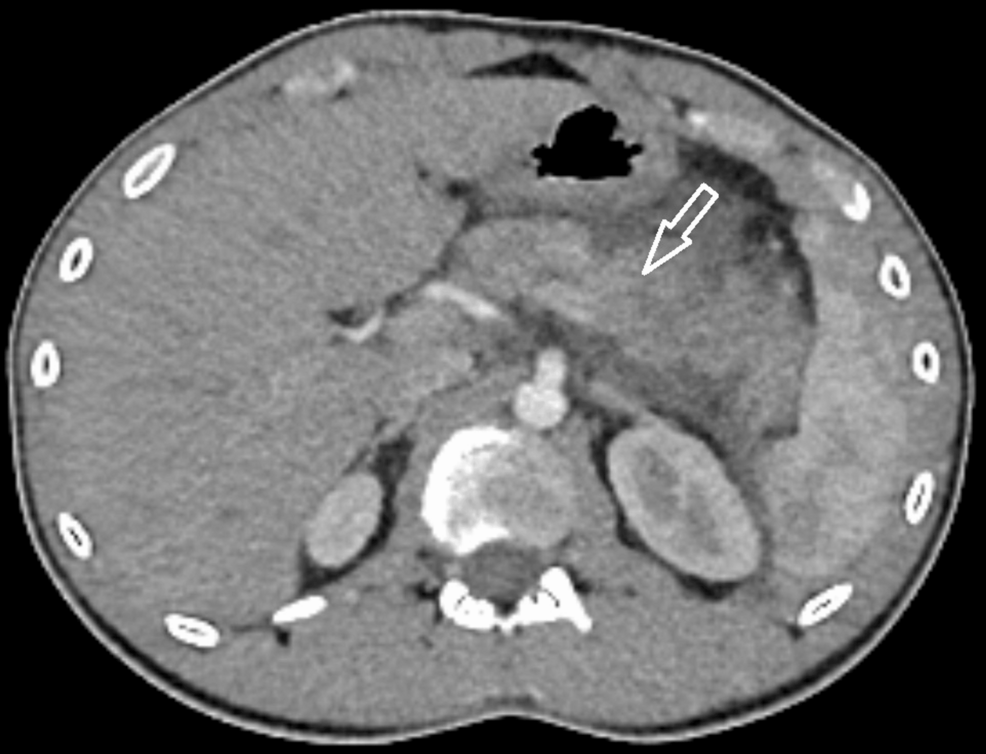
Doctors in a new case report describe a 19-year-old man who arrived at an emergency room with sharp upper-abdominal pain and was found to have acute pancreatitis — yet the usual culprits, gallstones, alcohol and high blood fats, were all ruled out.
The eventual answer, published in the journal Cureus, was celiac disease never diagnosed before, surfacing as severe pancreatic inflammation.
The case matters because it stretches what patients and clinicians should expect from celiac disease. The man had no diarrhea, no bloating, no weight loss — the classical digestive picture. What he had was 796 U/l of lipase on admission, a pancreas that turned necrotic on later imaging, and, hiding beneath it all, a duodenal biopsy showing Marsh stage IIIa villous atrophy, Cureus reported.
Pancreatitis resolved after gluten-free diet
- Pancreatitis can be the first sign of celiac disease. Doctors traced his unexplained pancreatic inflammation to an immune reaction to gluten, confirmed by biopsy after standard tests came up empty.
- He felt better than expected after going gluten-free. Nine months later, follow-up scans showed his pancreas had fully recovered, and his gut looked normal.
- Most pancreatitis isn’t caused by celiac disease. Standard work-up finds the cause in 80% of cases; this link is rare and usually only surfaces when nothing else explains the attack.
What the patient looked like on day one
The young man’s pain began shortly after dinner — a sharp sensation in the epigastric and upper-left abdomen, no nausea, vomiting, diarrhea or fever. On arrival his heart rate was 70 per minute, temperature 36.0 °C, blood pressure 130/72 mmHg, and his body mass index 19.4 kg/m², low-normal for an adult.
Labs told a sharper story. Pancreatic amylase sat at 307 U/l and lipase at 796 U/l — both considerably raised — while C-reactive protein was only 1.4 mg/l and white cells mildly elevated at 14.3×10⁹/l. A CT scan within 12 hours showed an edematous, swollen pancreatic tail with fluid collecting around it.
His history held two clues that only made sense later, Cureus noted. A year earlier, a general practitioner had found mild vitamin D and iron deficiency, both classic consequences of celiac-related malabsorption. He had also battled recurring MRSA skin abscesses, including a perineal abscess needing surgical drainage, and had recently finished a course of oral clindamycin.
Exclusion process found no clear cause
What followed was a near-textbook exclusion process. MRCP imaging found no gallstones and no cholestasis. Calcium and triglycerides were normal. Autoimmune panels — ANA, ANCA, anti-MPO, anti-PR3 — were negative, and total IgG4 fell within range. Serology for Coxiella burnetii and quantitative CMV DNA were negative. There was no pancreas divisum or other anatomical predisposition.
Routine diagnostics identify a cause in about 80% of acute pancreatitis cases, leaving the remainder classified as idiopathic, the report states. This patient, temporarily, fell into that last 20%.
Ten days after discharge, an endoscopic ultrasound changed the picture. It revealed a large necrotic collection with fluid and solid components and early calcification in the pancreatic tail — upgrading the diagnosis from interstitial edematous pancreatitis to necrotizing pancreatitis. Fine-needle aspiration showed necrotic debris and dense inflammatory infiltration, with no malignancy.
Then came the celiac findings. The duodenal biopsy showed 40 intraepithelial lymphocytes per 100 epithelial cells and patchy subtotal villous atrophy — Marsh stage IIIa. Tissue transglutaminase IgA measured 10.0 kU/L, at the top of the borderline band (normal below 7, borderline 7–10), with total IgA normal. Only then was the immune-mediated gut disease identified, and it “may have been a contributing factor; a causal relationship cannot be confirmed,” the authors state.
How the case resolved
Recovery ran a favorable course. The patient’s pain resolved, pancreatic enzymes fell, and he went home after seven days, though CRP peaked at 340 mg/l on day four — a striking contrast with the near-normal 1.4 mg/l at admission, reflecting how late this inflammatory marker can crest.
Nine months later, a follow-up endoscopic ultrasound showed complete resolution with unremarkable pancreatic tissue. At one year, he reported feeling well, had gained 7 kg on a strict gluten-free diet, and described less general fatigue — noting he had never experienced the bowel symptoms most people associate with celiac disease.
| Marker | Admission | Reference/notes |
|---|---|---|
| Lipase | 796 U/l | Considerably elevated |
| Pancreatic amylase | 307 U/l | Considerably elevated |
| C-reactive protein | 1.4 mg/l | Peaked at 340 mg/l on day 4 |
| Leucocytes | 14.3×10⁹/l | Elevated, with neutrophilia |
| tTG-IgA | 10.0 kU/L | Borderline (normal <7) |
| Intraepithelial lymphocytes | 40/100 epithelial cells | Marsh stage IIIa biopsy |
A rare overlap, seen through the evidence
How common is this overlap, really? The research base is thin, and the Cureus authors are candid about it. In one cited cohort study, Patel and colleagues tested 169 patients referred for sphincter of Oddi manometry over idiopathic pancreatitis and found 12 cases of celiac disease — nine of them previously undiagnosed.
Population-level data add nuance. A retrospective matched cohort study using a Swedish nationwide histopathology registry found a moderately increased long-term risk of a first episode of acute pancreatitis in people with celiac disease, but no increased risk of recurrences.
A separate multi-center study from the TriNeTx research network in Cambridge, Massachusetts, by Krishnan and colleagues, went further: it showed a significantly increased long-term risk of developing acute and chronic pancreatitis — across alcohol-related, biliary, and idiopathic subtypes — in patients with celiac disease.
What remains open is the mechanism. The report does not establish exactly how gluten-driven intestinal inflammation triggers pancreatic injury, and the authors explicitly withhold a causal claim. They also concede limits in their own work-up: only fine-needle aspiration, not a full biopsy, of pancreatic tissue was taken, and no glucocorticoid trial was performed, so autoimmune pancreatitis could not be excluded with certainty.
Celiac testing not warranted for mild upset
- A single mild digestive upset does not warrant celiac testing on the strength of this case alone — the association is rare, and the authors themselves could not confirm causation.
- Anyone with severe or recurrent acute pancreatitis without an identifiable cause should ask about a complete etiologic work-up; Cureus notes additional endoscopic ultrasound is strongly indicated after two or more episodes, or a severe first episode, and for patients over 39, tobacco users, or those with a family history of pancreatic cancer.
- A gluten-free diet should not be started before diagnostic testing, because it can normalize antibodies and biopsy findings and obscure the diagnosis.
- Unresolved iron or vitamin D deficiency, or unexplained fatigue with borderline celiac serology, is a reasonable trigger to discuss duodenal biopsy with a physician.
Why this case matters beyond one patient
For clinicians, the case reinforces the report’s central point: recognizing celiac disease’s non-classical and silent phenotypes depends on knowing its associated conditions and referring for evaluation, rather than waiting for digestive symptoms that may never come. For health systems, it argues for keeping celiac serology on the list when pancreatitis idiopathic work-ups stall.
For patients, the trajectory here is the reassuring part. Complete pancreatic recovery on imaging, seven kilograms regained, normal bowel habits throughout — the disease announced itself loudly, then quieted entirely once gluten left the diet.
The authors’ word for the link remains the honest one: celiac disease “may have been a contributing factor; a causal relationship cannot be confirmed.”
References
- Cureus — “Acute Pancreatitis as the First Manifestation of Celiac Disease: A Case Report” (case report and patient data)
- Patel et al. — cohort study of celiac testing in 169 patients with idiopathic pancreatitis, cited in the Cureus report
- Yao J et al. — retrospective matched cohort study, Swedish nationwide histopathology cohort, cited in the Cureus report
- Krishnan et al. — multi-center retrospective matched cohort study, TriNeTx research network, Cambridge, MA, cited in the Cureus report
- Marsh classification of duodenal histopathology (Marsh stage IIIa), as referenced in the Cureus report
Readers experiencing severe abdominal pain should seek emergency care.
