
A 54-year-old man presenting with flank pain, positive nitrites, and profound pancytopenia was diagnosed with acute promyelocytic leukemia after clinicians identified circulating blasts and the PML::RARA fusion gene on fluorescence in situ hybridization, Cureus reported.
The patient, who has a four-year history of Parkinson’s disease, was transferred from an outside hospital to evaluate left-sided flank and back pain associated with urination. He also reported lower-extremity bruising, gingival bleeding, and subjective fever. While dipstick urinalysis showed positive nitrites and moderate blood, computed tomography revealed no nephrolithiasis, hydronephrosis, or acute intra-abdominal inflammation.
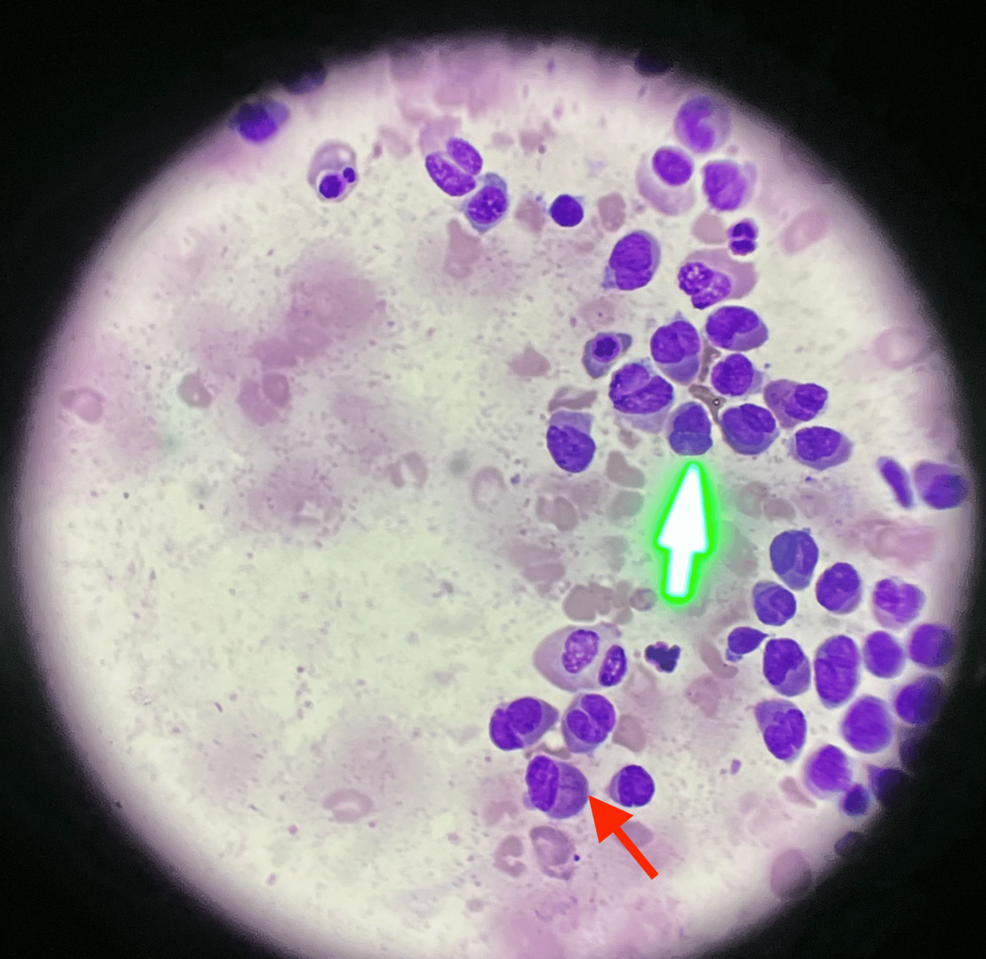
Initial laboratory workup uncovered profound pancytopenia with a white blood cell count of 2.0 × 10³/µL, hemoglobin at 7.2 g/dL, and a platelet count of 7,000/µL. Although his initial fibrinogen level measured 528 mg/dL, clinicians noted that acute-phase reactants can falsely elevate this concentration during inflammation or infection. Bone marrow examination subsequently demonstrated greater than 95% cellularity with abnormal promyelocytic proliferation.
Medical teams initiated empiric piperacillin-tazobactam for suspected urinary tract infection due to dysuria and nitrite-positive findings. However, concurrent mucocutaneous bleeding and multi-lineage cytopenias prompted urgent hematology consultation. Peripheral blood smear review revealed circulating blasts, prioritizing bone marrow biopsy over routine urologic investigation.
Fluorescence in situ hybridization confirmed the promyelocytic leukemia-retinoic acid receptor alpha fusion resulting from the t(15;17) chromosomal translocation. Treatment with all-trans retinoic acid and arsenic trioxide induction therapy began on hospital day three. By day six, supportive and leukemia-directed care increased hemoglobin to 9.3 g/dL and platelets to 37,000/µL, though neutropenia persisted.
- Look beyond common symptoms: Urinary complaints can occasionally mask severe hematologic emergencies like acute promyelocytic leukemia.
- Rely on blood counts: A complete blood count and peripheral smear serve as critical diagnostic tools when unexplained bleeding accompanies low blood cell counts.
- Act without delay: Guidelines recommend starting all-trans retinoic acid immediately upon clinical suspicion, prior to definitive molecular confirmation, to reduce early hemorrhagic mortality.
Acute promyelocytic leukemia remains a hematologic emergency driven by the accumulation of abnormal promyelocytes that arrest cellular differentiation. Early hemorrhagic mortality represents a major clinical hurdle, frequently exacerbated by delayed recognition or delayed administration of targeted therapy. Multicenter studies cited in the report demonstrate that treatment delays beyond 24 hours serve as independent predictors of early death.
| Hematologic Parameter | Initial Presentation Value | Post-Induction Value (Day 6) |
|---|---|---|
| White Blood Cell Count | 2.0 × 10³/µL | Not Reported |
| Hemoglobin | 7.2 g/dL | 9.3 g/dL |
| Platelet Count | 7,000/µL | 37,000/µL |
| Fibrinogen | 528 mg/dL | Not Reported |
The case shows that serial coagulation monitoring is necessary. An elevated initial fibrinogen level fails to exclude coagulopathy when severe thrombocytopenia and bleeding are present. Clinicians emphasize that first-contact providers must avoid attributing discordant hematologic findings solely to uncomplicated urinary tract pathology.
Patients exhibiting spontaneous bruising, gingival bleeding, petechiae, or unexplained fatigue alongside multi-lineage cytopenias require immediate hematologic evaluation. Targeted differentiation therapy involving all-trans retinoic acid requires close supervision in specialized inpatient settings due to the high risk of differentiation syndrome and life-threatening coagulopathy. Healthcare providers must weigh individual patient comorbidities, such as preexisting neurological conditions, while coordinating intensive transfusion support and serial coagulation panels.
- Sanchez J, Prado Escobar D, Memari K, et al. From Urologic Symptoms to Promyelocytic Leukemia-Retinoic Acid Receptor Alpha (PML::RARA): Acute Promyelocytic Leukemia Recognized Through Mucocutaneous Bleeding and Pancytopenia. Cureus. 2026;18(11):e119368. doi:10.7759/cureus.119368.
Always consult a qualified physician regarding any medical condition or therapeutic intervention.
