
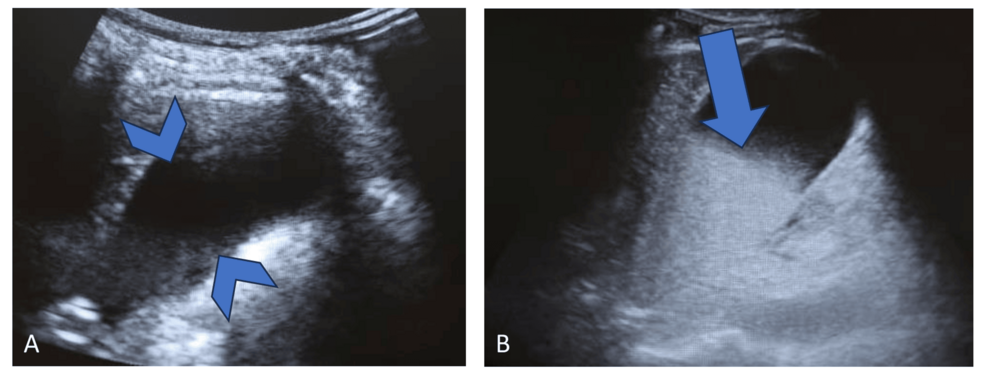
A 55-year-old man developed acute right upper quadrant pain and hematemesis ten minutes after undergoing an ultrasound-guided liver biopsy for an LR-4 hepatic lesion, with subsequent imaging confirming acute hemobilia into the gallbladder lumen, Cureus reported.
The case, documented by medical teams evaluating post-procedural complications, details a rare instance of immediate symptomatic bleeding following a percutaneous core needle biopsy of the liver. While hemorrhage remains the most clinically significant risk of the procedure, delayed presentations averaging five days are typical, making this hyperacute presentation distinct.
Doctors Treat Rare Hemobilia with Observation After Liver Biopsy
- What happened: A patient experienced sudden abdominal pain and vomiting blood just minutes after a liver tissue sample was collected.
- The diagnosis: Doctors used ultrasound and computed tomography (CT) scans to discover that blood had pooled inside the patient’s gallbladder, a rare condition called hemobilia.
- The outcome: Because the patient’s vital signs remained stable and the bleeding stopped on its own, doctors treated him successfully with close observation rather than surgery.
Clinical Presentation of Hyperacute Hemobilia
The patient, who has a history of chronic hepatitis B, was referred to the radiology department for evaluation of a 40 by 39 millimeter focal hepatic lesion located at the junction of hepatic segments IVa, IVb, and VIII.
Magnetic resonance imaging previously characterized the mass with arterial phase hyperenhancement and washout, earning a Liver Imaging Reporting and Data System category of LR-4. Pre-procedural blood work showed a hemoglobin level of 12.5 grams per deciliter, a normal platelet count of 280,000 per microliter, and 75 percent prothrombin activity, confirming no standard contraindications to tissue acquisition.
A planning ultrasound confirmed a normal, anechoic gallbladder before clinicians used a semi-automatic 16-gauge core biopsy needle with a coaxial introducer to secure three core specimens via an intercostal approach.
Ten minutes post-procedure, the patient reported acute right upper quadrant abdominal pain and experienced hematemesis, defined as the vomiting of blood. Bedside ultrasonography immediately revealed new echogenic material occupying roughly half of the gallbladder lumen, shifting the clinical focus toward intrabiliary hemorrhage.
CT Scans Show Blood in Gallbladder Without Active Hemorrhage
Emergency multiphasic contrast-enhanced computed tomography performed roughly fifteen minutes after symptom onset showed hyperattenuating gallbladder contents measuring approximately 52 Hounsfield units, indicating acute blood products. Scans also displayed small foci of gas along the needle tract, a normal finding following recent intervention. However, arterial and portal venous phases demonstrated no active contrast extravasation, pseudoaneurysm, or visible arteriobiliary fistula.
Because the patient remained hemodynamically stable without signs of ongoing hemorrhage, the medical team elected conservative management with close clinical observation. A hemoglobin check six hours later registered 12.3 grams per deciliter and remained stable the following day. The patient required no blood transfusions, endoscopic procedures, or angiographic embolization, and was discharged after three days. Outpatient follow-up at five weeks confirmed he remained completely asymptomatic.
Seek Medical Evaluation for Severe Post-Biopsy Symptoms
Percutaneous liver biopsies are generally contraindicated in patients with uncorrectable coagulopathies, severe thrombocytopenia, or extensive ascites. Following any liver biopsy, individuals must seek immediate medical evaluation if they experience severe or worsening right upper quadrant abdominal pain, dizziness, rapid heart rate, fever, jaundice, or episodes of vomiting blood or passing black, tarry stools.
| Clinical Parameter | Pre-Procedural Value | Post-Procedural Finding |
|---|---|---|
| Hemoglobin Level | 12.5 g/dL | 12.3 g/dL (stable) |
| Platelet Count | 280,000 / µL | Within normal limits |
| Prothrombin Activity | 75% | Not reassessed |
| Gallbladder Content | Anechoic (Clear) | Echogenic (Blood products) |
Diagnostic Evaluation of Rare Intrabiliary Bleeding
While post-biopsy hemorrhage usually involves intraperitoneal bleeding, hemobilia involves blood tracking directly into the biliary tree. The classical Quincke triad—consisting of gastrointestinal bleeding, right upper quadrant pain, and jaundice—appears together in only a minority of cases, as demonstrated by this patient presenting without jaundice. Sequential imaging combining bedside ultrasound and multiphasic CT remains vital for identifying intracholecystic blood products even when a specific vascular-biliary communication cannot be visualized.
References
- Cureus. Immediate Hemobilia Following Percutaneous Liver Biopsy: A Case Report of an Acute Symptomatic Presentation.
Always seek the advice of your physician or other qualified health provider with any questions regarding a medical condition.
