
Retrograde Jejunojejunal Intussusception Following Sleeve Gastrectomy to Roux-en-Y Gastric Bypass Conversion
Retrograde jejunojejunal intussusception emerged as a rare late complication in a 69-year-old female patient a decade after her initial bariatric procedure, presenting with a perforated common channel despite normal inflammatory markers and the absence of peritoneal signs.
Intussusception occurs when a segment of the bowel telescopes into an adjacent section, disrupting normal peristalsis and gastrointestinal transit. While relatively common in pediatric populations where a distinct lead point like a tumor or polyp usually drives the invagination, the pathology behaves differently following bariatric interventions such as a Roux-en-Y gastric bypass (RYGB). In these post-surgical configurations, lead points are typically absent. Instead, the distal bowel telescopes backward against the normal direction of food flow and peristaltic waves, creating a retrograde telescoping event.
Recent surgical literature published in Cureus details a complex presentation involving a patient whose medical history featured a laparoscopic sleeve gastrectomy performed ten years prior for a body mass index of 42 kg/m². Roughly two years after that initial operation, she experienced symptomatic gastroesophageal reflux disease, prompting a laparoscopic conversion to an RYGB. Ten years downstream from her original bariatric journey, she woke up with acute abdominal pain radiating to her back, accompanied by recent diarrhea but lacking vomiting or fever.
Reveal Atypical Presentation During Emergency Evaluation
Clinical evaluation upon arrival at the Emergency Department revealed an atypical presentation that masked an underlying surgical emergency. Her vital signs remained stable with a heart rate of 78 beats per minute and a blood pressure of 132/87 mmHg, while her abdomen exhibited diffuse tenderness without guarding, rigidity, or overt peritoneal signs. Laboratory analysis showed leukocytosis with a white blood cell count of 14.5 × 10³/µL, a mildly elevated lactate level of 2.2 mmol/L, and a surprising C-reactive protein reading of 0 mg/dL. Plain abdominal radiography demonstrated air-fluid levels, and nasogastric intubation yielded coffee-ground content.
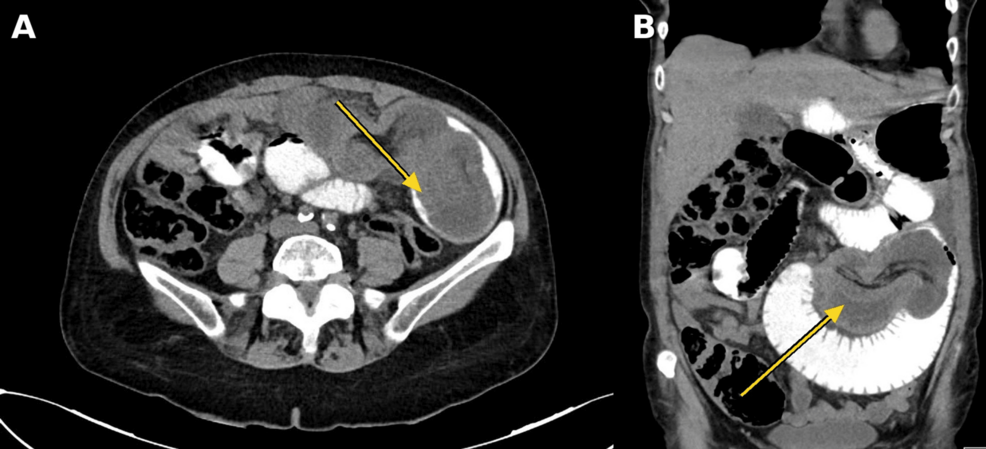
Contrast-enhanced computed tomography of the abdomen proved critical, identifying dilated proximal small bowel loops up to 5 cm in diameter alongside a complex in the left upper abdomen. The imaging captured a bowellike configuration measuring approximately 23 cm from its entry point to its tip, localized near the jejunojejunal anastomosis. Although computed tomography could not definitively isolate which specific limb drove the obstruction, it successfully mapped out the proximal dilation without displaying free intraperitoneal air, creating a diagnostic puzzle regarding the integrity of the bowel wall.
Diagnostic laparoscopy immediately exposed the severity of the crisis prior to mechanical bowel manipulation. Surgeons discovered a 1 cm perforation situated in the common channel directly outside the intussuscepted segment. The perforation edges appeared edematous yet lacked fibrin or gross peritoneal contamination. Because the invaginated loop could not be reduced laparoscopically, the clinical team converted the procedure to an exploratory laparotomy.
Map Anatomical Architecture During Intraoperative Exploration
Intraoperative exploration mapped out the exact anatomical architecture of the patient’s prior bariatric modifications. The biliopancreatic limb measured approximately 50 cm from the ligament of Treitz to the jejunojejunal anastomosis and continued as an unobstructed blind segment measuring about 30 cm, with its tip adherent to the liver. The alimentary Roux limb measured about 80 cm from the gastrojejunostomy to the anastomosis and displayed distal dilation. The common channel had telescoped retrogradely through the side-to-side stapled jejunojejunal anastomosis into the blind segment.
| Anatomical Segment | Measured Length / Parameter | Clinical Observation |
|---|---|---|
| Biliopancreatic Limb | 50 cm to anastomosis + 30 cm blind tip | Dilated, tip adherent to liver without angulation |
| Alimentary (Roux) Limb | 80 cm | Dilated at its distal end |
| Telescoped Common Channel | 23 cm from entry point to tip | Hyperemic, viable, containing a 1 cm perforation |
| Surgical Intervention | Reduction with fixation and primary repair | No bowel resection performed due to viability |
Surgeons successfully milked the telescoped bowel out of the blind segment to achieve complete reduction. The bowel wall warmed with saline application, demonstrating returning peristalsis and healthy color changes that confirmed tissue viability. Rather than performing a complex bowel resection, the team elected to close the 1 cm perforation transversely using a continuous single-layer 3-0 Vicryl suture. They closed both the Petersen space and the jejunojejunal mesenteric defect using a continuous barbed V-Loc suture and anchored the common channel to the biliopancreatic limb and mesenteric root with interrupted Vicryl sutures to prevent recurrence.
The patient’s recovery proceeded without adverse events. She received intravenous ceftriaxone and metronidazole for three days, advanced her oral intake gradually under dietary supervision, and was discharged home on postoperative day 6. At her two-month clinical follow-up, she reported no new symptoms and showed no evidence of recurrence.
References
- Simper SC, Erzinger JM, McKinlay RD, et al. Retrograde intussusception safely treated by operative reduction and segmental enteropexy after Roux-en-Y gastric bypass. Surg Obes Relat Dis. 2008;4(6):752-7.
- Hii MW, Smithers BM, Gotley DC. Retrograde jejunojejunal intussusception after Roux-en-Y gastric bypass: case report and literature review. Surg Obes Relat Dis. 2005;1(6):560-4.
- Cureus. Retrograde Jejunojejunal Intussusception With Perforation After Sleeve-to-Roux-en-Y Gastric Bypass (RYGB) Conversion: A Case Report. 2026.
