
A 46-year-old woman with Congenital Central Hypoventilation Syndrome (CCHS) experienced acute respiratory failure after her diaphragmatic pacemaker failed and her transmitter was lost. Admitted with an outdated BiPAP machine and a viral infection, she highlighted the severe transition gap adult patients face when leaving pediatric care.
NIPPV Stabilizes Adult CCHS Patients During Respiratory Failure
- What happened: A patient with a rare genetic breathing disorder suffered a lung crisis because her implanted breathing pacemaker stopped working and she entered adult systems often unfamiliar with the syndrome.
- The core risk: CCHS patients lack autonomic ventilatory responses to hypoxemia and hypercarbia, meaning viral infections can precipitate acute hypoxic and hypercapnic respiratory failure without proper mechanical ventilation.
- The modern solution: Hospitals can use non-invasive positive pressure ventilation (NIPPV) with intelligent volume-assured pressure support (iVAPS) to stabilize adult patients during respiratory decompensation.
The Anatomy of Pacing Failure in Adult CCHS
Congenital Central Hypoventilation Syndrome is a rare, lifelong disorder driven by heterozygous mutations in the paired-like homeobox 2B (PHOX2B) gene. While voluntary breathing remains intact, autonomic ventilatory responses to hypoxemia (low blood oxygen) and hypercarbia (excess carbon dioxide) are absent or attenuated.
Historically, prognoses were grim. Modern neonatal interventions, including temporary tracheostomies and subsequent diaphragmatic pacing, have allowed a growing number of patients to reach adulthood.
Diaphragmatic pacers use a subcutaneous radiofrequency receiver connected to the phrenic nerve. An external antenna transmits electromagnetic pulses that stimulate the nerve, producing diaphragmatic contraction. Over time, however, these hardware systems face mechanical degradation.
Subcutaneous tissue changes can attenuate signal transmission. Receivers can also develop calcifications, as documented in clinical literature where surgical exploration revealed significant circumferential calcium accumulation on the right pacer receiver.
When these implanted devices fail, patients are left vulnerable to acute or gradual hypoventilation. If they transition from experienced pediatric programs to adult systems often unfamiliar with the syndrome and with diaphragmatic pacing, they face significant challenges.
Patient Presents with Respiratory Infection and Marked Hypercapnia
Upon admission to the emergency department, the patient presented with an upper respiratory tract infection. Her initial room air oxygen saturation was 80%.
| Clinical Parameter | Patient Value | Reference Range |
|---|---|---|
| Blood Pressure | 154/94 mmHg | 90-120/60-80 mmHg |
| pH (Arterial, 30% FiO2) | 7.36 | 7.35-7.45 |
| PaCO2 (Arterial, 30% FiO2) | 74 mmHg | 35-45 mmHg |
| Hemoglobin | 16.7 g/dL | 12.0-15.5 g/dL (women) |
| Bicarbonate (HCO3) | 37 mmol/L | 20-31 mmol/L |
Arterial blood gas analysis revealed a compensated respiratory acidosis with marked hypercapnia, consistent with chronic alveolar hypoventilation with an acute component. Her elevated hemoglobin of 16.7 g/dL was consistent with secondary polycythemia from chronic hypoxemia.
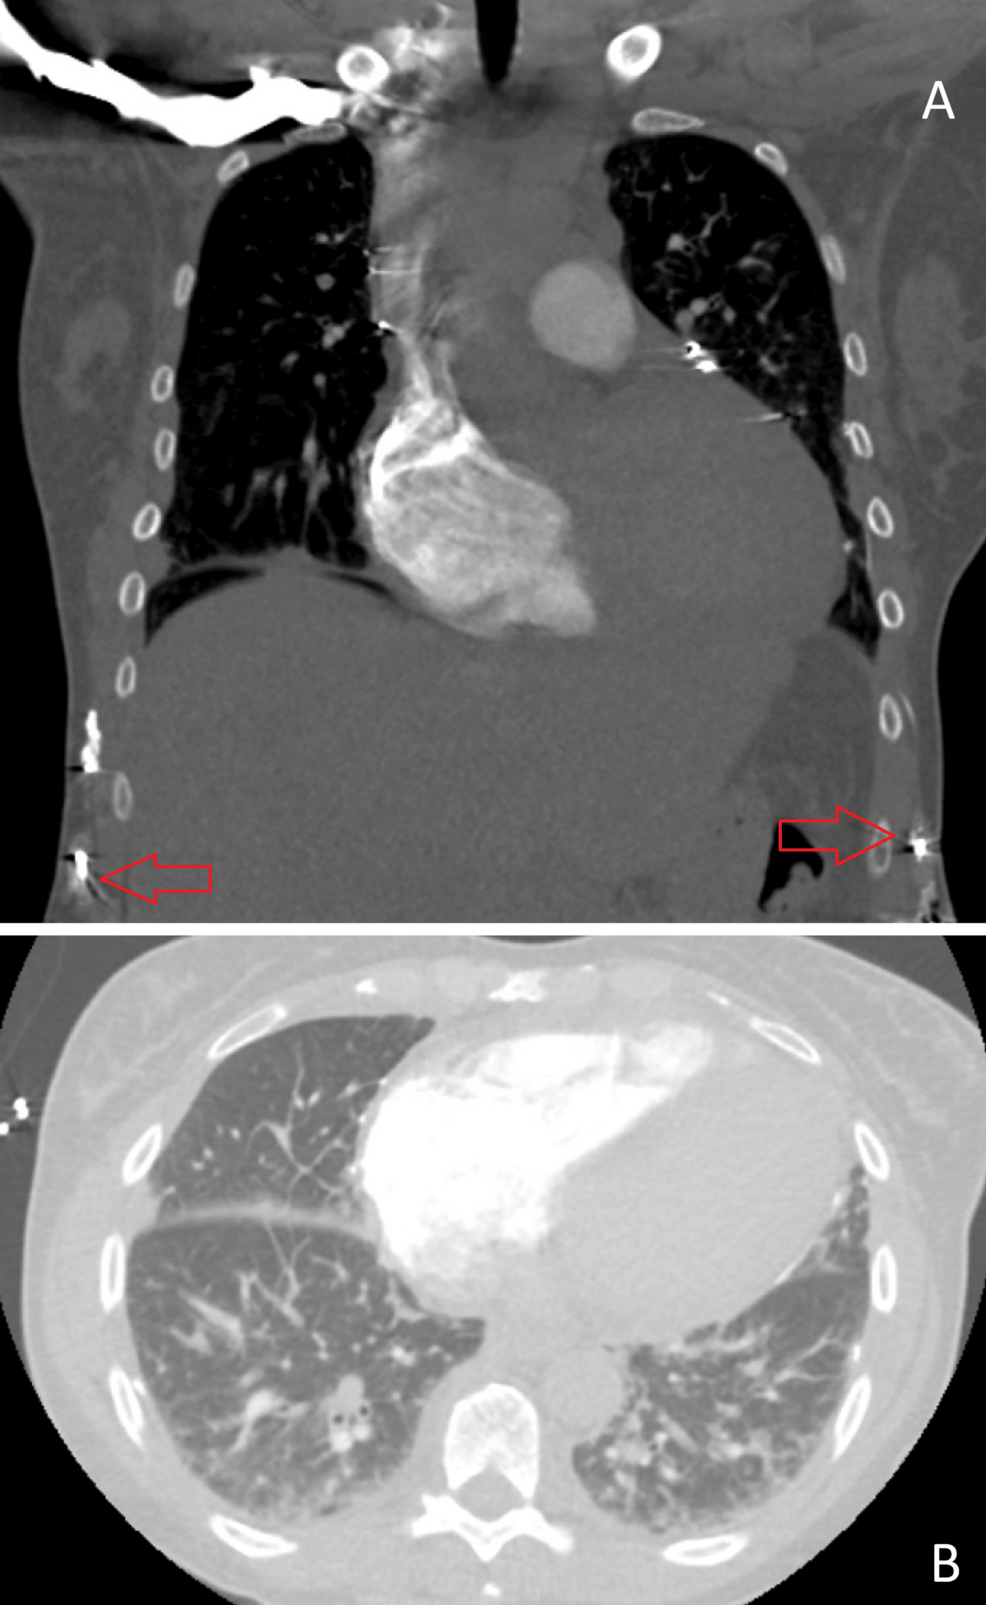
Computed tomography angiography of the chest ruled out a pulmonary embolism but exposed bilateral diaphragmatic pacer receivers resting external to the rib cage. Transthoracic echocardiography showed a left ventricular ejection fraction of 50%, alongside a dilated right ventricle and right atrium. These imaging markers were consistent with pulmonary hypertension and right heart strain.
Clinical management required diuresis to treat pulmonary edema. To replace her outdated BiPAP device and missing pacer transmitter, clinicians initiated ventilatory support via an average volume-assured pressure support system. Preliminary settings targeted a tidal volume of 490 mL at a set respiratory rate of 16 breaths per minute.
Because end-tidal carbon dioxide monitoring for NIPPV is often inaccurate due to high flow rates and air leaks, care teams relied on morning venous blood gases to verify ventilatory efficacy. Prior to discharge, her regimen was transitioned to a home ventilator utilizing intelligent volume-assured pressure support (iVAPS) and auto-EPAP to maintain a target alveolar ventilation of 6.2 L/min, which was later optimized to 6.6 L/min.
Specialists Optimize Long-Term Strategy as Pacer Revisions Remain Unavailable
Pacer revisions are not readily available at most centers.
Efforts to reassess the patient’s non-functional diaphragmatic pacer remain ongoing as outpatient specialists optimize her long-term ventilatory strategy.
References
- Cureus: Congenital Central Hypoventilation Syndrome in an Adult With Diaphragmatic Pacing Failure.
- PHOX2B gene mutations cause congenital central hypoventilation syndrome, a rare disorder characterized by autonomic nervous system dysregulation.
