
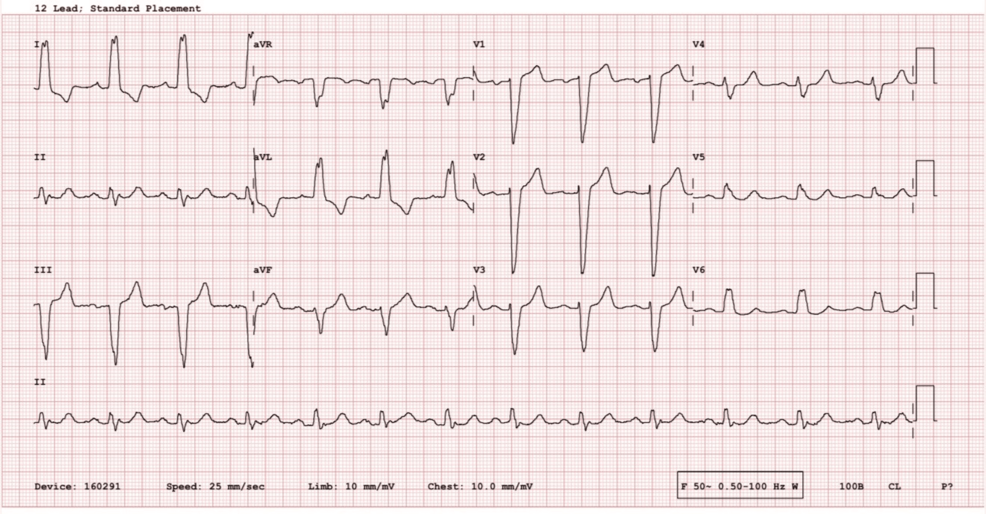
Ventricular standstill caused an 84-year-old female patient to collapse repeatedly while doctors initially attributed her symptoms to postural hypotension and benign paroxysmal positional vertigo, Cureus reported.
The patient presented to the acute medical unit following a fall with loss of consciousness and no recollection of the events. An initial 12-lead electrocardiogram demonstrated left bundle branch block, which was consistent with her pre-existing baseline conduction abnormality, with no new acute changes identified.
Medical teams initially deferred further cardiac investigations in favor of outpatient assessment because the electrocardiogram remained unchanged from baseline. Ongoing episodes of collapse prompted clinicians to order a 24-hour ambulatory Holter monitoring test, which captured a prolonged episode of ventricular standstill lasting 9.08 seconds.
Holter Monitoring Captures Transient Life-Threatening Arrhythmias
- Standard 12-lead electrocardiograms record cardiac electrical activity for only a few seconds, which frequently misses transient, intermittent arrhythmias.
- Patients with pre-existing conduction abnormalities like left bundle branch block can harbor life-threatening pauses that remain hidden during routine resting exams.
- Ambulatory cardiac monitoring successfully captured the 9.08-second ventricular standstill and led to urgent permanent pacemaker implantation.
Ventricular standstill represents a rare and potentially life-threatening cardiac conduction disturbance characterized by the absence of ventricular depolarization despite ongoing atrial electrical activity. This electrical failure halts effective ventricular contraction, which can quickly trigger cerebral hypoperfusion, presyncope, syncope, or complete hemodynamic collapse.
During her inpatient stay, she sustained a second fall that resulted in an acute right frontoparietal subdural hematoma confirmed by computed tomography of the head.
Bedside vestibular assessments pointed toward benign paroxysmal positional vertigo, while blood pressure measurements revealed a postural drop from 118/70 mmHg lying down to 90/60 mmHg standing with associated light-headedness. These findings initially directed clinical attention away from primary electrical cardiac failure.
Previous medical literature shows the variable and unpredictable nature of prolonged cardiac pauses. Stern and Tzivoni documented episodes of atrial and ventricular standstill lasting up to 20 seconds during sleep, noting that a 19-second pause during daily activity caused dizziness without a total loss of consciousness.
Following the Holter monitor detection at 13:21 hours, the medical team urgently referred the patient to cardiology for permanent pacemaker implantation. The procedure successfully resolved her symptoms, and she experienced no further episodes of dizziness or collapse before being discharged home in a stable condition.
Seek Medical Evaluation for Recurrent Syncope or Dizziness
Patients presenting with recurrent unexplained syncope, sudden falls, or presyncope should never rely on a single resting electrocardiogram to rule out cardiac disease. Individuals with pre-existing conduction delays, such as left bundle branch block or bifascicular blocks, require rigorous ambulatory or inpatient rhythm monitoring when symptoms persist.
Immediate medical evaluation in an emergency setting is warranted whenever a patient experiences abrupt loss of consciousness, persistent dizziness accompanied by bradycardia, or signs of hemodynamic compromise. Deferring cardiac investigation in favor of outpatient care carries severe risks when intermittent high-grade heart blocks remain undiagnosed.
Clinical guidelines from the European Society of Cardiology recommend selecting monitoring modalities based entirely on symptom frequency and the clinical suspicion of an arrhythmic etiology. Implantable loop recorders or prolonged external event monitors remain critical tools for capturing infrequent, transient conduction failures that evade standard 24-hour Holter recordings.
| Clinical Parameter | Initial Assessment | Post-Holter Findings |
|---|---|---|
| Diagnostic Tool | Resting 12-Lead ECG | 24-Hour Ambulatory Holter |
| Identified Rhythm | Baseline Left Bundle Branch Block | 9.08-Second Ventricular Standstill |
| Initial Working Diagnosis | Postural Hypotension & BPPV | Severe Bradyarrhythmia / Heart Block |
| Intervention | Outpatient Referral Deferred | Permanent Pacemaker Implantation |
This case establishes that a baseline electrocardiogram showing unchanged chronic conduction abnormalities must not provide false clinical reassurance. Clinicians must maintain a high index of suspicion for intermittent arrhythmias in patients with unexplained falls to prevent catastrophic outcomes.
References
- Cureus: Beyond Known Left Bundle Branch Block: Ventricular Standstill Revealed by Ambulatory ECG Monitoring.
- European Society of Cardiology (ESC): 2018 Guidelines for the Diagnosis and Management of Syncope.
- CRYSTAL-AF Trial: Long-Term Continuous Monitoring for Atrial Fibrillation in Cryptogenic Stroke.
