
France has approved CAR-T cell therapy for thousands of blood-cancer patients, but nearly half of the country’s authorized treatment centers say they cannot keep up.
A national review by the National Cancer Institute (INCa) found 5,370 patients treated by February 2025 — and 46% of centers unable to absorb demand within acceptable delays.
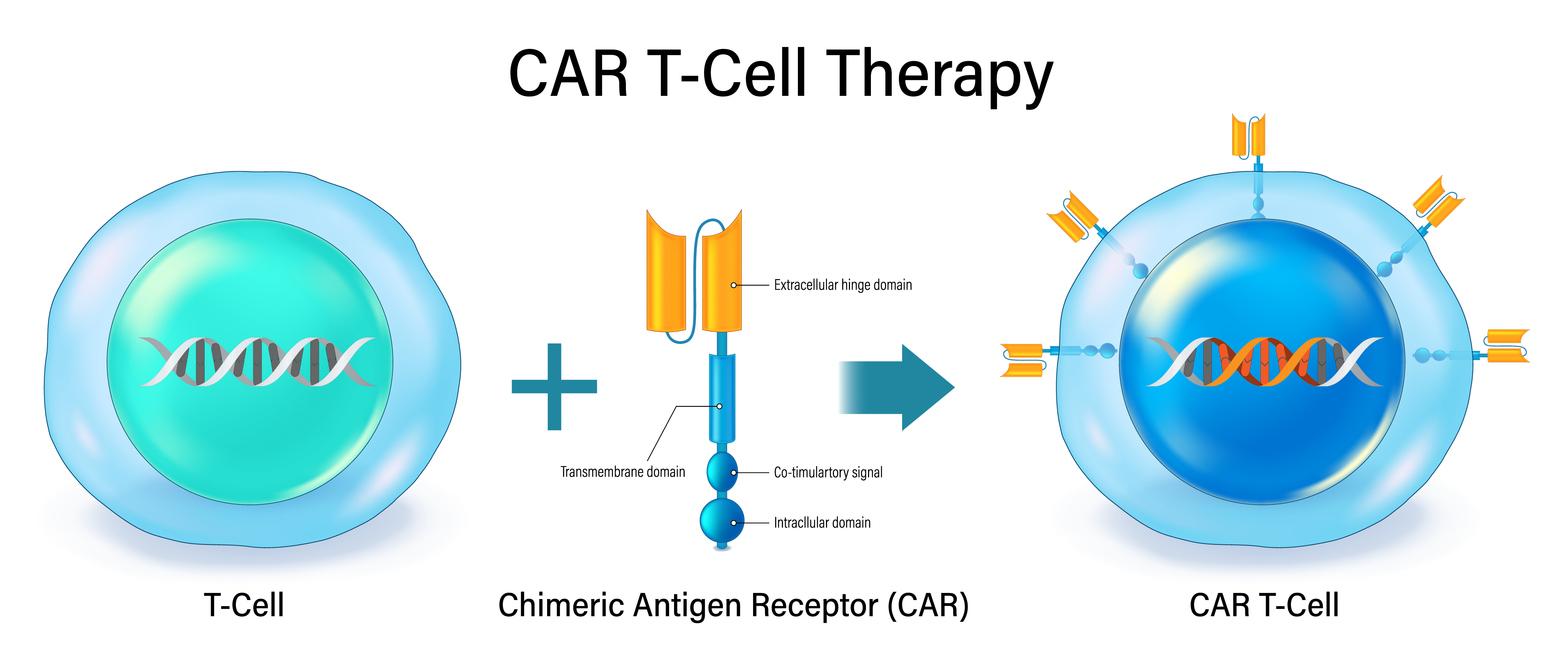
The bottleneck is not scientific. It is beds, staff, and logistics. CAR-T therapy — short for chimeric antigen receptor T-cell therapy — works by removing a patient’s own T lymphocytes (immune cells), genetically engineering them to recognize tumor cells, and reinfusing them after a round of lymphodepleting chemotherapy.
The cells are manufactured abroad over four to six weeks, and that manufacturing time has not shortened. INCa tallied the active patient file at 5,852 people by the end of 2025, with monthly treatments projected to reach 200 to 250 by 2027.
In Plain English: The Clinical Takeaway
- CAR-T is a personalized infusion of your own reprogrammed immune cells — not a daily drug — and it is proven effective in several blood cancers.
- Waiting is the risk: median delays from treatment decision to infusion run 55 to 66 days for second-line diffuse large B-cell lymphoma, and up to 142 days for multiple myeloma in some centers.
- Access in France depends heavily on where you live and which beds are free — not just on whether the therapy is approved and reimbursed.
French centers face uneven access
CAR-T access in France has grown fast. Five sites treated patients in 2018; forty qualified centers existed by 2025, with more openings planned. Monthly treatments rose from about twenty in 2020 to more than one hundred in 2024.
But the map is uneven. University hospitals (CHU) carry 88% of activity, and one-third of sites perform more than 75% of treatments. Île-de-France has one center per 1.2 million residents; Occitanie has one per 3.1 million.
Pediatric care is even more concentrated. Only 110 children were treated between 2018 and the end of 2024, with at most four injections per month nationwide. Hôpital Robert Debré and the CHU de Montpellier each handled 32% of pediatric activity in 2024, with the technique spreading gradually to Nancy and Marseille, according to Fréquence médicale.
Where the pipeline breaks: apheresis, pharmacies, and beds
Drawing on the DESCAR-T, PMSI and Oncology Pipeline databases together with an INCa national enquête conducted during the summer of 2025 across all authorized centers and the regional health agencies, the review identifies friction points throughout the entire pathway. It also assessed application of the June 28, 2024 decree that governs the therapy’s legal framework.
The cell-collection step — leukapheresis — is outsourced in 40% of centers, most often to the French Blood Establishment (Établissement français du sang), whose units lack dedicated CAR-T staff, pediatric expertise, and equipment. 25% of centres déplorent en outre des créneaux de production trop tardifs en cas de maladie agressive. A quarter of establishments (26%) also report recurring difficulty rapidly accepting patients referred from peripheral centers.
Hospital pharmacies are under their own kind of pressure: for one in four establishments (26%), directing patients arriving from peripheral centers toward the right facility quickly proves to be a recurring challenge. During the weeks of manufacturing, the injecting center guarantees bridging therapy in only 42% of cases, and 14% of centers outsource lymphodepletion chemotherapy to the patient’s original hospital for lack of beds.
Bed capacity is the hardest constraint. In 2024, CAR-T activity consumed nearly 30,000 hospitalization days — the equivalent of 118 to 148 permanently occupied beds, roughly forty in Île-de-France and twenty in Auvergne-Rhône-Alpes. Bed availability limits activity at 54% of centers and causes delays at 26%. With human resources under strain as the main driver, 46% of establishments judge themselves unable to take in their entire active caseload within acceptable timeframes.
Efficacy in hematologic malignancies and ongoing research
Efficacy is established in several hematologic malignancies: diffuse large B-cell lymphoma, follicular lymphoma, mantle cell lymphoma, acute lymphoblastic leukemia, and multiple myeloma. Evaluation continues in solid tumors and autoimmune diseases.
Of the 44 phase III trials, nearly all target hematologic cancers (42) — chiefly non-Hodgkin lymphomas and multiple myeloma — and half assess CAR-T products already on the market. Of the 28 phase II trials, 17 involve solid tumors (lung, ovarian, pancreatic, colorectal) and 11 hematologic indications, with 33 trials registered in 2025, according to Mdedge.
Indications skew heavily toward lymphoma. Diffuse large B-cell lymphoma in third line or beyond accounts for 41% of uses, the same lymphoma in second line 24%, and multiple myeloma 18% — for which idecabtagene vicleucel is currently the only available option.
| Indicator (France) | Figure | Period / comparison |
|---|---|---|
| Patients treated (cumulative) | 5,370 | By February 2025 (INCa) |
| Active patient file | 5,852 | End of 2025 (INCa) |
| Qualified centers | 5 → 40 | 2018 → 2025 |
| Centers unable to absorb demand in acceptable delays | 46% | 2025 survey |
| Hospitalization days consumed | ~30,000 (118–148 permanent beds) | 2024 |
Why regulatory approval was never the whole battle
The French case illustrates a gap other health systems are also confronting. Even once the Transparency Commission has issued its validation and the price negotiations between the Comité économique des produits de santé and the manufacturer have concluded, guaranteeing that every patient can access a breakthrough innovation is not assured. Il faut encore que la logistique suive, surtout lorsqu’elle est complexe.
Other wrinkles compound the strain. Cryoconservation of the cell collection — required for some products such as tisagenlecleucel — offers flexibility that fresh-collection CAR-T products do not.
Who qualifies for CAR-T therapy
CAR-T therapy is not for everyone. Eligibility is decided case by case in multidisciplinary tumor-board meetings (referred to in France as RCP), and the approved indications are limited to specific relapsed or refractory blood cancers after prior lines of treatment have failed.
Emergency plan, or structural fix?
Faudrait-il pour cette thématique lancer un nouveau plan d’urgence ? The INCa projections make the stakes plain: 200 to 250 new patients per month by 2027, roughly double the 2024 volume, against a system where 46% of centers already say they cannot absorb their caseload within acceptable delays. Staffing shortages — not science, not funding approval — are the named obstacle.
Until capacity catches up, the gap between what French medicine can manufacture and what its hospitals can deliver remains the story’s quiet headline: a therapy proven in peer-reviewed trials, reimbursed by the state, and still out of timely reach for too many of the patients it was designed for.
References
- Fréquence médicale — report on INCa’s national review of CAR-T access in France (2019–2025 analysis, DESCAR-T, PMSI, and Oncology Pipeline data)
- Mdedge — coverage of INCa findings on CAR-T cell treatment capacity in France
- Institut national du cancer (INCa) — national survey of authorized CAR-T centers and regional health agencies, summer 2025
- Arrêté du 28 juin 2024 — French regulatory framework governing CAR-T therapy
Treatment decisions must be made with a qualified oncologist or hematologist.
