
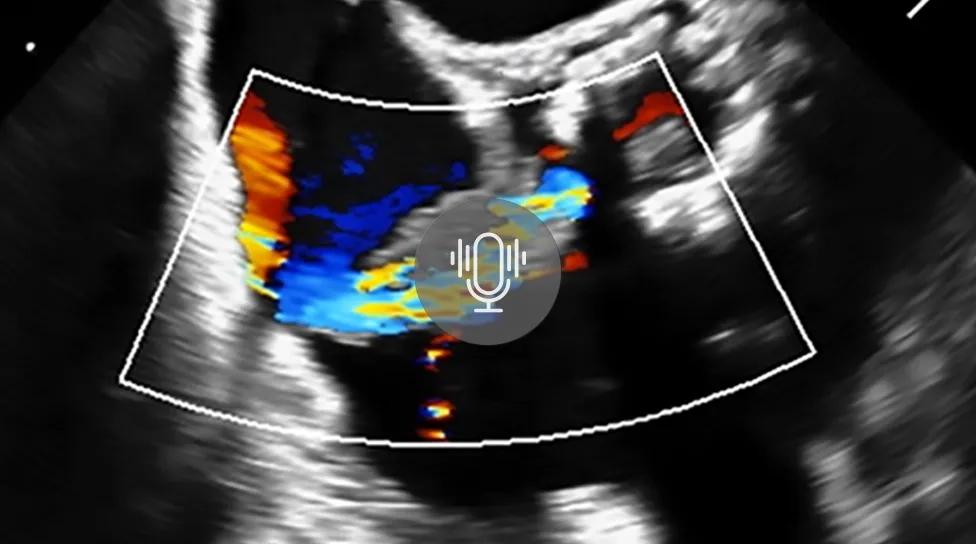
When a heart team encounters a patient with aortic valve endocarditis, time is of the essence more than in many other care scenarios, Consult QD reported.
Managing complex aortic valve endocarditis requires rapid clinical evaluation to balance surgical urgency with safety. When a vegetation burden is large, patients face risks of uncontrolled infection, detached emboli leading to stroke, heart failure from severe aortic valve regurgitation, and abscess formation that can cause atrioventricular block, according to Cleveland Clinic.
“When we see these patients, we need to quickly assess who requires urgent and elevated care due to risks like these,” Milind Desai, MD, MBA, Medical Director of Cleveland Clinic’s Aorta Center, told Consult QD. “These are the types of red flags that will send me to the office of one of my cardiac surgeon colleagues right away.”
Dr. Desai discussed contemporary management strategies for complex aortic valve endocarditis with colleague Per Wierup, MD, PhD, in a recent 13-minute episode of Cleveland Clinic’s Cardiac Consult podcast. The specialists outlined initial evaluation protocols, surgical timing, and three leading operative approaches based on individual patient anatomy.
“Yes, it’s a pretty logical sequence of three options for all our surgeons here, who are experienced in doing repairs of aortic, mitral and tricuspid valves,” Dr. Wierup told Consult QD.
The primary option is native valve repair, performed when patients present early and the infection remains localized. Surgeons remove the infected portion and reconstruct the affected leaflet to preserve natural valve function.
When the valve is heavily damaged but the infection remains strictly confined to the leaflets, a tissue prosthesis is typically utilized. This approach avoids the need for long-term anticoagulation therapy, which carries risks of brain bleeds, Consult QD reported.
The third option addresses cases where the infection has spread beyond the native valve to form an abscess. In these instances, surgeons deploy a homograft tissue structure to manage extensive tissue destruction and resist reinfection.
Addressing Double-Valve Endocarditis
Specialists also evaluate whether patients require a Commando operation during double-valve endocarditis involving both the aortic and mitral valves. This procedure is indicated when infection affects the curtain separating the two structures, requiring precise reconstruction using bovine pericardium.
“The Commando can be used in cases of double-valve endocarditis involving the aortic and mitral valves when there is infection in the curtain between the two valves,” Dr. Wierup told Consult QD. “You open up the area between the valves, you remove the infection and you reconstruct the curtain with bovine pericardium. Then you place the mitral valve prosthesis and aortic valve prosthesis or a homograft.”
Dr. Wierup said that while he performed many Commando procedures earlier in his career, experience allows surgeons to avoid the extensive operation in less destructive cases by utilizing local tissue reconstruction.
Milind Desai, MD, MBA, serves as Vice-Chair of Education and CME at the Miller Family Heart, Vascular & Thoracic Institute and Director of Clinical Operations for the Tomsich Department of Cardiovascular Medicine.
He holds the Haslam Family Endowed Chair in Cardiovascular Medicine and co-directs the Cardiovascular Imaging Laboratories for Cardiac CT and MRI. Desai earned an MBA from the University of Tennessee Haslam College of Business in 2020 and completed fellowships at Brigham & Women’s Hospital and Johns Hopkins University School of Medicine.
Time Critical for Aortic Valve Complications
- Time is Critical: Large vegetations or abscesses on the aortic valve can quickly trigger severe complications, including strokes, heart failure, or dangerous disruptions in heart rhythm.
- Tailored Interventions: Surgical teams choose between native valve repair, tissue valve replacement, or homograft reconstruction depending on how far the infection has spread.
- Intraoperative Judgment: While advanced imaging guides initial planning, a surgeon’s real-time visualization of the anatomy during the operation remains essential for the best outcomes.
“That’s an important point, because this is where the value of a surgical team with the full spectrum of expertise comes into play,” Dr. Desai told Consult QD. “This is never a one-size-fits-all situation. You have to tailor the approach to a given individual and the given findings.”
| Infection Extent | Preferred Surgical Approach | Primary Clinical Rationale |
|---|---|---|
| Localized Leaflet Infection | Valve Repair | Preserves native valve function and avoids artificial prostheses. |
| Extensive Leaflet Damage | Tissue Valve Replacement | Avoids long-term anticoagulation therapy and associated bleeding risks. |
| Abscess Formation | Homograft Implantation | Manages tissue destruction and provides high resistance to reinfection. |
Keep reading
- Medscape Collects Doctors’ Accounts of Funny Patient Remarks
- Texas Execution Takes 63 Minutes as Staff Struggle to Find Vein
- Russian Billionaires Worth $700B Quietly Prepare for post-Putin Era, Experts Say (world-today-news.com)
- Cleveland Clinic Tests Virtual Reality for Cancer Distress (newsdirectory3.com)
