
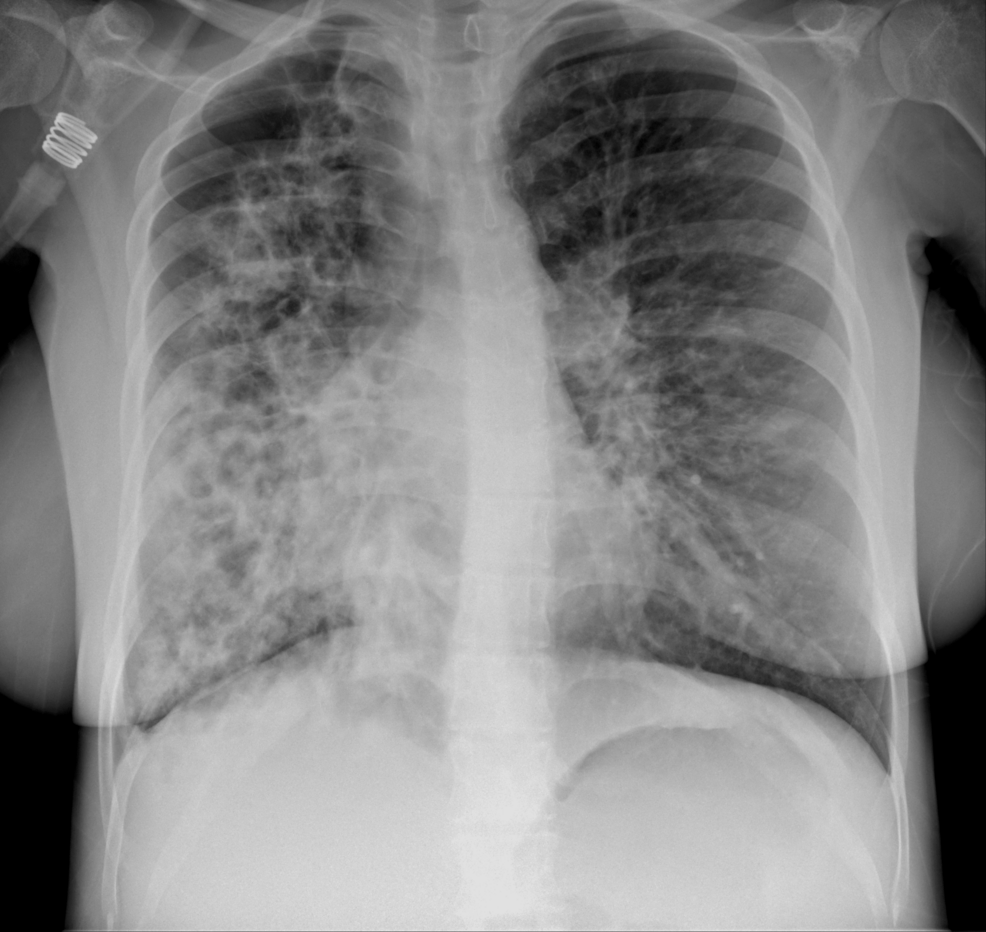
An 18-year-old primigravida with advanced cystic fibrosis and acute hypoxaemic respiratory failure successfully underwent urgent caesarean delivery using combined spinal-epidural anaesthesia while maintaining high-flow nasal cannula support, according to a case report published in Cureus.
Managing anaesthesia during pregnancy in patients with severe pulmonary impairment presents profound clinical obstacles. The physiological demands of gestation reduce functional residual capacity and elevate oxygen consumption. When acute respiratory failure complicates advanced lung disease, clinicians must carefully balance maternal ventilation requirements against the risks of airway instrumentation.
- Avoiding Intubation: Combined spinal-epidural (CSE) anaesthesia allows regional pain control while letting the patient breathe spontaneously, bypassing the respiratory risks associated with general anaesthesia.
- High-Flow Support: High-flow nasal cannula (HFNC) therapy delivers heated and humidified oxygen at high rates, helping patients maintain adequate oxygen saturation during acute pulmonary exacerbations.
- Multidisciplinary Care: Complex high-risk pregnancies require close coordination between obstetricians, anaesthesiologists, pulmonologists, and intensive care teams to manage acute decompensation.
Patient History of Cystic Fibrosis and Respiratory Status
The patient was diagnosed with cystic fibrosis at two years of age and was homozygous for the F508del variant, as detailed by Marques, Vicetro, and Viana in Cureus. Her disease course involved chronic airway colonisation with Methicillin-sensitive Staphylococcus aureus and Achromobacter xylosoxidans, exocrine pancreatic insufficiency, and ongoing evaluation for lung transplantation.
She had received triple cystic fibrosis transmembrane conductance regulator (CFTR) modulator therapy with elexacaftor/tezacaftor/ivacaftor for several years. Her history also included a previous spontaneous right-sided pneumothorax and frequent pulmonary exacerbations.
At 33 weeks and 3 days of gestation, she was admitted for maternal and fetal surveillance. On Day 4 of the admission, she returned to the obstetric emergency department experiencing dyspnoea on minimal exertion and uterine contractions.
An evaluation of her arterial blood gases demonstrated significant hypoxaemia and normal carbon dioxide levels, despite the administration of supplemental oxygen through a Venturi mask delivering an FiO₂ of 0.40. A chest radiograph demonstrated worsening infiltrates involving the right lower lobe and the posterior segment of the right upper lobe.
As her oxygen demands escalated, clinicians initiated high-flow nasal cannula therapy at 45 L/min and an FiO₂ of 0.50, which required upward titration to 0.75 to maintain peripheral oxygen saturation above 90%. She was transferred to the intensive care unit, where a diagnosis of lower respiratory tract infection with acute hypoxaemic respiratory failure was established, and empirical piperacillin/tazobactam therapy was started.
Neuraxial Management of Labour and Delivery
On Day 6 of admission, corresponding to 34 weeks and 1 day of gestation, progressive preterm labour prompted an urgent caesarean delivery. Although tocolysis with nifedipine had been administered, cervical dilatation progressed to 3 cm with 80% effacement. To avoid general anaesthesia, tracheal intubation, and positive-pressure mechanical ventilation, the clinical team selected combined spinal-epidural anaesthesia.
The regional anaesthesia technique utilised intrathecal hyperbaric bupivacaine and sufentanil, supplemented by epidural ropivacaine administration to establish a stable sensory block. High-flow nasal cannula support remained active throughout the surgical procedure. The intervention proceeded without intraoperative respiratory deterioration or haemodynamic instability. The neonate delivered successfully, achieving Apgar scores of 9, 9, and 9 at one, five, and ten minutes, respectively.
Following surgery, the patient returned to the intensive care unit for close respiratory monitoring. Her supplemental oxygen requirements steadily declined, and she was discharged from the hospital on postoperative day seven breathing room air without supplemental oxygen.
| Clinical Parameter | Preoperative / Admission Value | Postoperative Status |
|---|---|---|
| Gestational Age | 34 weeks and 1 day (Delivery) | Postoperative Day 7 (Discharge) |
| Respiratory Support | HFNC (FiO₂ 0.75, Flow 45 L/min) | Room air (No supplemental oxygen) |
Conditions That Contraindicate Neuraxial Anaesthesia
Neuraxial anaesthesia techniques like combined spinal-epidural are contraindicated in patients with uncorrected coagulopathies, severe systemic infection at the puncture site, elevated intracranial pressure, or patient refusal. Individuals with advanced pulmonary disease experiencing acute respiratory decline require immediate evaluation by multidisciplinary specialist teams.
Feasibility of Maintaining Respiratory Support During Obstetric Procedures
While single-case observations cannot establish the definitive superiority of neuraxial techniques over general anaesthesia across all patient profiles, this report highlights the feasibility of maintaining non-invasive respiratory support during high-risk obstetric procedures. The findings were previously presented as a poster at Euroanaesthesia 2026 in Rotterdam.
References
- Marques D, Vicetro J, Viana P. Combined Spinal-Epidural Anaesthesia for Caesarean Delivery in a Parturient With Advanced Cystic Fibrosis and Acute Hypoxaemic Respiratory Failure: A Case Report. Cureus. 2026;18(11):e119318. doi:10.7759/cureus.119318.
- American Society of Anesthesiologists Practice Guidelines for Obstetric Anesthesia. Anesthesiology.
- Recent advances in obstetric regional anaesthesia and critical care management. PubMed.
Disclaimer: This article is intended for informational and educational purposes based on published peer-reviewed medical literature. It does not constitute formal medical advice, diagnosis, or treatment planning. Always consult qualified healthcare professionals regarding specific medical conditions or pregnancy-related care.
