
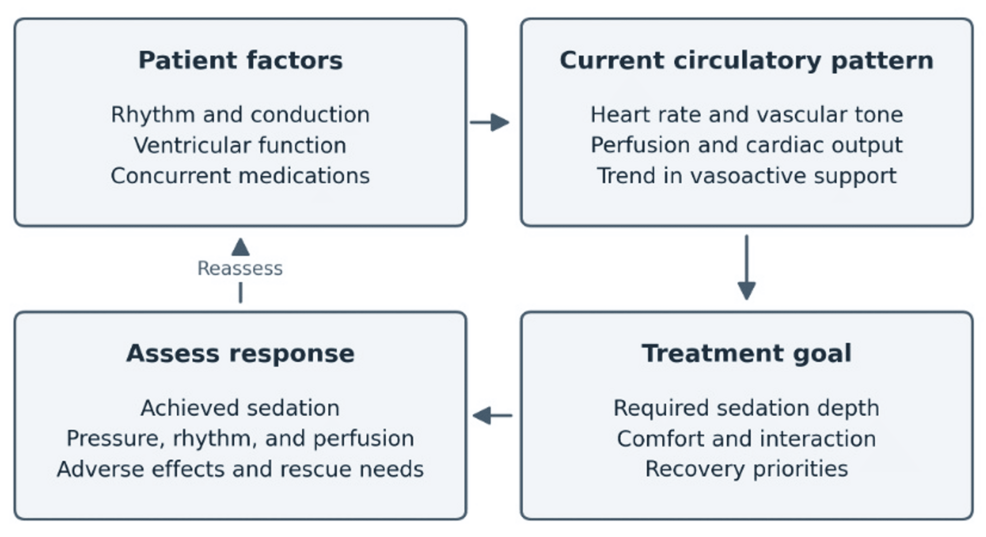
Published in this week’s medical literature, a narrative review in Cureus evaluates the hemodynamic safety and recovery outcomes of dexmedetomidine versus propofol for early postoperative sedation following adult cardiac surgery. The analysis contrasts how differing pharmacological profiles, dosing regimens, and outcome definitions shape clinical interpretation during mechanical ventilation and weaning.
In Plain English: The Clinical Takeaway
- Sedation Choices: Both dexmedetomidine and propofol are widely used to keep patients comfortable during early recovery from heart surgery, but they affect the cardiovascular and nervous systems differently.
- Hemodynamic Trade-offs: Evidence shows dexmedetomidine is linked to a higher incidence of low blood pressure (hypotension) and slow heart rate (bradycardia), while propofol can reduce overall vascular tone and cardiovascular performance.
- Recovery Milestones: While dexmedetomidine use is frequently associated with reduced vasopressor requirements and lower rates of delirium in specific comparative trials, researchers emphasize that treatment protocols and study designs vary widely.
Navigating Postoperative Sedation Risks After Cardiac Procedures
More than two million cardiac surgeries are performed annually worldwide to treat ischemic heart disease, congenital malformations, and valvular disorders, as reported in comparative data from PMC. Managing patients immediately following cardiopulmonary bypass requires precise hemodynamic control. Myocardial dysfunction, fluid shifts, and altered vascular tone frequently threaten circulatory stability during this critical window. Clinicians must balance patient comfort, ventilator tolerance, and the ability to rapidly assess neurological status against the physiological toll of sedative agents.
Propofol allows rapid titration across various sedation depths, yet its vasodilatory mechanism can suppress venous return and overall cardiovascular performance. Conversely, dexmedetomidine produces sedation through alpha-2-adrenoceptor activation, dampening central sympathetic activity while preserving relative respiratory function. However, this sympatholysis can provoke profound bradycardia and hypotension, particularly in patients whose cardiac output heavily relies on intrinsic heart rate or adrenergic support.
The narrative review in Cureus highlights that existing systematic reviews and randomized controlled trials frequently diverge in their findings due to heterogeneous treatment targets, loading protocols, and rescue medications. For instance, trials evaluated by researchers such as Djaiani et al. and Liu et al. demonstrated decreased delirium and atrial fibrillation rates associated with dexmedetomidine, but noted concurrent increases in hypotensive episodes. Systematic syntheses, including meta-analyses by Montaseri et al. and Sattar et al., underscore that recorded hypotension, vasopressor modifications, and extubation timelines must be treated as distinct clinical endpoints rather than interchangeable markers of safety.
Furthermore, broader perioperative investigations, such as the work by Turan et al. and Lei et al., examine adjunct dexmedetomidine strategies rather than direct replacements for propofol. These methodological differences complicate efforts to establish universal clinical superiority. Researchers emphasize that a lower heart rate does not automatically translate to superior tissue perfusion, nor does propofol’s known vasodilatory profile prove that dexmedetomidine entirely spares patients from circulatory depression.
Contraindications & When to Consult a Doctor
Patients with pre-existing conduction system disease, severe baseline bradycardia, or uncompensated heart failure may experience exaggerated sympatholytic responses when exposed to alpha-2 agonists like dexmedetomidine. Conversely, individuals with compromised vascular tone or sensitivity to myocardial depression require careful dose titration when receiving propofol. Clinicians must continuously monitor hemodynamic stability, vasopressor support, and cardiac rhythm during early postoperative recovery. Immediate medical evaluation is required if patients exhibit acute hemodynamic collapse, refractory hypotension, malignant arrhythmias, or sudden neurological decline following extubation.
Future Directions in Cardiovascular Anesthesia
As cardiac surgical volumes continue to rise globally, optimizing postoperative care protocols remains a central focus for critical care medicine. The current narrative review underscores the necessity for standardized outcome definitions and rigorous, prospective trial designs to clarify the distinct physiological impacts of sedative agents. Future investigations aiming to guide personalized anesthetic selection must account for baseline cardiovascular reserve, microcirculatory dynamics, and individual analgesic co-interventions.
References
- Hemodynamic effects of dexmedetomidine versus propofol in cardiac surgery: a systematic review and meta-analysis. BMC Anesthesiology.
- Montaseri et al. Systematic review and meta-analysis of hemodynamic outcomes comparing dexmedetomidine and propofol in cardiac surgery.
- Djaiani et al. Randomized trial evaluating postoperative ICU sedation and delirium endpoints.
- Subramaniam et al. Factorial randomized trial examining analgesic co-interventions and sedative exposure from chest closure.
