
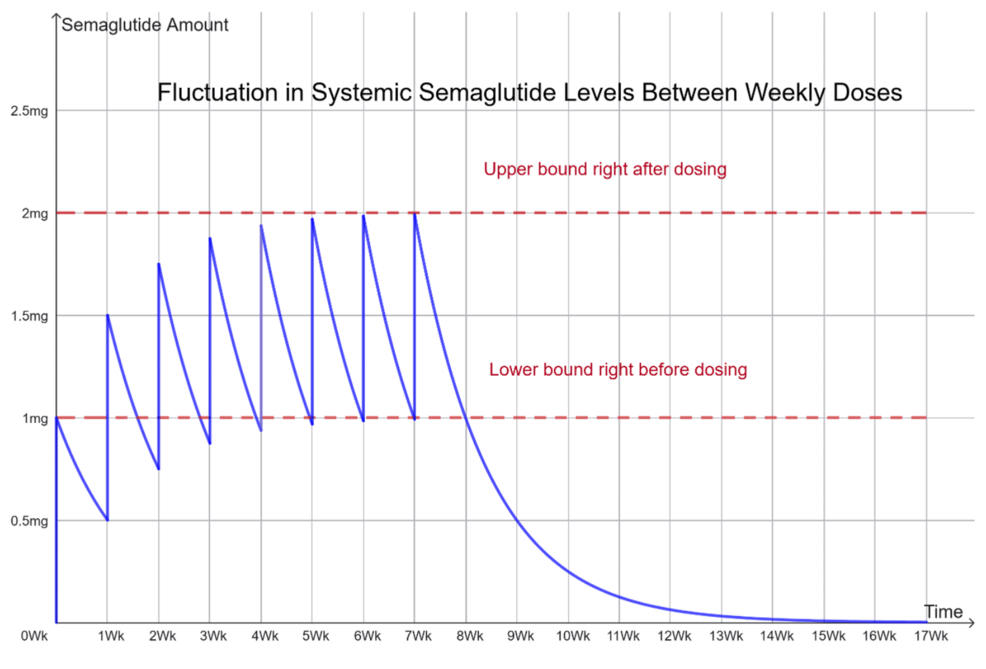
An emerging mathematical model published in Cureus proposes transitioning surgical patients from long-acting GLP-1 receptor agonists to shorter-acting agents four weeks prior to operations to curb residual gastric contents and aspiration risks.
The rising prevalence of glucagon-like peptide-1 receptor agonists creates a significant perioperative hurdle, given their impact on stomach emptying and the risk that gastric residue may remain during surgical anesthesia. In clinical practice, retained gastric contents are frequently observed in patients who continue GLP-1 RA therapy.
Even among individuals who have ceased GLP-1 RA usage ahead of their operation, preoperative stomach ultrasound sometimes reveals the presence of residual gastric material. Such findings indicate an increased risk of pulmonary aspiration and complicate perioperative management for anesthesiologists.
Drugs Delay Stomach Emptying During Anesthesia
- The Core Problem: Popular diabetes and weight-loss drugs delay stomach emptying, which can cause dangerous food or liquid leakage into the lungs during anesthesia.
- The Mathematical Proposal: Researchers modeled drug half-lives using geometric series to show how switching from a weekly injection to a daily short-acting drug could safely lower drug levels before surgery.
- What Remains Unknown: This is currently an untested theoretical schedule, and clinical trials are needed to prove whether it actually prevents stomach retention during procedures.
Developing a Dosing Strategy Using Pharmacokinetics
Beisel and C. Lee introduced a theoretical, pharmacokinetics-based approach intended to lower residual drug levels prior to surgery while cutting down on the time patients must pause their GLP-1 RA treatment.
Geometric series modeling, exponential drug elimination, and pharmacokinetic principles were used to develop the proposed schedule. The model accounts for the significant disparities in elimination half-lives among GLP-1 RAs, specifically liraglutide and semaglutide, to calculate how these drugs accumulate and clear over time.
Since the Food and Drug Administration granted approval for semaglutide in 2017, the drug has rapidly risen in popularity, becoming one of the most frequently prescribed medications. By 2023, semaglutide achieved the distinction of being the top-selling pharmaceutical product globally.
Regarding usage data, the numbers are just as remarkable: roughly 12% of the U.S. population has utilized semaglutide, with an estimated 6% currently on the medication. These statistics highlight the broad interest and clinical utility of the drug, particularly in a nation where one in three adults qualifies as obese, a state defined as having a body mass index over 30.
Pharmacologically, semaglutide is classified as a glucagon-like peptide-1 receptor agonist. GLP-1 is an incretin hormone produced by L cells in the colon and distal ileum following nutrient consumption.
Its physiological functions are diverse: GLP-1 boosts insulin production in a glucose-dependent manner, suppresses glucagon secretion, slows the emptying of the stomach, and reduces both fluid and food intake, all of which work together to aid in weight loss and blood sugar management.
Clinical Evolution of Perioperative Guidelines
As the use of GLP-1 RAs expands, so does the volume of patients undergoing surgical procedures while taking these medications. This trend has created new perioperative hurdles, specifically the necessity of balancing the risk of aspiration caused by delayed gastric emptying against the metabolic and clinical downsides of pausing the therapy. Recognizing these concerns, the American Society of Anesthesiologists issued consensus guidance on June 19, 2023.
The guidance advised that individuals taking daily GLP-1 versions should skip their dose on the day of their procedure, while those on weekly versions should stop the medication seven days before surgery.
Decisions regarding intraoperative care should be based on symptoms: if a patient reports gastrointestinal issues on the day of the procedure, the operation should be delayed. More recently, on October 29, 2024, updated clinical guidance was released through a multi-society consensus.
| Guidance Source | Date Released | Key Recommendation |
|---|---|---|
| American Society of Anesthesiologists | June 19, 2023 | Withhold daily formulations on surgery day; withhold weekly formulations for seven days prior. |
| Multi-Society Consensus | October 29, 2024 | Most patients may continue therapy, but high-risk individuals should follow a clear-liquid diet for 24 hours pre-op. |
The multi-society update suggests that most patients can safely continue GLP-1 therapy in the perioperative period. Nevertheless, a more cautious approach is warranted for high-risk individuals. For these specific patients, adhering to a clear-liquid diet for 24 hours before the procedure is advised.
Evaluating the Proposed Bridging Strategy
Based on mathematical modeling, the authors propose a potential strategy of transitioning patients from a longer-half-life agent, such as semaglutide, to a shorter-half-life agent, such as liraglutide, approximately four weeks before surgery. This should be followed by discontinuation of liraglutide approximately two days before surgery.
This method utilizes the faster elimination half-life of liraglutide, potentially allowing for a more significant drop in residual drug levels before surgery while reducing the length of time the patient is off their medication.
A geometric series refers to a progression of values where each subsequent figure is determined by multiplying the previous one by a fixed common ratio. This mathematical trait makes it effective for tracking values that drop by a consistent percentage over specific time frames.
During the accumulation phase, the GLP-1 RA level can be modeled with a geometric series. One compartment model was chosen so volume of distribution can be omitted, since drug amount and concentration are linearly related.
Semaglutide, with a half-life of one week, and liraglutide, with a half-life of 13 hours, served as examples in this mathematical model. The suggested plan entails switching from semaglutide to liraglutide about four weeks prior to the operation, then stopping the liraglutide two days before the procedure. This interval corresponds to approximately four elimination half-lives of liraglutide, theoretically allowing a substantial reduction in circulating drug levels.
High-Risk Criteria Requiring Careful Screening
High-risk criteria requiring careful screening include recent initiation of GLP-1 therapy, current dose escalation occurring over four to eight weeks, use of high-dose regimens, and the presence of significant gastrointestinal symptoms.
Additional risk factors include comorbidities such as bowel dysmotility, gastroparesis, scleroderma, amyloidosis, systemic lupus erythematosus, or Parkinson’s disease. Clinicians should screen for symptoms like constipation, dyspepsia, abdominal pain, nausea, or vomiting, and inquire about recent dosage changes within the last three weeks.
Patients scheduled for surgery should immediately disclose their complete medication history to their surgical and anesthesia teams. If unexpected gastrointestinal symptoms arise during the preoperative window, or if a patient has continued taking a GLP-1 RA without adherence to standard holding intervals, immediate professional consultation is required to evaluate aspiration risk and determine whether procedural postponement is necessary.
Further clinical studies are needed to determine whether this pharmacokinetic bridging approach reduces residual gastric contents and perioperative aspiration risk and to evaluate its overall safety and efficacy in broader patient populations.
References
- Beisel K, Lee C. GLP-1 Receptor Agonists: Geometric Series, Exponential Decline, and a Hypothetical Preoperative Management Strategy. Cureus. 2026;18(11):e119766.
