
“I am more than lubrication,” said Melissa Shusterman, describing how doctors dismissed her menopausal symptoms.
Last month, the Pennsylvania state representative introduced a package of bills mandating insurance coverage for menopause care, becoming part of a movement that has produced more than 60 state bills in two years.
Shusterman had seen a gynecologist, a physical therapist, a chiropractor and a urologist for body aches, lethargy and brain fog — a state she described as feeling “not myself.” One physician handed her a lubricant after she had already explained that sex was not the problem. (“Have you seen my husband?” she quipped, the Guardian reported in its roundup of state menopause legislation.)
The Pennsylvania package, announced at a September state capitol rally with dozens of women behind her, would mandate insurance coverage for menopausal care, expand public education, extend Medicaid coverage for menopause treatment, add workplace protections for symptomatic workers and broaden coverage for related conditions such as osteoporosis and urinary tract infections. It is, the Guardian reported, one of the most ambitious menopause legislative packages in the country.
Why it matters now: almost half of American women aged 40 to 60 experienced menopausal symptoms last year, according to a recent federal study — yet only about 16% took any prescription medication for those symptoms, and just 31% of OB-GYN residency program directors said menopause training was included in their programs in a 2022 survey indexed on PubMed.
Finding a menopause-trained doctor
- Menopause symptoms — hot flashes, vaginal dryness, brain fog, joint aches — affect nearly half of women in midlife, but only a small fraction receive prescription treatment.
- Hormone therapy is now recommended by the American College of Obstetricians and Gynecologists as a first-line treatment for hot flashes, except in women with certain histories such as breast cancer.
- Finding a doctor trained in menopause management is often the hardest step; most residency programs do not teach it.
A 25-year shadow over hormone therapy
The legislative push is running against a decades-old clinical chill. In 1991, the National Institutes of Health launched the Women’s Health Initiative, a large trial measuring hormone therapy’s effects in menopause; by the late 1990s, hormone therapy had Lindsay-era pop-culture cachet, and model Lauren Hutton served as its public face, Jennifer Weiss-Wolf, author of the new book When in Menopause: A User’s Manual and Citizen’s Guide, told the Guardian.
In lay terms, hormone therapy replaces the estrogen (and sometimes progestogen) the ovaries stop producing — the mechanism of action underlying relief from hot flashes and vaginal dryness.

In 2002, the trial’s organizers abruptly stopped part of the study, announcing hormone therapy was associated with increased risks of breast cancer and heart disease. Prescribing collapsed: from about 27% of women with symptoms in 1999 to less than 2% in 2024, Weiss-Wolf writes in her book, according to testimony she submitted to the US Senate Aging Committee, a copy of which is posted on the committee’s site.
Newer non-hormonal options can relieve some symptoms, but costs can exceed $600 per month, and few states mandate insurance coverage for either approach.
The access gap lawmakers are trying to close
Even a diagnosis is hard to come by. Lauren Streicher, a clinical professor of obstetrics and gynecology at Northwestern University, told the Guardian that finding a doctor trained in menopause management “can be difficult or impossible.” The problem is worse, she said, in states where restrictive abortion laws have driven OB-GYNs out of practice: “There’s no one to give menopause care or do anything else.”
The taboo itself is a policy subject. “It is still so taboo,” said Cheryl Bergman, executive director of the Michigan Women’s Commission, which released a report on menopause policy in March. “Most of the time I bring the conversation up with men, even progressive men, they take a step back. They just literally step away from it.”
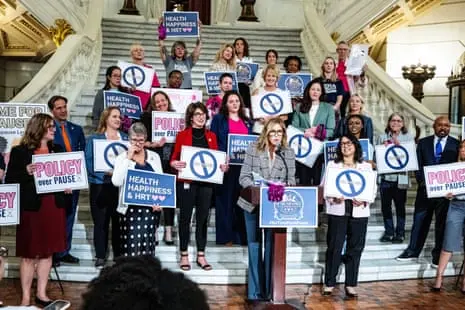
Over the last two years, more than 60 bills on menopause education, insurance coverage or workplace accommodations have been introduced at the state level, Weiss-Wolf said; at least 21 have passed. Louisiana was among the first states to mandate insurance coverage for menopause care, in 2024, and measures have passed from Rhode Island to Utah — several with bipartisan support, including in red states.
| Measure | Figure | Period |
|---|---|---|
| Women 40–60 with menopausal symptoms | Almost half | past year (federal CDC study) |
| Took prescription medication for symptoms | ~16% | same federal study |
| Women prescribed hormone therapy | ~27% → under 2% | 1999 → 2024 (Weiss-Wolf) |
| OB-GYN residency programs including menopause training | 31% | 2022 survey |
| State menopause bills introduced / passed | 60+ / at least 21 | past two years (Weiss-Wolf) |
Women behind the wave
The movement’s energy, lawmakers say, comes from lived experience. Celebrity moments have helped: Michelle Obama interviewed obstetrician and menopause practitioner Sharon Malone on her podcast in 2020; Oprah Winfrey hosted a panel with Drew Barrymore and Maria Shriver in 2023; and in May 2024, Halle Berry joined senators at the US Capitol to press for federal research funding. “I’m in menopause, OK?” she shouted.
“Most of us are millennials and gen Xers, raising their voices because they’re experiencing something in their own lives,” said Pennsylvania state representative Morgan Cephas, who is sponsoring the Medicaid-expansion and workplace-protection bills. “We’re also in the sandwich generation. We’re raising kids, but we’re also taking care of our parents.”
Cephas links the fight to reproductive health broadly. “The fall of Roe was a nail in the coffin for us because now we’re looking at our children and understanding that they have less reproductive rights than our parents had,” she told the Guardian. While protecting abortion access, she said, “we begin thinking of the entire continuum of healthcare for women.”
Economics is part of the case too. “Women get sidelined just as they’re reaching the pinnacle of their potential in their chosen work” because of misdiagnosed or untreated symptoms, Shusterman said.
Where the outlets diverge
On the prognosis for Pennsylvania, Cephas told the Guardian that with Democrats having flipped the state Senate and holding the House and governorship, “I believe we’ll see a good number of these bills fly through.”
Consulting a doctor for menopause treatment
The last word goes to Shusterman: “People want to be seen. We need to be seen and cared for, because a lot of times women are the ones caring for everyone else.”
References
- Michigan Women’s Commission menopause policy report.
