
JDentalCare's Maxilla-For-All cut the share of patients reporting oral discomfort from 69% to 21.8% in a one-year study of 53 patients published in 2025.
Implant maker JDentalCare is promoting Maxilla-For-All, a graftless treatment for severe upper-jaw bone loss, on the strength of a one-year study of 53 patients published in 2025.
The company describes it as a complete clinical system — tested implants, a guided digital workflow and a step-by-step surgical protocol with hands-on training — rather than a single device.
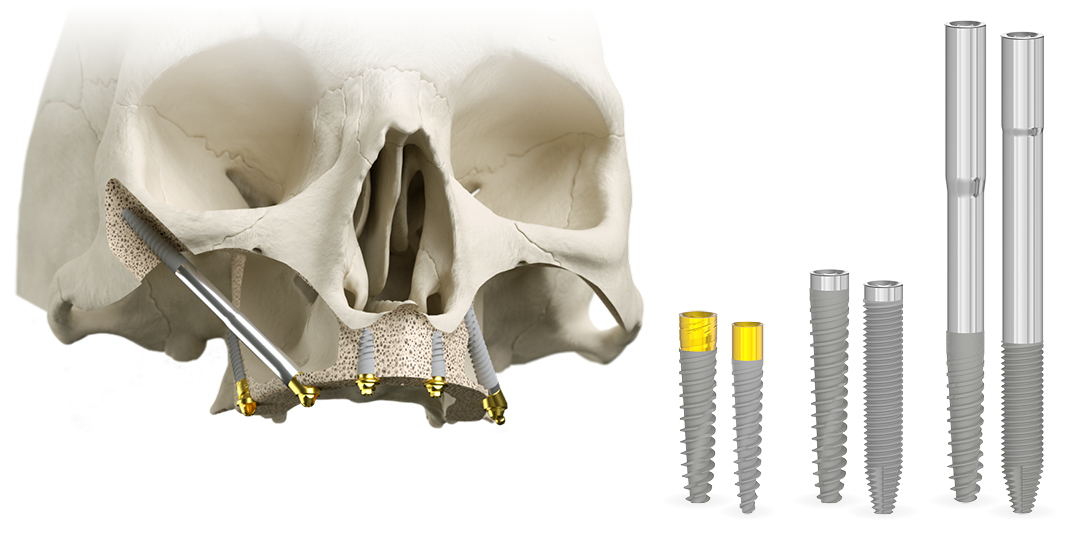
Severe atrophy of the maxilla, the upper jaw that carries the teeth, has historically pushed patients toward bone-grafting operations before implants can even be placed. Maxilla-For-All, JDentalCare reported, is built to skip that grafting stage by anchoring standard and long implants beyond the failed bone itself: in the pterygoid region behind the upper jaw, through the sinus, and into the zygoma, the cheekbone.
What separates this announcement from most product launches is the outcome measure. The study the company cites does not count implants placed; it counts how patients felt — about pain, function and their own appearance — before surgery and one year after.
What Graftless Means for Patients
- No graft operation first. The concept is designed for patients whose upper jaw has lost so much bone that conventional implants cannot hold, without a separate bone-grafting procedure and its recovery period.
- Anchors beyond the jaw. Surgeons using the protocol can place pterygoid, trans-sinus and zygomatic implants, engaging denser bone structures such as the cheekbone when the maxilla itself is too thin.
- Measured in patient-reported terms. The evidence uses two validated questionnaires — the OHIP-14, which scores oral health–related quality of life, and the PIDAQ-23, which scores the psychological and social impact of dental appearance.
Fifty-Three Patients, Twelve Months
Fifty-three patients treated with the system completed both questionnaires before surgery and again at 12 months. On the OHIP-14, the share of patients reporting oral discomfort fell from 69% to 21.8% over the year. On the PIDAQ-23, psychosocial discomfort — the distress patients associate with how their teeth and smile look — dropped from 44.7 to 6.8 on the scale.
Those are patient-reported outcomes, not a surgeon’s assessment. A score falling from 44.7 to 6.8 means that, one year on, patients on average reported distress about their dental appearance near the bottom of the scale where they had once clustered near the middle.
The Clinicians Behind the Data
Two of the study’s authors also appear in JDentalCare’s own testimonials endorsing the system. The announcement does not disclose the study’s funding.
“In my daily clinical practice, I only use solutions I trust completely. JDentalCare implants and surgical protocols enable me to treat even the most complex cases with greater predictability, stability, and confidence,” said Dr. Tommaso Grandi in a testimonial published by JDentalCare.
“JD pterygoid and zygomatic implants are a reliable solution for the treatment of severe maxillary atrophy. I appreciate their quality, predictable outcomes and ease of use. I recommend this system for its clinical versatility and long-term reliability,” said Dr. Matteo Giorgi in the same company series.
Both men speak from the operative side of the data: Grandi’s testimonial describes treating complex cases with the protocol, and Giorgi’s names the two long-implant types — pterygoid and zygomatic — that the published study also covers.
Where the Evidence Stops
The follow-up runs to 12 months, and the announcement presents no longer-term implant survival or complication figures beyond that point. That matters, because dental implants are judged over years, not months, and long implants placed in the cheekbone and sinus region carry their own learning curve for surgical teams.
Access, for now, runs through professionals. The company’s materials and offer for the protocol are addressed to dental practitioners only, with training built into the system — meaning a patient’s route to this treatment depends on finding a clinician who has been trained in it.
When This Surgery Is Not Advised
Candidacy for graftless full-arch treatment is an anatomy decision, made on imaging by a surgeon trained in the protocol — not one a brochure can settle. The published study reports outcomes for the 53 patients treated; the announcement does not list who was excluded from treatment or on what grounds.
Patients with severe upper-jaw bone loss who are considering implants should ask a qualified clinician directly whether their bone structure and general health fit a graftless approach, whether a conventional graft route would serve them as well, and what the published complication experience is for the specific implant types involved. Persistent pain, signs of infection around any implant, or sinus symptoms after upper-jaw surgery warrant prompt professional evaluation.
The Number That Stays With You
The sharpest single change in the study was not clinical but personal: psychosocial discomfort on the PIDAQ-23 fell from 44.7 to 6.8 in twelve months. Whether that gain holds over five or ten years is the question the published one-year data cannot yet answer.
References
- JDentalCare. “Maxilla For All: Full Arch Treatment” — protocol, clinical study summary and clinician testimonials.
This article is informational and does not replace consultation with a qualified dental or medical professional.
