
A new low-cost training phantom for a specialized chest pain block, described in Cureus, aims to improve procedural safety for emergency medicine trainees by simulating critical anatomical landmarks and potential hazards. The model, designed for the ultrasound-guided serratus anterior plane block (SAPB), uses common materials to create a realistic training environment without the high cost of commercial simulators, potentially accelerating competency in a technique proven to manage post-surgical pain.
SAPB's growing role in multimodal analgesia explains the need for such a training tool. As reported in Cureus, a randomised clinical trial demonstrated that adding an ultrasound-guided SAPB to protocolised rib-fracture care significantly increased the proportion of patients achieving a meaningful early reduction in pain and reduced in-hospital opioid use. This positions the block as an evidence-supported component of care rather than a universal replacement for other analgesic strategies. The challenge lies in mastering the procedure, which requires integrating complex sonoanatomy with precise needle control near vital structures like the thoracodorsal artery and the pleura.
Building a Low-Fidelity, High-Impact Training Model
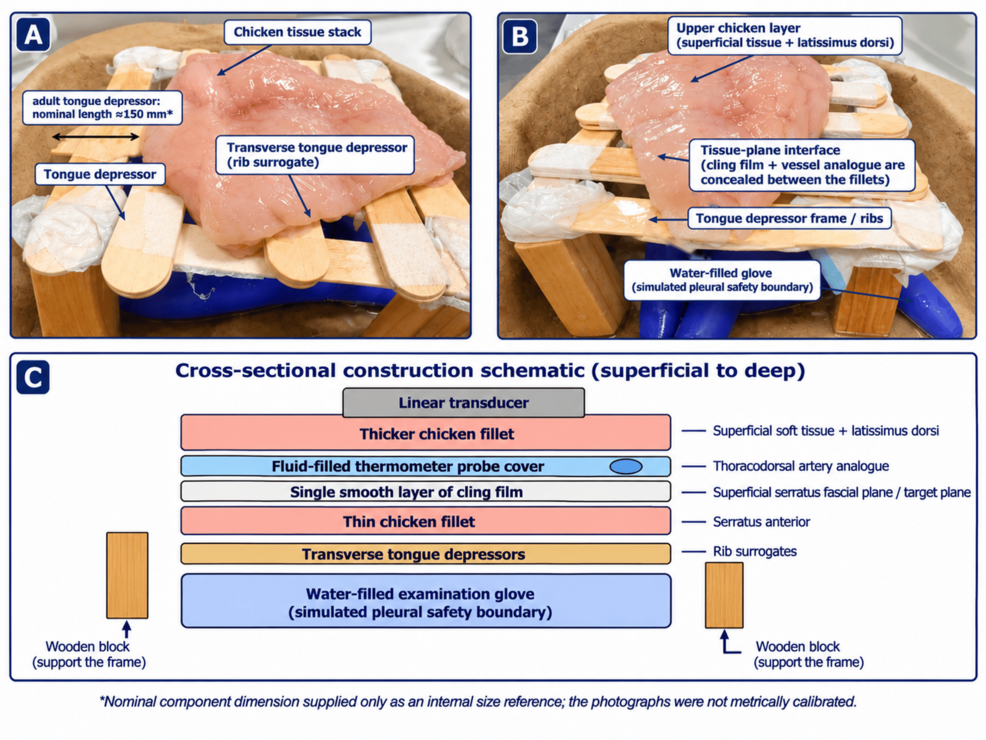
The design rationale behind this new phantom prioritizes accessibility and pragmatic safety features. The model’s evolution from foam and cardboard to its final form was driven by the need for better acoustic transmission and a rigid, water-tolerant platform. The final prototype, constructed from easily obtainable components, was evaluated in a proof-of-concept bench session, establishing the superficial target plane at approximately 8-10 mm and the rib surrogates at approximately 18-22 mm depth—critical measurements for trainees to understand.
Construction is straightforward. Four wooden stacking blocks support a scaffold of tongue depressors, which act as rib surrogates. A water-filled examination glove sits beneath them, serving as a simulated pleural safety boundary. The tissue stack is composed of two chicken fillets representing the serratus anterior and latissimus dorsi muscles, with a single layer of cling film creating the fascial plane between them. A fluid-filled thermometer probe cover is placed in this plane to mimic the thoracodorsal artery, a key sonographic landmark for the superficial approach.
Practice Model Helps Doctors Learn Chest Injection
- This is a practice model, not a toy, designed to help doctors learn a specific chest injection safely on a simulated patient.
- It uses everyday items like chicken and wooden sticks to mimic the body’s layers, including a “blood vessel” and a “lung membrane” to avoid puncturing.
- The goal is to build a doctor’s confidence and skill before they perform the procedure on a real patient, potentially leading to better pain management and fewer complications.
From Simulation to Supervised Practice: A Staged Pathway
The model is presented as a “part-task trainer,” meaning it focuses on rehearsing specific components of a procedure rather than the entire clinical encounter. Its primary function is to train for the superficial SAPB, with tasks including in-plane needle visualization, vessel avoidance, and hydrodissection. The model provides immediate visible feedback if an unsafe needle trajectory breaches the water-filled glove, simulating a pleural breach. It does not replicate the complex physiology of a pneumothorax. The authors propose a seven-step pathway, using phantom performance as a gate for progression to directly supervised patient procedures.
This staged approach aligns with established educational principles. A randomized study of novice anaesthesia residents found that just one hour of low-fidelity simulation training improved early block-room performance, with a higher percentage of simulation-trained residents achieving proficiency compared to those trained conventionally. Similarly, SAPB-specific mastery learning has been demonstrated in emergency medicine residents using a procedural checklist. These findings strongly support simulation as preparation for supervised practice but not as a standalone tool for competency assessment.
| Component | Material & Function | Clinical Significance |
|---|---|---|
| Rib Surrogates | Three transverse tongue depressors | Provide a depth reference and firm landmark for needle insertion. |
| Pleural Boundary | Water-filled examination glove | Simulates the pleura, providing immediate feedback on unsafe needle depth. |
| Thoracodorsal Artery | Fluid-filled thermometer probe cover | Mimics the key vascular landmark to avoid accidental puncture. |
| Fascial Plane | Single layer of cling film | Represents the target tissue plane for local anaesthetic deposition. |
Globally Relevant, Locally Implemented
While the model was designed with UK emergency medicine trainees in mind, its principles are transferable globally. The core challenge—balancing cost, efficacy, and safety in medical training—is universal.
The model's focus on the SAPB also relates to post-operative pain management. A study from PubMed on thoracoscopic surgery highlighted the significant benefits of ultrasound-guided SAPB, showing it significantly reduces postoperative pain scores, the need for supplemental analgesics, and agitation, while stabilizing perioperative vital signs.
No validity, reliability, durability, or learner-outcome testing was performed. The model and its proposed pathway are offered as a starting point for structured preclinical preparation. The Royal College of Emergency Medicine (RCEM) framework, which integrates simulation, image acquisition, and workplace evidence for competence judgment, provides a relevant precedent for how such a tool should be used within a formal training curriculum.
Consult Doctor After Procedure Symptoms
Any concerning symptoms after a real procedure warrant immediate medical consultation.
Research Needs Validation for Performance
Looking ahead, the most critical next steps for this research lie in validation. Future research must rigorously evaluate whether training with this phantom leads to improved performance, fewer complications, or a faster pathway to clinical competency in supervised settings.
References
- Cureus.
- PubMed. Ultrasound-guided serratus anterior plane block in patients undergoing thoracoscopic surgery.
- ClinicalTrials.gov.
- Good Cause Extension Request Process and Criteria. U.S. Food and Drug Administration.
