
Starting January 1, 2027, most Medicaid expansion adults ages 19 to 64 must document 80 hours of monthly work, education, or community engagement to keep coverage — unless they qualify for a medical frailty exclusion, which explicitly includes people with disabling mental disorders.
In November 2026, CMS offered states an optional six-month delay in enforcement.
For the roughly one-third of adults with mental health conditions who rely on Medicaid, the exemption process — not the work rule itself — may determine whether treatment continues or stops. KFF’s new analysis, published as states finalize implementation plans due to CMS by December 31, 2026, finds that qualifying for the mental health exclusion is far harder than having a diagnosis, KFF reported.
Exempt from Monthly Requirement
- If you have a mental health condition and are on Medicaid expansion coverage, you may be exempt from the 80-hour monthly requirement — but you may need to ask for that exemption or provide documentation.
- A diagnosis alone may not be enough in some states; some require evidence of how the condition limits daily functioning or records of treatment use.
- If you have no recent treatment records, your condition may not appear in state data, so screening questions or self-attestation in 2027 may be your only route to an exclusion.
CMS Softens the Clock, but the Rule Stands
Under the 2025 federal budget reconciliation law, states must still begin implementing the community engagement requirements on January 1, 2027. But in November 2026, the Centers for Medicare and Medicaid Services announced an optional six-month delay on enforcement, giving states breathing room as their data systems and verification processes come online, according to KFF.

The American Academy of Family Physicians, which has tracked the rule’s impact on practices, warned that administrative barriers could cause people to lose coverage even when they would otherwise remain eligible. In a comment letter, the AAFP urged CMS to delay implementation and to direct states to use existing administrative data to establish medical frailty without extra paperwork.
A Rule Written, Struck Down, and Possibly Appealed
The medical frailty standard has shifted repeatedly over the past year. In June 2026, CMS issued an interim final rule adding a requirement that enrollees show evidence their qualifying condition impairs their ability to meet work requirements. In October 2026, a district court struck down that additional requirement — though CMS may still appeal, and the criteria could change again if the ruling is overturned or new guidance is issued, KFF reported.
The National Coalition on Mental Health and Aging, in guidance for behavioral health providers, emphasized the practical consequence: simply having a qualifying diagnosis such as bipolar disorder or a serious substance use disorder is insufficient under the CMS framework, and blanket exemptions are prohibited.
The coalition also flagged a structural risk: people with serious mental illness who hold jobs only because intensive behavioral health treatment stabilizes them could lose coverage if employment changes, triggering what it calls psychiatric decompensation precisely when continuous coverage matters most.
Exposed Population
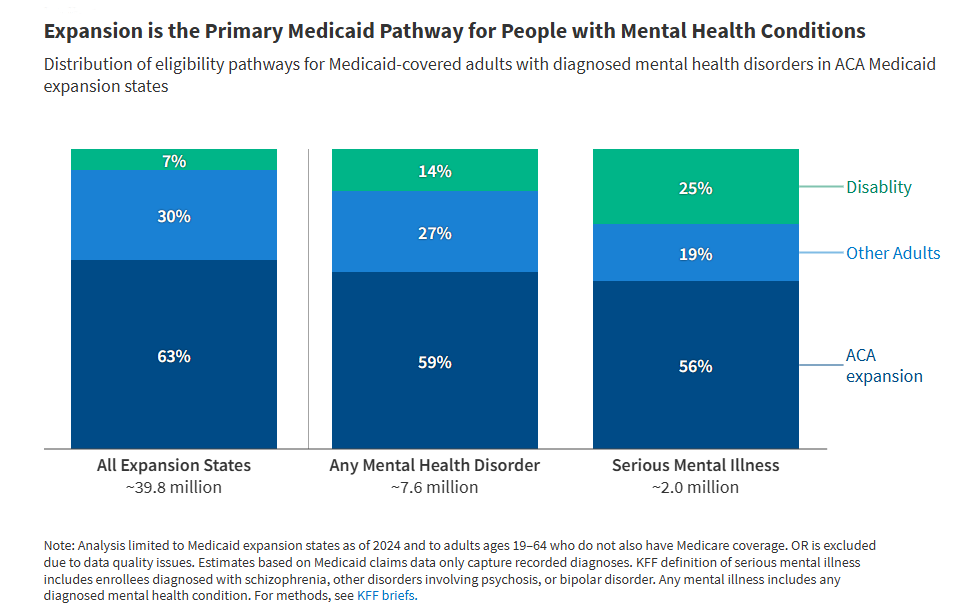
KFF’s data analysis quantifies the exposed population. Among Medicaid-covered adults under 65 with at least one diagnosed mental health disorder in expansion states, 59% qualify through the expansion pathway — as do 56% of those with a diagnosed serious mental illness, defined in the analysis as schizophrenia, bipolar disorder, and other psychotic disorders.
Overall, about 17% of expansion enrollees have at least one diagnosed mental health condition, including about 4% with a diagnosed SMI. KFF notes this likely understates the true burden, since undiagnosed conditions do not appear in claims data.
| Measure (expansion states) | Share |
|---|---|
| Expansion enrollees with ≥1 diagnosed mental health condition | ~17% |
| Expansion enrollees with diagnosed SMI | ~4% |
| Adults with a mental health disorder enrolled via expansion pathway | 59% |
| Adults with SMI enrolled via expansion pathway | 56% |
State Definitions Diverge Sharply
States must build their own lists of which diagnoses qualify as disabling mental disorders, and the variation is substantial. North Carolina’s proposed list includes schizophrenia, bipolar disorder, and major depressive disorder, and would let certain behavioral health services — crisis intervention, partial hospitalization, assertive community treatment — independently establish frailty.
Nevada’s code list includes some of these services as well. Michigan, by contrast, allows dementia and dissociative diagnoses to qualify without extra evidence but requires proof of service use for schizophrenia or bipolar disorder. Indiana requires additional evidence for every mental health condition. A few states treat a recorded suicide attempt as sufficient on its own.
In September, CMS outlined an optional tiered framework, described in agency guidance, under which some conditions qualify on diagnosis alone while others require evidence of severity. North Carolina’s list is open for public comment through its proposed clinical coverage policy.
Why the Exemption May Miss the Sickest Patients
The clinical literature explains the gap. Serious mental illness can impair concentration, memory, and planning — and can involve anosognosia, the inability to recognize one’s own illness, which the National Institute of Mental Health describes in its materials on schizophrenia.
Systematic reviews and meta-analyses cited by KFF document delays of more than five years between symptom onset and diagnosis or treatment of bipolar disorder, whose mood disturbances can disrupt work capacity long before a claim ever reaches a state database.
Claims processing adds delay even for people in treatment. A recent study found the median time from service to payment for Medicaid managed care claims was 26 days, but 10% took longer than 128 days, with wide variation across states and plans. New applicants, meanwhile, have no Medicaid claims history at all.
KFF reports it remains unclear how states will identify people for manual review when claims data are unavailable. In 2027, states may accept self-attestation when data are insufficient — though some have said they will not — and from 2028, self-attestation is limited to once per continuous enrollment period.
Contact Medicaid Promptly
This is a coverage policy, not a treatment, so the clinical caution runs in a different direction. People with serious mental illness who receive a noncompliance notice should contact their state Medicaid agency and their treating clinician promptly — the National Coalition on Mental Health and Aging reports that proof of work or an exemption must generally be established within 30 days of such a notice, after which coverage can end immediately.
Patients whose symptoms include hallucinations, delusions, or acute mood disturbance — as described in NIMH’s public materials — should seek clinical care first and ask a provider or caseworker to help document frailty. Clinicians asked to verify a patient’s status should weigh the confidentiality and stigma concerns that KFF and the AAFP both flag.
States Must Submit Plans
States must submit implementation plans to CMS by December 31, 2026, and fully enact the requirements by the end of 2027, per the AAFP. Whether CMS appeals the October court ruling — and whether more states adopt the six-month delay announced this month — will shape how many people with mental illness keep their coverage in the new year.
References
- KFF — Medical Frailty and Medicaid Work Requirements: Challenges for People with Mental Health Conditions
- American Academy of Family Physicians — Medical frailty and Medicaid work requirements: What to know
- National Coalition on Mental Health and Aging — Medicaid Work Requirements and Behavioral Health Providers
- Centers for Medicare & Medicaid Services — Implementing Medical Frailty guidance
- National Institute of Mental Health — Schizophrenia; Bipolar Disorder publications
