
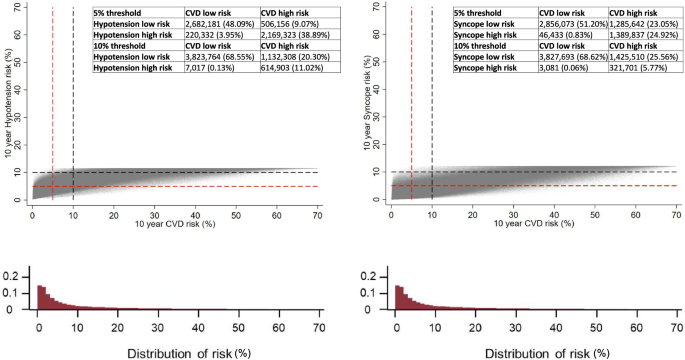
A retrospective observational cohort study published in Nature analysed electronic health records from 5.5 million individuals in England to weigh the cardiovascular benefits of antihypertensive medications against six serious treatment-related harms.
Researchers developed the STRATIFY-CVD prediction model using data from the Clinical Practice Research Datalink to estimate absolute treatment outcomes.
Researchers Model Absolute Treatment Effects and Harms
- Absolute Effect Modelling: Researchers combined patient baseline risk scores with published relative treatment effects to calculate how many adverse events or benefits occur per 1,000 patients treated over a 10-year period.
- Evaluating Harms: Beyond cardiovascular disease reduction, the study measured six specific treatment complications: hypotension, syncope, falls, fractures, acute kidney injury, and hyperkalaemia.
- Model Validation: The new STRATIFY-CVD prediction model was developed in CPRD GOLD and externally validated in CPRD Aurum datasets to ensure population representation across England.
Developing the STRATIFY-CVD Prediction Model
The study protocol received approval from the CPRD Independent Scientific Advisory Committee under protocol number 25_004935 in April 2025. Investigators gathered electronic health records from individuals registered at general practices in England between January 1, 1998, and December 31, 2018. Patients entered the cohort when their systolic blood pressure reached or exceeded 130 mmHg, while individuals with readings of 180 mmHg or higher were excluded because treatment benefits invariably outweigh risks at that threshold.
The primary outcome for the prediction model focused on major cardiovascular disease events, defined as non-fatal myocardial infarction or stroke leading to hospital admission, or any cardiovascular-related death. Covariates incorporated into the multivariable Fine-Gray sub-distribution hazard model drew primarily from the established QRISK2 framework. Missing data for variables such as ethnicity, body mass index, smoking status, and cholesterol ratios were handled using multiple imputation with chained equations.
| Study Parameter | Details & Parameters |
|---|---|
| Observation Window | January 1, 1998, to December 31, 2018 |
| Blood Pressure Threshold | Cohort entry at $ge 130$ mmHg; exclusion at $ge 180$ mmHg |
| Validation Datasets | CPRD GOLD (apparent validation) and CPRD Aurum (external validation) |
| Evaluated Harm Outcomes | Hypotension, syncope, falls, fracture, acute kidney injury, hyperkalaemia |
Weighing Treatment Benefits Against Adverse Events
To evaluate absolute treatment effects, investigators compared baseline cardiovascular risks against the incidence of six distinct harm outcomes. While cardiovascular events are conventionally assessed as a composite endpoint, the six harm outcomes were analysed separately due to their varying severity and impact on patient quality of life. The absolute treatment effect was estimated across the entire cohort as events prevented or caused per 1,000 patients treated for 10 years.
Analyses further stratified these estimates by age, sex, frailty status derived from electronic frailty indices, and pre-existing cardiovascular history. The study protocol ensures all patient data remain fully anonymised, linking primary care entries with Office for National Statistics mortality records and Hospital Episode Statistics inpatient diagnostic data.
Extreme Blood Pressure Readings Demand Urgent Care
Patients exhibiting extreme systolic blood pressure readings at or above 180 mmHg require immediate clinical intervention, as standard risk-prediction models are unnecessary when acute risks dictate urgent treatment.
Future Trajectory of Cardiovascular Risk Modelling
The integration of large-scale electronic health record modelling into primary care decision-making continues to evolve. Questions remain regarding how clinicians will integrate individualised harm-benefit trade-offs into routine consultations for older or frail populations. Investigators intend to refine predictive accuracy across diverse demographic subgroups as longer-term data accumulate.
References
- Clinical Practice Research Datalink (CPRD). Independent Scientific Advisory Committee protocol 25_004935.
- Office for National Statistics (ONS). Linked mortality data for England.
- Hospital Episode Statistics (HES). Inpatient diagnostic data collection.
