
Immune effector cell-associated enterocolitis (IEC-EC), a rare but serious complication of BCMA-directed CAR T-cell therapy, has been characterized in a multicenter analysis covering 53 evaluable cases identified across eight academic institutions between 2019 and 2025, according to the study published in Nature.
All 54 suspected cases of gastrointestinal toxicity after ciltacabtagene autoleucel (cilta-cel) were discussed at a working group multidisciplinary tumor board and underwent central pathology evaluation when diagnostic tissue was available.
Diagnostic confirmation rested on anti-camelid variable heavy-chain (VHH) domain immunohistochemistry, an assay that targets the camelid-derived binding domain of the cilta-cel CAR construct and identifies CAR-positive T cells in tissue sections.
Cases were classified as confirmed IEC-EC at 20% or more VHH-positive lamina propria lymphocytes, probable IEC-EC when clinical or histopathologic features were consistent without VHH confirmation, or negative at fewer than 5% VHH-positive cells. No case had a diagnostic biopsy in the indeterminate 5% to 20% range, although VHH levels in that band were seen in biopsies taken after immunosuppressive therapy had begun.
The assay was available at only five institutions during the study period — Stanford University, MD Anderson Cancer Center, Mayo Clinic, Moffitt Cancer Center and Lombardi Comprehensive Cancer Center — and probable cases most often lacked VHH confirmation because the assay was unavailable at the treating institution or diagnostic tissue was missing.
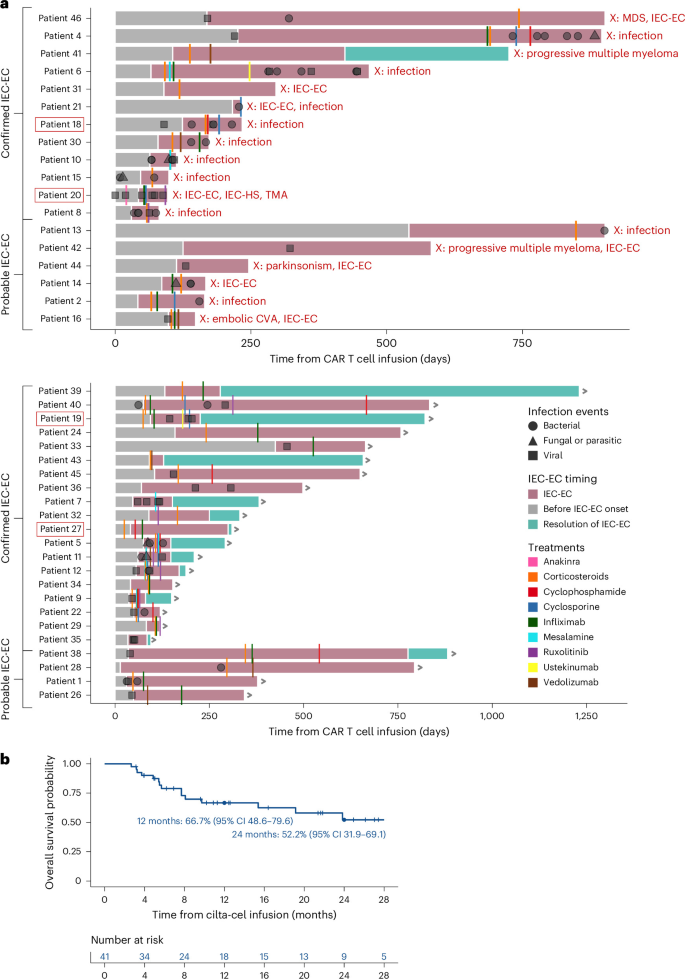
Patients had received a median of four previous lines of therapy; 36% carried high-risk cytogenetics, defined as del(17p), t(4;14) or t(14;16), and 15% had extramedullary disease. Bridging therapy preceded infusion in 38 of 41 patients with IEC-EC, and among 32 evaluable patients, 6 achieved a partial response or better.
The workup also cleared a substantial share of suspected cases: 12 of the 53 (23%) were negative for IEC-EC. Ten underwent endoscopic evaluation with fewer than 5% positive lymphocytes, and alternative causes were identified in four — infectious gastroenteritis in two, bile acid malabsorption in one and medication toxicity in one — while six had self-limited symptoms that resolved without immunosuppression.
One additional patient, treated on the CARTITUDE-1 trial (NCT03548207) in 2019, was adjudicated non-evaluable and excluded after a negative day-1,317 biopsy proved discordant with autopsy-confirmed colitis.
That patient developed diarrhea on day 778 that was clinically consistent with IEC-EC, and the tumor board excluded the case both because it fell outside the 2022 to September 2025 real-world window and because the sole VHH-stained biopsy, obtained without confirmed systematic random duodenal and ileal sampling, left it neither confirmed nor confidently negative.
A companion case series indexed on Europe PMC adds clinical detail on the syndrome’s course. In that series, 19 patients at six U.S. academic centers were treated with commercial cilta-cel from April 2022 to December 2024, an estimated incidence of 4.3%, with a median follow-up of 473 days and a median age at infusion of 68 years. Median diarrhea onset came 81 days after infusion. Any-grade and grade 3-or-higher cytokine release syndrome rates were 74% and 0%, and the corresponding ICANS rates were 26% and 11%.
Diarrhea and colitis were graded with Common Terminology Criteria for Adverse Events (CTCAE) v5.0, while cytokine release syndrome and immune effector cell–associated neurotoxicity syndrome were graded with American Society for Transplantation and Cellular Therapy criteria. The median peak absolute lymphocyte count in the series was 2.2 × 10³/µl (range, 0.6–157.0).
Delayed neurotoxicity preceded diarrhea in five patients — four cranial nerve palsies and one parkinsonism — and seven patients had a preceding infection within 45 days, including four with C. difficile that showed microbiologic clearance and atypical upper-GI inflammation, ruling out ongoing C. difficile colitis.
Stanford University, a private research university in Stanford, California, was founded in 1885 by Leland Stanford, then a United States senator representing California, and his wife, Jane, and admitted its first students in 1891 as a coeducational, non-denominational institution. Its School of Medicine was established in 1908, when the university acquired Cooper Medical College in San Francisco, and moved to the Stanford campus in 1959.
The university is organized around seven schools on an 8,180-acre campus, one of the largest in the nation, and is classified among “R1: Doctoral Universities – Very high research activity”. In 1951 it established Stanford Research Park in Palo Alto, the world’s first university research park, a development that gave rise to what is today known as Silicon Valley.
Despite a call for cases that was open to all BCMA-directed CAR T-cell products, only cases following cilta-cel were submitted — a pattern the investigators attribute to current clinical-use patterns.
