
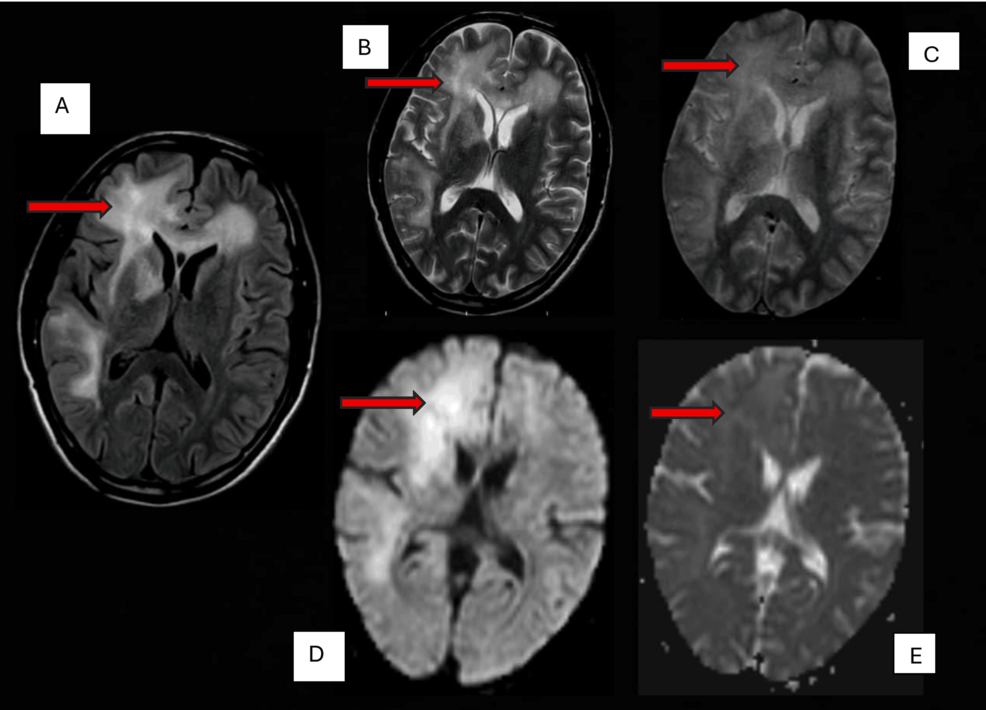
A newly diagnosed HIV patient with a CD4 count above 200 cells per microlitre developed inflammatory progressive multifocal leukoencephalopathy without immune reconstitution, demonstrating an atypical non-IRIS phenotype.
Progressive multifocal leukoencephalopathy (PML) is a severe neurological disorder caused by the John Cunningham virus, a polyomavirus that affects approximately 4% of individuals with human immunodeficiency virus type 1, Cureus reported. The condition typically emerges during advanced infection when CD4 counts drop below 100 cells per microlitre.
A recent case profile published in Cureus details an unusual presentation in a male patient in his 40s who experienced left-sided limb weakness, a right hemicranial headache, and a focal seizure.
The patient was diagnosed with a retroviral disease during hospital admission but had not yet started antiretroviral therapy. Routine blood tests showed positive HIV serology alongside a CD4 count of 212 cells per microlitre, placing him above the threshold where PML normally manifests. Brain magnetic resonance imaging revealed altered signal intensity across the bilateral frontal, right basofrontal, right temporoparietal, and right capsuloganglionic regions.
Diffusion-weighted imaging showed T2 shine-through with patchy regions of free diffusion, while post-contrast scans demonstrated subtle nodular enhancement along the lesion margins. Cerebrospinal fluid analysis confirmed the presence of the JC virus via polymerase chain reaction testing, establishing a definitive diagnosis of non-immune reconstitution inflammatory syndrome PML. Clinicians initiated antiretroviral therapy using tenofovir, emtricitabine, and efavirenz, alongside anti-seizure medications including levetiracetam and clobazam.
Classical PML arises during profound immunosuppression, marked by demyelination driven by unchecked viral replication with minimal tissue inflammation. In contrast, PML-associated immune reconstitution inflammatory syndrome typically occurs after patients start antiretroviral therapy, triggering restored immunity that attacks previously infected central nervous system tissue. The case described in Cureus highlights a distinct clinical entity where inflammatory radiological features emerged in an antiretroviral-naïve patient, bypassing the classical immune reconstitution window.
Magnetic resonance imaging findings included gyriform T1 hyperintensity, corresponding to hyperintense cortical signals in the deeper cortex adjacent to white matter lesions. This phenomenon results from direct involvement of deeper cortical layers, leading to neuronal loss termed JC virus-associated focal leukocortical encephalitis.
While such imaging characteristics resemble laminar necrosis seen in ischemic strokes or status epilepticus, their presence alongside white matter lesions points directly to an aggressive, localized viral-driven inflammatory process.
Over more than seven years of regular follow-up evaluations, the patient maintained viral suppression and restored his CD4 counts to the normal reference range. He did not develop permanent focal neurological deficits and successfully returned to employment three months after discharge. Breakthrough seizures required short-term hospital admissions lasting one to two days, which physicians managed effectively through adjustments to his anti-seizure medications.
Follow-up neuroimaging confirmed significant resolution of the active white matter lesions, accompanied by regional frontotemporal brain atrophy and ex vacuo ventricular enlargement. Antiretroviral therapy acts indirectly by driving up CD4 cell counts, extending survival from a historical mean of three to four months to years of neurological stability.
The case shows that inflammatory neuroimaging features in antiretroviral-naïve patients require careful evaluation to distinguish non-IRIS inflammatory phenotypes from standard reconstitution syndromes.
| Clinical Parameter | Patient Findings | Standard PML Presentation |
|---|---|---|
| Baseline CD4 Count | 212 cells/µL | Typically < 100 cells/µL |
| Antiretroviral Status | ART-naïve at presentation | Varies (often post-ART for IRIS) |
| JC Virus Detection | Confirmed via CSF PCR | Confirmed via CSF PCR |
| Inflammatory Imaging | Subtle nodular enhancement & HCS | Usually minimal inflammation |
The patient demonstrated a favourable long-term outcome, with subsequent clinical and radiological evaluations revealing only well-controlled scar epilepsy, Cureus reported.
