
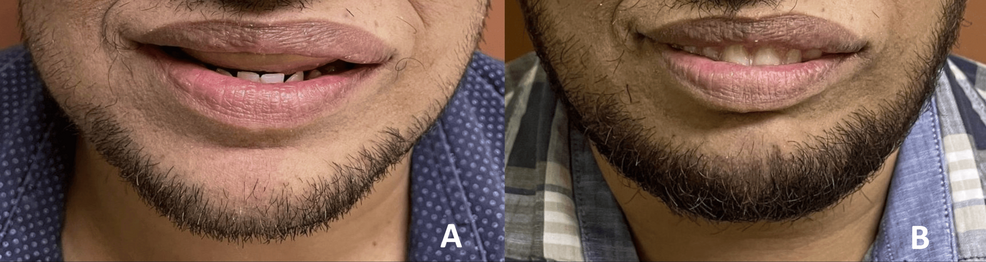
A 31-year-old male osteosarcoma survivor received non-surgical prosthetic rehabilitation using a thermoplastic pressure-molded sheet after enduring nine years without teeth due to a bulky microvascular fibula flap, Cureus reported.
Maxillary osteosarcomas account for 6 to 8% of all osteosarcomas. Radical resective surgery followed by microvascular flap reconstruction remains the standard treatment approach. However, bulky flaps often leave patients with severe anatomical mismatches, restricted inter-arch space, and devastating impacts on facial esthetics, mastication, and psychosocial well-being.
The patient underwent a segmental maxillectomy, Brown Class IIc, alongside free fibular flap reconstruction. Subsequent treatments included chemotherapy and image-guided radiation therapy at a cumulative dose of 54 Gy. The psychological trauma of the ordeal left him refusing secondary debulking surgery or conventional prosthetics for nearly a decade.
Slim Thermoplastic Appliance Restores Appearance Without Surgery
- What happened: A cancer survivor lived nine years without replacing his upper teeth because reconstructive surgery left too little room for a normal denture, and he feared further operations.
- How it was solved: Clinicians bypassed surgery by fabricating a slim, transparent thermoplastic appliance that holds artificial teeth in front of the bulky tissue graft.
- Why it matters: This non-invasive method restores appearance and social confidence for patients who refuse or cannot undergo secondary revision surgeries.
Overcoming Restricted Inter-Arch Space Without Surgery
Prosthodontic rehabilitation of maxillary defects presents profound anatomical challenges. Unplanned microvascular reconstruction frequently results in unfavorable soft-tissue bulk, insufficient vestibular depth, and negligible inter-arch space. While fixed dental implants offer high success rates elsewhere, prior radiotherapy lowers implant survival in free fibula flaps to between 73.8% and 84.6%, Cureus reported.
Secondary surgical procedures like flap debulking or vestibuloplasty can clear space for traditional restorations. Yet, physical and psychological burdens frequently deter patients from pursuing them. Clinical examination of the patient revealed an incompetent upper lip, a convex profile, and a bulky flap measuring 1.9 cm vertically, 4.5 cm mesio-distally, and 3.5 cm antero-posteriorly. Lower anterior teeth impinged directly upon the flap, causing localized erythema from mechanical trauma.
Cone beam computed tomography scans confirmed satisfactory bone healing, though healing in the maxillary left lateral incisor and canine region remained questionable. Because the patient steadfastly declined further surgical intervention, clinicians devised a conservative, non-invasive rehabilitation strategy utilizing a thermoplastic sheet-supported partial denture.
Fabrication of the Thermoplastic Prosthesis
Alginate impressions were poured in type III dental gypsum, and maxillomandibular relationships were mounted on an articulator. Acrylic teeth were trimmed on their lingual and ridge lap surfaces down to a thickness of 1 to 1.5 mm while preserving their visible labial contours for esthetics.
The modified teeth were positioned labial to the flap as facings on the cast, secured temporarily with cyanoacrylate adhesive. A thin layer of pink auto-polymerizing resin was contoured around the artificial teeth to mimic natural gingiva. After finishing and polishing, a transparent 0.75 mm polyethylene terephthalate-glycol thermoplastic sheet was pressure-molded over the assembly using a dedicated pressure molding machine.
This pressure-molding technique allowed the thermoplastic material to adapt closely to the resin-teeth complex, providing secure mechanical retention. The finished appliance covered the remaining teeth and palatal region to maximize stability without impinging excessively on the restricted oral volume.
| Parameter | Clinical Finding |
|---|---|
| Patient Age and Sex | 31-year-old male |
| Initial Pathology | Well-differentiated osteosarcoma of the maxilla |
| Reconstructive Method | Microvascular free fibula flap |
| Radiation Dose | 54 Gy image-guided radiation therapy |
| Prosthetic Technique | 0.75 mm PET-G thermoplastic pressure-molded denture |
Patient Adaptation and Follow-Up Evaluations
The prosthesis was seated intraorally and checked for proper fit, comfort, insertion ease, and occlusal stability. Salivary flow remained normal, and the patient received standard oral hygiene instructions emphasizing meticulous cleaning while removing the appliance during meals and sleep.
Regular clinical evaluations at one week, 15 days, one month, and three months demonstrated satisfactory adaptation. Clinical observations and photographic comparisons confirmed marked improvements in facial esthetics and lateral profile balance. The patient expressed clear satisfaction with the results, and examinations revealed no mechanical delamination, loosening, or separation of the acrylic teeth from the thermoplastic carrier sheet.
Avoid Thermoplastic Appliances If Malignancy or Periodontal Disease Is Present
Patients with active malignancy, uncontrolled periodontal disease, or severe manual dexterity issues preventing appliance removal should avoid thermoplastic removable appliances. Individuals must consult a qualified prosthodontist or maxillofacial surgeon immediately if they experience persistent mucosal ulceration, localized pain, tissue inflammation, or signs of mechanical impingement beneath the prosthesis.
Next Steps in Non-Invasive Rehabilitation
The successful six-month evaluation highlights a viable pathway for managing post-surgical oncology patients who reject secondary surgeries. Long-term follow-up remains necessary to monitor tissue health beneath the thermoplastic coverage and ensure material durability.
References
- Cureus: Pressure-Molded Thermoplastic Prosthesis for a Patient With Reduced Inter-arch Space After Fibula Flap Reconstruction of the Maxilla: A Case Report.
- PubMed: Outcomes of dental implants in irradiated versus non-irradiated free fibula flaps.
