
A case report highlights the severe systemic complications following organophosphorus (OP) poisoning.
Organophosphorus (OP) poisoning is a significant public health concern, particularly in regions like India, where intentional self-poisoning is a documented occurrence. This case shows why doctors must monitor renal function, muscle markers, and electrolyte balance even after the initial acute poisoning has stabilized.
In Plain English: The Clinical Takeaway
- OP Poisoning is Systemic: The toxic effects of OP poisoning extend far beyond the nervous system, potentially affecting the kidneys and muscles, leading to Acute Kidney Injury (AKI).
- Intermediate Syndrome (IMS) Risk: IMS, a neurological condition occurring after the initial crisis, involves progressive proximal muscle weakness requiring specialized management.
- Rhabdomyolysis is a Major Threat: Severe muscle breakdown (rhabdomyolysis) releases toxins into the bloodstream, which can cause severe kidney failure (AKI) and dangerous electrolyte imbalances like hyperkalemia.
The Pathophysiology of Organophosphate Toxicity and Acute Kidney Injury
OP compounds exert their toxicity by irreversibly inhibiting the enzyme acetylcholinesterase (AChE). This enzyme normally breaks down the neurotransmitter acetylcholine (ACh) in the synaptic cleft. When AChE is inhibited, ACh accumulates excessively on muscarinic and nicotinic receptors, leading to the characteristic cholinergic crisis (e.g., miosis, excessive secretions, and muscle fasciculations).
The development of Acute Kidney Injury (AKI) in these cases is multifactorial. The primary mechanisms hypothesized include direct nephrotoxicity from the pesticide itself, hemodynamic instability resulting from shock or vasopressor use, and the secondary injury caused by rhabdomyolysis. Rhabdomyolysis, severe muscle breakdown, releases creatine kinase (CPK) and myoglobin into the circulation, which can overwhelm the kidney’s ability to filter waste and maintain electrolyte homeostasis.
The case detailed a patient with a CPK level of 38,710 U/L. This extremely high level of CPK confirms severe rhabdomyolysis. The subsequent rise in serum creatinine defined his AKI, requiring emergency hemodialysis to manage life-threatening hyperkalemia.
How Intermediate Syndrome Caused the Patient's Muscle Weakness
Intermediate Syndrome (IMS) is a distinct neurological complication reported to occur after the initial acute cholinergic crisis subsides. It is predominantly characterized by weakness in proximal muscles and neck flexors. This patient experienced profound proximal muscle weakness (less than 2/5) which was clinically diagnosed as IMS. This condition is proposed to stem from an abnormality in the neuromuscular junction, possibly involving postsynaptic transmission, though the precise pathophysiology remains unclear.
While the patient initially received standard treatments like atropine and pralidoxime (an oxime used to reactivate AChE), the progression of IMS and the associated muscle injury necessitated a complex management plan, including mechanical ventilation and specialized supportive care during the subsequent rise in muscle toxins.
OP poisoning can manifest with either an acute cholinergic crisis or delayed toxicity. The combination of these acute and subacute events significantly complicates the clinical picture, often resulting in a poor prognosis if critical supportive care is not provided.
The Intersection of Infection, Rhabdomyolysis, and Organ Failure
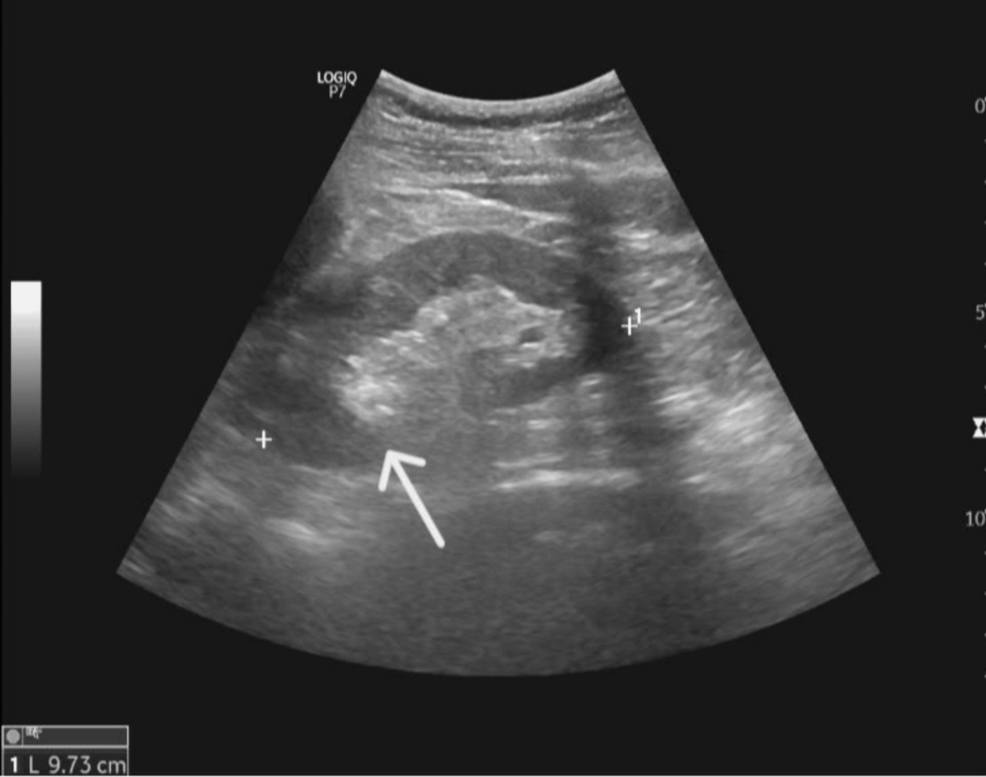
The patient’s renal deterioration was further complicated by systemic infections. Investigations revealed evidence of left pyelonephritis, which required the use of polymyxin B. This infectious process, combined with the metabolic stress of rhabdomyolysis and the hemodynamic changes from earlier resuscitation, created a “perfect storm” for acute kidney injury.
The progression of AKI in this case illustrates the concept of multiple organ distress syndrome (MODS). The kidney injury was not solely due to the initial pesticide exposure; it was a culmination of toxin-induced nephrotoxicity, hemodynamic shock, and severe renal insult from a nosocomial infection. In the initial presentation, the patient was intubated with a Glasgow Coma Scale (GCS) score of 7/15, indicating a depressed level of consciousness that added layers of diagnostic difficulty.
| Organ Failure Factor | Primary Mechanism | Clinical Manifestation | Key Treatment |
|---|---|---|---|
| Rhabdomyolysis | Massive muscle breakdown (CPK 38,710 U/L) | Refractory hyperkalemia | Hemodialysis, Potassium-binding resins |
| Renal Failure (AKI) | Multi-factorial (Shock, Toxin, Infection) | Creatinine rising to 7.2 mg/dL | Renal Replacement Therapy (Hemodialysis) |
| Neurological Impairment | Post-cholinergic/Neuromuscular Junction | Proximal muscle weakness (IMS) | Atropine, Pralidoxime, Supportive Care |
Epidemiological Risk and Global Healthcare Response to OP Poisoning
In Pakistan, where OP poisoning is frequently used for intentional self-poisoning, the exact number of cases is difficult to calculate because the country lacks strong poison surveillance systems. Globally, an estimated 3 million people are exposed to organophosphates or carbamates yearly, with up to 10% (300,000) fatalities.
The necessity for advanced care, including mechanical ventilation and dialysis, highlights the strain on regional healthcare systems. This case shows why physicians must watch for severe, non-respiratory systemic complications, even when classic kidney symptoms are absent at first.
Contraindications & When to Consult a Doctor
This is not a condition for home management. Patients must be monitored for the early signs of respiratory distress, excessive secretions, and muscle weakness. Pharmacological treatments, such as specific oximes (like pralidoxime), have strict protocols regarding timing; they are most effective when administered promptly following exposure.
Individuals with pre-existing conditions, particularly hypertension or diabetes, are at significantly higher risk for severe outcomes, including AKI, following OP exposure. Management of such co-morbidities requires highly specialized intensive care unit (ICU) protocols.
