
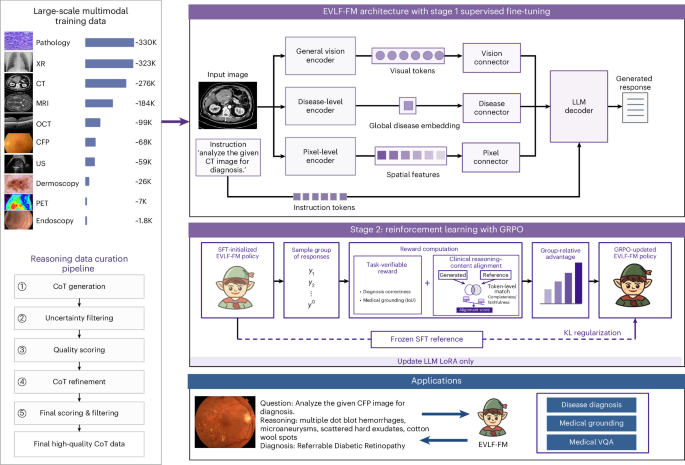
EVLF-FM is an advanced, multimodal vision-language foundation model designed for medical imaging that combines multi-disease classification with pixel-level explainability. Built with a dual-encoder architecture and reinforcement learning, the model achieves high diagnostic accuracy across dermatology, radiology, pathology, and ophthalmology while providing explicit visual grounding for clinical decision support.
As health systems grapple with the opacity of traditional artificial intelligence tools, researchers have rolled out clinical validation data comparing specialized deep learning frameworks against generalist models. Published findings from Bai et al. indicate that EVLF-FM tackles the long-standing “black-box” dilemma in medical diagnostics by integrating high-level disease classification with dense spatial tracking. Rather than merely outputting a disease probability, the model maps its diagnostic reasoning directly onto anatomical regions across diverse imaging modalities.
Decoding Diagnostic Architecture and Dual-Encoder Mechanics
EVLF-FM relies on a dual-encoder framework designed to process clinical images at both global and local levels. The disease-level encoder, formulated as $e = f_{text{disease}}(I)$, extracts overarching macroscopic patterns essential for disease categorization. Simultaneously, a pixel-level encoder $p in mathbb{R}^{H times W times C} = f_{text{pixel}}(I)$ captures dense spatial features, which are then projected into the language-model space via dedicated multimodal connectors.
This dual pathway prevents the loss of granular information that typically plagues traditional convolutional neural networks. The system consistently outperformed generalist vision-language models in accuracy and F1 scores across multiple diagnostic benchmarks.
| Dataset Modality | EVLF-FM Accuracy | EVLF-FM F1 Score | Key Comparator Performance |
|---|---|---|---|
| BCN20000 (Dermatology) | 0.949 | — | Highest among evaluated models |
| BUSI (Ultrasound) | 0.932 | 0.926 | Outperformed generalist VLMs |
| OAEFD-OCT (Ophthalmology) | 0.990 | 0.977 | State-of-the-art benchmark |
| MedMNIST (Multi-domain) | 0.851 | 0.808 | Highest mean accuracy overall |
Bridging Visual Grounding and Zero-Shot Clinical Adaptability
Beyond static image classification, the model demonstrates robust performance in visual question answering (VQA) and medical visual grounding. When evaluated on datasets such as VQA-RAD and SLAKE, EVLF-FM maintained closed-accuracy rates near 90% and open recall exceeding 80%. This indicates a capacity to generate contextually appropriate free-text clinical reasoning rather than relying solely on closed multiple-choice parameters.
In visual grounding tasks measured via intersection over union (IoU) thresholds, EVLF-FM averaged an [email protected] of 0.842 and a mean IoU of 0.741 across nine distinct imaging modalities, outperforming baseline models like InternVL 8B. Furthermore, zero-shot and few-shot external testing across un-seen datasets confirmed that incorporating in-context examples enhances diagnostic output.
In Plain English: The Clinical Takeaway
- Transparent AI Mapping: The model does not just name a condition; it highlights the exact pixels on an X-ray or pathology slide that led to its conclusion.
- Cross-Specialty Versatility: It performs reliably across diverse formats, including skin lesions, eye scans, and computed tomography, rather than being restricted to a single organ system.
Contraindications & When to Consult a Doctor
Foundation models like EVLF-FM serve strictly as decision-support tools and are not cleared to replace independent physician judgment, histopathological confirmation, or direct physical examinations. Clinicians should exercise caution when applying automated diagnostics to multi-label datasets with severe class imbalances, such as complex chest radiography, where overlapping pathologies can obscure primary findings. Patients experiencing acute cardiopulmonary symptoms, sudden vision loss, or dermatological changes requiring immediate triage must seek prompt evaluation by a licensed healthcare professional rather than relying on algorithmic output.

References
- Bai, et al. (2025). Clinical Multimodal Vision Language Foundation Model with Fine-Grain Explainability. arXiv preprint.
- Cai, et al. (2026). Early Vision-Language Fusion for Generative Dataset Distillation.
- Vixège, et al. (2021). Full-Volume Intraventricular Flow Reconstruction from Triplane Color Doppler. arXiv:1803.02825.
Disclaimer: This article is for informational purposes only and does not constitute medical advice, diagnosis, or treatment recommendations.
