
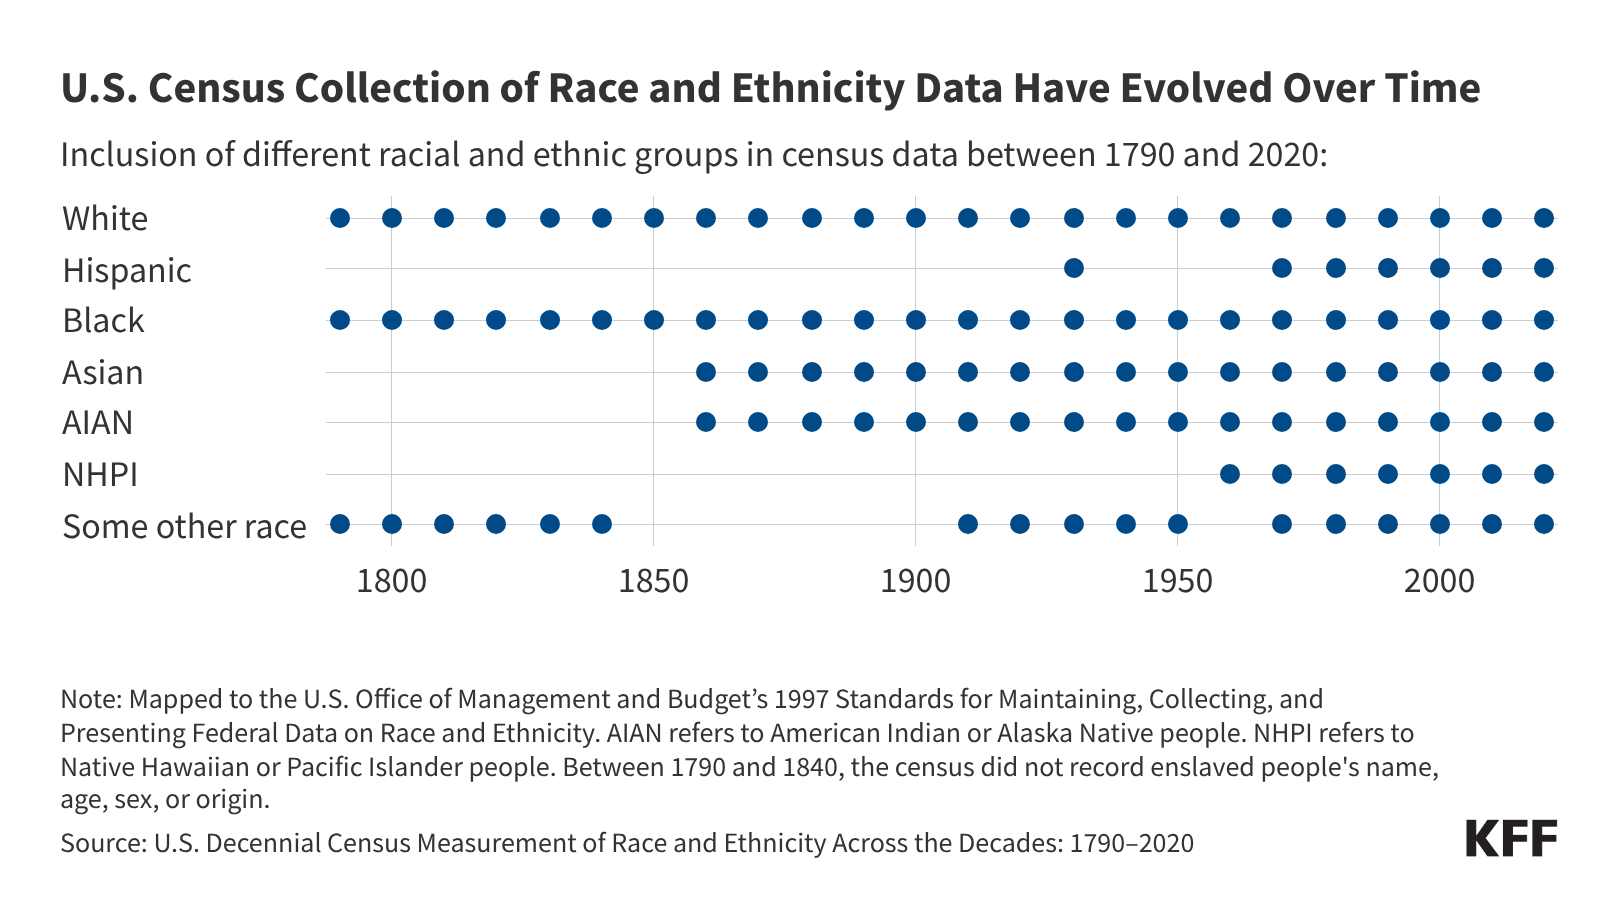
Proposed changes to the U.S. Census Bureau regulations published on September 10, 2026, would prohibit questions on race, ethnicity, and sexual orientation while excluding millions of noncitizen immigrants from apportionment counts. This shift threatens vital data collection used to address healthcare disparities and distribute federal health funding.
In Plain English: The Clinical Takeaway
- Loss of Clinical Metrics: Removing race and ethnicity questions eliminates block-level data necessary for tracking diseases and healthcare access gaps among diverse populations.
- Funding Vulnerabilities: Excluding millions of noncitizens from the official apportionment count could reduce federal funding for essential safety-net programs like Medicaid and the Children’s Health Insurance Program (CHIP).
- Population Accuracy: Utilizing tax records to define “usual residence” risks undercounting marginalized groups, creating a distorted epidemiological picture of who actually resides in the United States.
The Mechanics of Demographic Data and Public Health Surveillance
The decennial census, constitutionally mandated since 1790, serves as the foundational data source for epidemiological research across the United States. Drishti Pillai and Samantha Artiga note that the census is the only complete source of block-level data on race, ethnicity, and core sociodemographic characteristics. Researchers and public health officials rely on these granular data points to construct nationally representative survey samples, weigh clinical data, and investigate disparities in workforce health, chronic disease prevalence, and housing stability.
Under the proposed rule issued by the Census Bureau on September 10, 2026, two unprecedented changes would alter these processes. First, the regulations would prohibit questions on race and ethnicity, alongside sexual orientation. Second, the rule narrows the definition of “usual residence” to exclude millions of noncitizen immigrants—including undocumented individuals and lawfully present immigrants without lawful permanent resident status, such as a green card—from the official apportionment count used to divide the 435 seats in the U.S. House of Representatives.
The Census Bureau also proposes utilizing tax records to determine "usual residence." This methodological shift threatens to systematically exclude individuals who do not file formal tax returns from the population count. Public comments on the proposed rule remain open until October 13, 2026, after which the Census Bureau must review and respond before establishing a final rule. While any final implementation will likely face intense legal challenges, and potential shifts in presidential administration could alter its trajectory prior to the 2030 decennial census, the immediate policy friction highlights deep vulnerabilities in our national health data architecture.
Implications for Federal Health Funding and Health Disparities Research
Data granularity is essential for allocating federal resources effectively. When states and localities with large immigrant populations experience population undercounts in apportionment figures, the downstream effects ripple directly into healthcare financing. Federal funding formulas for major health programs, including Medicaid and CHIP, rely heavily on accurate census enumerations to distribute hundreds of billions of dollars annually.
Eliminating race and ethnicity tracking also obstructs longitudinal epidemiological studies.
| Metric / Variable | Historical Standard (1790–2020) | Proposed Rule (September 2026) |
|---|---|---|
| Race and Ethnicity Data | Collected via decennial census questionnaires | Prohibited from inclusion |
| Apportionment Inclusion | All persons living in the U.S., regardless of status | Excludes noncitizens without LPR status |
| Residency Determination | Physical enumeration and self-response | Potential reliance on tax records |
Contraindications & When to Consult a Doctor
Conclusion
The proposed modifications to demographic data collection represent a fundamental departure from centuries of census precedent. As the public comment period proceeds toward the October 13, 2026 deadline, clinicians, researchers, and policymakers must closely evaluate how the erosion of granular demographic data will influence future efforts to monitor and resolve healthcare disparities across the nation.
