Cardiovascular disease remains a major contributor to disability in women, yet clinical guidelines and diagnostic frameworks are still largely derived from studies where male-pattern disease phenotypes predominated. Addressing this systemic disparity requires redesigning cardiovascular medicine around fundamental sex differences in physiology, pathophysiology, and clinical presentation.
In Plain English: The Clinical Takeaway
- Beyond Typical Symptoms: Female patients experiencing acute coronary syndromes often present without classic crushing chest pain, frequently reporting atypical symptoms like severe fatigue or shortness of breath.
- Biological Variables: Sex-specific vascular mechanics, plaque erosion rates, and hormonal transitions throughout the lifespan directly alter cardiovascular risk profiles.
- Evidence Gaps: Historically low female enrollment in major clinical trials has left significant gaps in sex-stratified dosing and treatment guidelines.
The Historical Evidence Gap in Cardiovascular Trials
For decades, foundational cardiovascular clinical trials relied heavily on male cohorts, assuming that pathophysiology observed in men applied uniformly to women. Analyses of clinical trials supporting FDA approval of cardiovascular drugs highlight persistent underrepresentation of female participants (Scott et al., 2018; Spiering et al., 2024). This historical imbalance created an evidence ecosystem that inadequately addresses female-specific biology (Regitz-Zagrosek & Gebhard, 2023). Without comprehensive, sex-disaggregated data, clinicians have had to extrapolate treatment efficacies and safety profiles from data that poorly reflect female physiology.
Recent reviews of trial persistence, such as the LoDoCo2 trial analysis examining permanent discontinuation rates of trial medications in chronic coronary artery disease, underscore the necessity of tracking sex-specific adverse events and tolerability (van der Bijl et al., 2025). Systematic evaluations of cardiovascular trials published between 2017 and 2023 confirm that while incremental progress occurs, systemic structural hurdles continue to limit equitable enrollment (Rivera et al., 2025; Cho et al., 2021).
Differentiating Female-Predominant Conditions and Pathophysiology
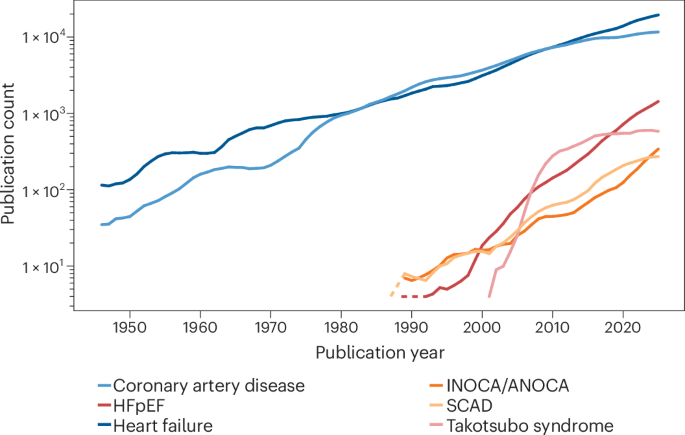
Cardiovascular disease manifestation diverges significantly across the life course due to distinct physiological mechanisms (Patwardhan et al., 2024; Vogel et al., 2021). Conditions such as spontaneous coronary artery dissection (SCAD), Takotsubo syndrome, and coronary vasomotor disorders disproportionately affect women. Historically under-recognized as distinct clinical entities, these conditions lack extensive mechanistic insight and large-scale, evidence-based therapeutic strategies (Saw et al., 2019; Singh et al., 2022).
Unlike obstructive coronary artery disease driven by classic lipid-core plaque rupture, sudden coronary events in women frequently involve coronary plaque erosion without rupture (Farb et al., 1996). The menopausal transition introduces distinct vascular and metabolic alterations that accelerate cardiovascular risk, demanding timed, early preventive interventions tailored to these biological shifts (El Khoudary et al., 2020).
Diagnostic Precision: Redefining Biomarkers and Clinical Thresholds
Diagnostic protocols must account for physiological variances in biomarker baselines. High-sensitivity cardiac troponin assays demonstrate clear sex-specific 99th-percentile upper reference limits. Utilizing universal thresholds often leads to the under-diagnosis of myocardial infarction in female patients, whose baseline circulating troponin concentrations typically run lower than those of males (Lee et al., 2019; Kimenai et al., 2018; Cao et al., 2024; Liu et al., 2022).
| Clinical Feature | Male-Pattern Dominant Evidence | Female-Predominant Considerations |
|---|---|---|
| Primary Pathophysiology | Obstructive plaque rupture with lipid core | Coronary plaque erosion, microvascular dysfunction, and vasospasm |
| Atypical Presentations | Less common; classical substernal chest pressure predominates | Frequent absence of chest pain; presentations include dyspnea, fatigue, and nausea (van Oosterhout et al., 2020) |
| Diagnostic Thresholds | Standardized high-sensitivity troponin cutoffs | Sex-specific high-sensitivity troponin thresholds required for accurate AMI detection |
| Unique Etiologies | Atherosclerotic cardiovascular disease standard | Disproportionate incidence of spontaneous coronary artery dissection (SCAD) and Takotsubo syndrome |
Translational Research and Regulatory Roadmaps
Redesigning cardiovascular medicine requires embedding sex as a biological variable across preclinical and clinical investigation. Regulatory bodies, including the European Society of Cardiology (ESC) through its updated guidelines for chronic coronary syndromes, acute coronary syndromes, and heart failure management, increasingly emphasize sex-specific risk stratification (Vrints et al., 2024; McDonagh et al., 2021; Byrne et al., 2023; McDonagh et al., 2023). Capitalizing on advanced imaging, proteomics, and multi-omics technologies can accelerate the discovery of sex-biased pathophysiological mechanisms, ultimately refining both diagnostic accuracy and therapeutic precision.
Contraindications & When to Consult a Doctor
Patients undergoing cardiovascular evaluation or adjusting chronic regimens must be aware of specific clinical caveats:
- Pharmacological Contraindications: Emerging sex-stratified evaluations of therapeutics like low-dose colchicine emphasize that dosage adjustments and contraindications must be meticulously reviewed against renal function and concurrent medications (Nidorf et al., 2020; Khan et al., 2025).
References
- Patwardhan, V. et al. (2024). Differences across the lifespan between females and males in the top 20 causes of disease burden globally: a systematic analysis of the Global Burden of Disease Study 2021. The Lancet Public Health, 9(5), e282–e294.
- Regitz-Zagrosek, V., & Gebhard, C. (2023). Gender medicine: effects of sex and gender on cardiovascular disease manifestation and outcomes. Nature Reviews Cardiology, 20, 236–247.
- Scott, P. E. et al. (2018). Participation of women in clinical trials supporting FDA approval of cardiovascular drugs. Journal of the American College of Cardiology, 71(18), 1960–1969.
- Vogel, B. et al. (2021). The Lancet Women and Cardiovascular Disease Commission: reducing the global burden by 2030. The Lancet, 397(10292), 2385–2438.
- Lee, K. K. et al. (2019). Sex-specific thresholds of high-sensitivity troponin in patients with suspected acute coronary syndrome. Journal of the American College of Cardiology, 74(16), 2032–2043.
Disclaimer: This article is for informational and educational purposes only and does not substitute for professional medical advice, diagnosis, or treatment. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a medical condition.