
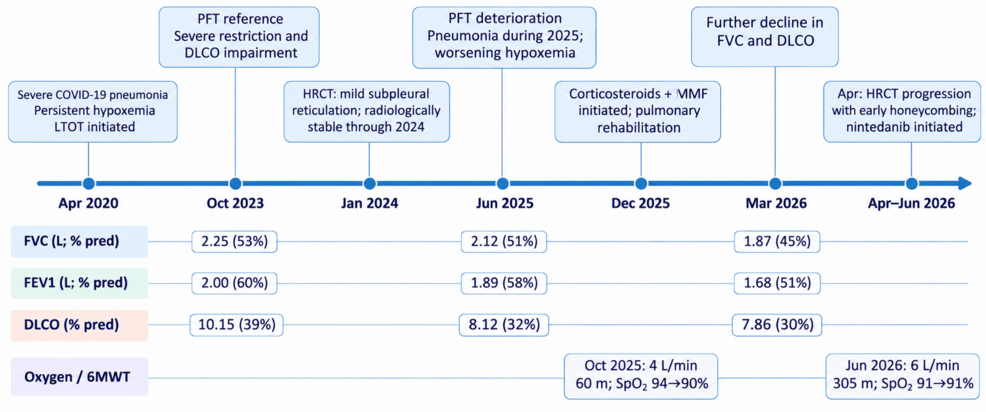
Two men developed progressive pulmonary fibrosis years after surviving severe COVID-19 pneumonia, challenging assumptions that post-viral lung damage stabilizes over time, Cureus reported this week.
The cases, published in Cureus, describe a 57-year-old man infected in April 2020 and a 64-year-old man infected in December 2021. Both met criteria for progressive pulmonary fibrosis (PPF) — defined by worsening symptoms, lung-function decline, and radiological progression — despite initial stability or improvement.
The first patient deteriorated after a subsequent pneumonia in 2025; the second developed new honeycombing in 2025 after years of radiological quiescence. Both were started on nintedanib and referred for lung-transplant evaluation.
“PPF may develop several years after severe COVID-19 pneumonia, even with initial radiological improvement or prolonged stability,” the authors wrote. They recommend continued evaluation with serial pulmonary function tests and high-resolution computed tomography (HRCT), plus early transplant referral for patients who progress despite medical therapy.
Why delayed progression rewrites follow-up protocols
Current guidelines often taper imaging after one to two years of stability. These cases show that a second hit — such as a new infection — or an intrinsic fibrotic drive can reactivate disease after a latency of four to five years.
The 57-year-old had stable reticulation in 2024; after a March 2025 pneumonia, his forced vital capacity (FVC) fell and early honeycombing appeared by April 2026. The 64-year-old, a never-smoker with prior Hodgkin lymphoma radiotherapy, improved on steroids after his 2021 infection but developed subpleural honeycombing and a >10% drop in diffusing capacity for carbon monoxide (DLCO) in 2025.
Lung scarring can worsen years after COVID-19
- Lung scarring from severe COVID-19 can stay quiet for years, then suddenly worsen — even if you felt fine.
- Antifibrotic drugs like nintedanib and early transplant evaluation are now options when progression is confirmed.
Differential diagnosis remains a minefield
The 57-year-old’s history — asbestos exposure as a plumber, GERD, smoking, and pet birds — created a differential spanning asbestosis, chronic hypersensitivity pneumonitis, GERD-related microaspiration, and connective-tissue-disease ILD. A low-titer ANA (1:40) was the only serologic clue. Transbronchial cryobiopsy and EBUS-guided sampling excluded malignancy, asbestosis, and hypersensitivity pneumonitis but yielded no definitive alternative diagnosis. The 64-year-old’s prior mantle-field radiotherapy for Hodgkin lymphoma added radiation-induced fibrosis to the differential.
Radiologically, post-COVID fibrosis can mimic usual interstitial pneumonia (UIP), nonspecific interstitial pneumonia (NSIP), or organizing pneumonia patterns. The absence of pleural plaques argued against asbestosis in Case 1; the lower-lobe, subpleural predominance argued against classic chronic hypersensitivity pneumonitis. Both cases ultimately fit the PPF behavioral definition rather than a single histologic pattern.
Antifibrotic therapy and transplant referral: the current evidence
Nintedanib, a tyrosine kinase inhibitor targeting VEGF, FGF, and PDGF receptors, is approved for idiopathic pulmonary fibrosis (IPF) and, since the INBUILD trial, for progressive fibrosing ILDs irrespective of etiology.
The INBUILD trial showed a reduction in the rate of FVC decline versus placebo across diverse ILDs (N=663). Pirfenidone, the other approved antifibrotic, has similar data in IPF but less in non-IPF PPF. Neither drug reverses established honeycombing; they slow progression.
| Parameter | Nintedanib (INBUILD) | Pirfenidone (IPF trials) |
|---|---|---|
| Annual FVC decline reduction | ~reduction vs placebo | ~reduction vs placebo (IPF) |
| Common adverse events | Diarrhea, nausea, liver-enzyme elevation | Photosensitivity, nausea, rash |
| Regulatory status for PPF | FDA/EMA approved for progressive fibrosing ILD | Approved for IPF; off-label for non-IPF PPF |
Lung transplantation remains the only curative option for end-stage disease.
Funding and transparency
The case report was published open-access in Cureus with no declared industry funding. The authors disclosed no relevant financial relationships. Nintedanib is marketed by Boehringer Ingelheim; pirfenidone by Genentech/Roche. Neither company had a role in the preparation of this report.
Nintedanib contraindicated in pregnancy, requires liver monitoring
- Nintedanib is contraindicated in pregnancy and requires liver-function monitoring; dose reduction is needed for moderate hepatic impairment (Child-Pugh B).
- Pirfenidone requires photosensitivity precautions and dose adjustment in severe renal impairment (eGFR <30 mL/min).
Earlier coverage: Case Series: Two COVID Survivors Develop Progressive Fibrosis Years Later
