
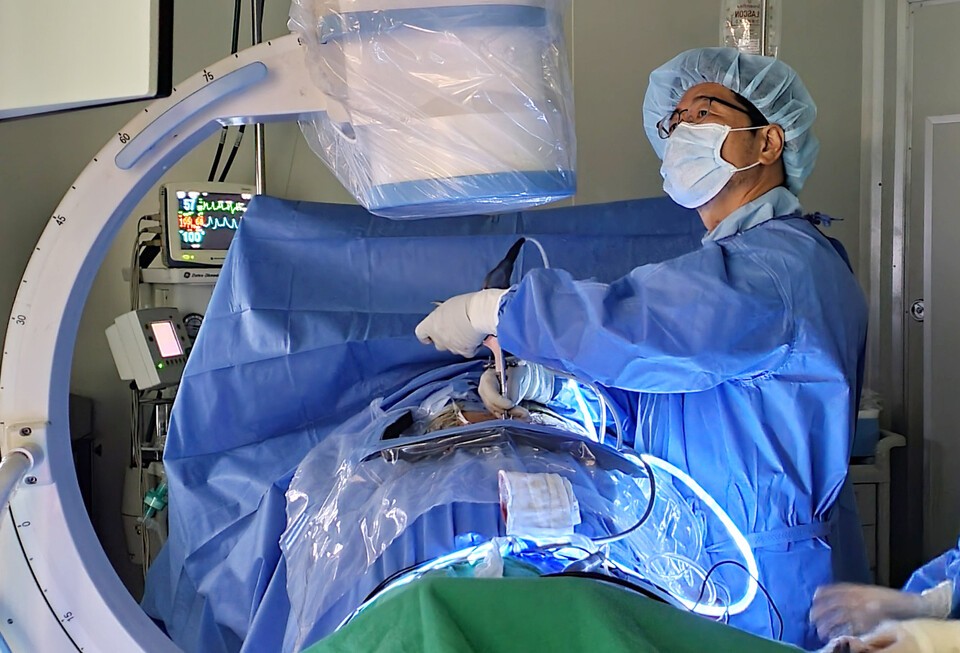
Two incisions smaller than a centimeter each may now be enough to relieve chronic back pain caused by herniated lumbar discs or lumbar spinal stenosis, as spine surgeons increasingly turn to biportal endoscopic surgery for patients who have exhausted non-surgical treatment. Biotimes reported this week on the technique, which uses one port for a camera and one for instruments.
The report, published by Biotimes, describes a minimally invasive option for two of the most common causes of radiating low back pain: lumbar disc herniation — the protrusion of the cushioning disc between vertebrae that compresses nearby nerves — and lumbar spinal stenosis, in which the spinal canal itself narrows and squeezes the nerves passing through it.
Both conditions are appearing in younger patients, the report notes, driven by prolonged sitting, lack of exercise, and poor posture. Pain that is dismissed as simple muscle strain can progress to leg numbness, sensory loss, muscle weakness, and difficulty walking.
“Lumbar disc herniation and spinal stenosis may have similar symptoms, but the cause of the nerve compression and the direction of treatment differ,” said Yang Hee-seok, neurosurgery specialist at Seoul Barunsesang Hospital, according to Biotimes.
Surgery Follows Failed Conservative Treatments
- Surgery is not the first step. Medication, physical therapy, and injection treatments come first; surgery enters the picture when those fail or when leg strength is declining.
- Biportal endoscopic surgery is one option, not a universal one. Severe spinal instability, deformity, or the need for extensive surgery call for different approaches.
How the Two-Port Technique Works
In biportal endoscopic spine surgery, the surgeon makes two incisions, each under about 1 centimeter. An endoscope — a thin camera — goes through one, giving a magnified view of the nerve and surrounding tissue. Instruments go through the other to remove whatever is compressing the nerve: protruding disc material or thickened ligament.
The mechanism of action is decompression, the same goal as open surgery: free the nerve, restore the passageway around it. The difference lies in the route.
That trade-off is where the clinical benefit sits.
Who Is a Candidate — and Who Is Not
The report is explicit that this is not an option for everyone with back pain. Candidates include patients who did not improve sufficiently with conservative treatment, those with recurring nerve compression symptoms, and diagnoses spanning disc herniation, spinal stenosis, foraminal stenosis, and recurrent disc disease.
Older patients and those with diabetes or cardiovascular disease may still be considered, but only after an overall assessment of underlying conditions and anesthesia risk. Magnetic resonance imaging (MRI) — a scan that maps the exact site and degree of nerve compression — is central to that evaluation.
Conversely, significant spinal instability or deformity, or cases requiring extensive surgery, point away from the endoscopic approach toward other treatments.
Two Conditions, One Shared Warning
The two conditions share symptoms but differ in origin, which is why diagnosis drives treatment. In disc herniation, the intervertebral disc — the shock absorber between vertebrae — bulges and presses the nerve; causes include degenerative change, repeated heavy lifting, poor posture, and external trauma.
In stenosis, the canal holding the nerve narrows, and the telltale sign is pain or numbness in the legs after walking a set distance that eases with rest, with the walkable distance shrinking as the disease worsens.
Both carry the same red flag. The report states that progressive paralysis or loss of bowel or bladder control requires prompt medical attention — these are signs of severe nerve compromise, not routine pain.
Recovery follows a staged protocol: light walking first, then gradual return to activity. Full exercise resumes only in step with healing.
“Biportal endoscopic surgery is a treatment that can remove the cause of nerve compression through small incisions, but it cannot be applied identically to all patients. The appropriate treatment method must be selected by comprehensively considering the patient’s age, underlying conditions, and spinal condition based on an accurate diagnosis,” Yang said, according to Biotimes.
Worsening Weakness or Paralysis Demands Urgent Care
Anesthesia and baseline disease risk must be weighed in older patients and those with diabetes or cardiovascular disease.
Seek medical care promptly — beyond routine follow-up — if leg weakness worsens, if paralysis progresses, or if bowel or bladder control is impaired.
The Measured Path Forward
The technique's trajectory, as the report frames it, is one of patient selection rather than replacement: a smaller-incision route to the same decompressive goal, appropriate for some spines and not others.
For context: the report notes these spinal diseases accumulate from everyday load on the spine, which is why they now surface in younger working-age patients and not only in degenerative aging.
References
Treatment decisions, including surgical candidacy, must be made with a qualified physician based on individual diagnosis and imaging.
