

Kenya discharged its last Ebola patient on November 11, just 37 days after the country recorded its first-ever case of the virus.
If no new cases emerge in the following six weeks, Kenya will be officially declared Ebola-free on December 23 — and so far, zero community transmission has been recorded in the country.
That outcome was built on preparation, not chance, according to an opinion column Global Issues published on Thursday by Caroline Kisia.
In June — months before Kenya’s first case on October 6 — the Kenya National Public Health Institute (KNPHI) invited a Ugandan epidemiologist to train some 200 Kenyan health workers in investigating every health alert and every unexplained death, drawing on Uganda’s experience after Ebola outbreaks were declared in Uganda and the Democratic Republic of the Congo.
When the first imported case was confirmed, KNPHI ran twice-weekly virtual training sessions for frontline health workers and surveillance officers across the country. Ugandan lessons on contact tracing, Kisia writes, helped Kenyan officials break the chain of transmission. The numbers behind the response show: Kenya recorded nine confirmed cases and two deaths from 669 samples tested — a positivity rate of 1.35 per cent — with no new case since October 19.
The contrast with the wider regional outbreak is sharp. Africa CDC data put the ongoing multi-country Bundibugyo Ebola outbreak at 10,699 confirmed cases and more than 5,202 deaths.
Kenya held nine cases; the region passed 10,000
At an online press briefing on Thursday, Wessam Mankoula, an Africa CDC official, called Kenya’s containment a continental model. “Kenya is showing a good model on how to contain an Ebola outbreak. When we have one imported case, countries should not be panicking. Investing in preparedness and readiness is what enabled Kenya to respond quickly, efficiently, and control the situation so far,” Mankoula said.
Mankoula also commended Kenya’s contact follow-up, noting that contacts who had left the country were communicated to the destinations they travelled to. “We commend the efforts done by the Kenyan authorities in early detection and also having the measures in place for containing this imported outbreak quickly through identifying all possible contacts, and putting them under quarantine,” he said.
Virtual networks carried the response
The infrastructure behind Kenya’s speed predates the outbreak. Kisia argues in her column for Global Issues that virtual networks — which her organisation, Project ECHO, supports — let KNPHI broadcast essential information to health workers nationwide within days of the first case. She frames them as a permanent investment in local capacity, not a crisis tool.
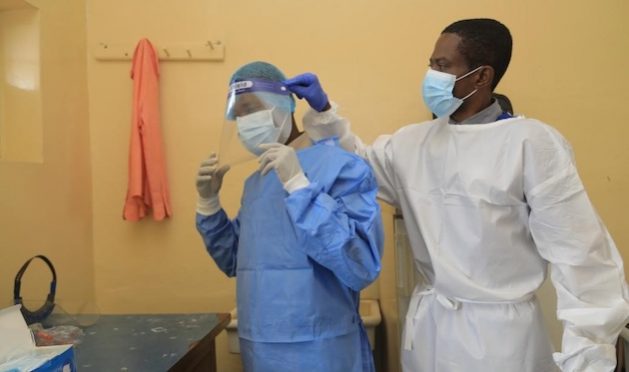
Regional examples back the argument. In Senegal, the Institut Pasteur runs virtual training on hemorrhagic and viral diseases reaching healthcare workers across francophone West Africa. Zambia’s government has embraced virtual learning networks for more than a decade.
Kisia also stresses the community dimension. Local health workers, faith leaders and trusted volunteers often spot unusual health events before formal systems do, and burying the dead in line with local tradition has repeatedly proved decisive in Ebola responses. Recent funding cuts to the WHO and other global health programmes, she writes, have undercut health staffing in many communities, making such networks more essential.
Africa CDC wants pledged funds released
The agency’s praise came alongside a warning. “This is a time for all our member states to invest in preparedness and readiness. Having an imported case should not push us to panic as long as we have the minimum capacity at all critical preparedness pillars,” Mankoula said.
Funding is the sticking point. Of roughly 3 billion US dollars pledged to the outbreak response, only about 1 billion US dollars of the overall pledged amount has been disbursed by donors so far, and Africa CDC has called for the immediate release of the remainder.
Africa CDC is the public health agency of the African Union, headquartered in Addis Ababa, Ethiopia, and tasked with strengthening member states’ capacity to deal with disease threats.
The idea was first proposed by the government of Ethiopia in 2013 at an African Union summit in Abuja, Nigeria, and the agency was officially launched in January 2017 — an effort accelerated by the 2014 Ebola epidemic in West Africa, which shaped its focus on emergency prevention and response.
Since then, the agency has led continental responses to the COVID-19 pandemic and, in August 2024, declared the mpox outbreak a Public Health Emergency of Continental Security as it spread from the Democratic Republic of the Congo. Its data and briefings have become central to how outbreaks like the current Bundibugyo Ebola emergency are tracked across the continent.
Kenya’s own countdown is now fixed: the country will start a 42-day countdown once the last patient recovers, ending on December 23, when the country can be declared Ebola-free if no new cases emerge.
