
Blood eosinophil counts may decide which bronchiectasis patients benefit from inhaled corticosteroids — and which are harmed — suggests a systematic review whose evidence search closed on November 4, 2026.
The review set out to establish whether blood eosinophil counts act as a treatment-effect modifier in adults with non-cystic fibrosis bronchiectasis, weighing both benefit and harm, rather than presuming such an effect exists.
That question matters because prescribing has run ahead of proof. A 2022 narrative review found more than 50% of patients were taking inhaled corticosteroids despite having bronchiectasis not due to asthma, COPD, or eosinophilic diseases — practice that international guidelines generally advise against.
Those guidelines generally advise against their use. The review notes that there is little evidence for the use of inhaled corticosteroids in bronchiectasis.
Eosinophil counts predict exacerbation risk
- Eosinophils are a type of white blood cell. Roughly 20% of patients without asthma have blood eosinophil counts of ≥300 cells/µL.
- Steroid inhalers dampen inflammation, but they also suppress immune defenses — a real concern in a disease dominated by chronic bacterial infection.
- A high eosinophil count is associated with a shorter time to the next exacerbation. Whether it predicts a good response to a steroid inhaler is exactly what the new review set out to test, not assume.
Guidelines say no; prescriptions disagree
Non-cystic fibrosis bronchiectasis is a long-term airway disorder marked by irreversible widening of the bronchi, disrupted mucus clearance, repeated infections, and ongoing inflammation, which together fuel exacerbations, declining lung function, and reduced quality of life. These elements feed a self-perpetuating cycle that drives exacerbations, loss of lung function, and poorer quality of life.
The recorded burden is increasing. In the United Kingdom, prevalence climbed considerably from 2004 to 2013, ultimately reaching about 566 per 100,000 women and 486 per 100,000 men.
Yet inhaled corticosteroids remain among the most frequently prescribed maintenance therapies in bronchiectasis registries, often without a guideline-concordant indication. Their immunosuppressive properties raise particular concern in a condition dominated by chronic bacterial infection, the review notes.
Predicting risk is not predicting response
Bronchiectasis has traditionally been viewed as a neutrophilic disease, but a clinically relevant eosinophilic subset is now characterized. In a European multicohort study, roughly one in five patients without asthma showed blood eosinophil counts of ≥300 cells/µL, and once infection was taken into account, higher eosinophil counts were linked to a shorter interval before the next exacerbation.
Here lies the review’s central distinction. A prognostic biomarker flags patients at higher risk of an outcome regardless of treatment. A predictive biomarker — a treatment-effect modifier — identifies patients in whom a specific drug works differently, and proving that requires a formal treatment-by-biomarker interaction test.
Eosinophilia predicting exacerbations, in other words, does not by itself show that eosinophilia predicts steroid response.
Earlier trials sent mixed signals
Support for the hypothesis came from post hoc analyses of earlier randomized trials, where inhaled fluticasone improved quality of life in patients with higher blood eosinophil levels, and pooled trial data suggested fewer exacerbations among patients with blood eosinophilia who received inhaled corticosteroids.
But the analyses were small and not uniformly concordant. A similar analysis of an inhaled budesonide trial found that blood eosinophils did not predict treatment response. Commentators have since argued that inhaled corticosteroid prescribing in bronchiectasis and COPD should be guided by biomarkers rather than by diagnostic labels.
How the reviewers built the evidence
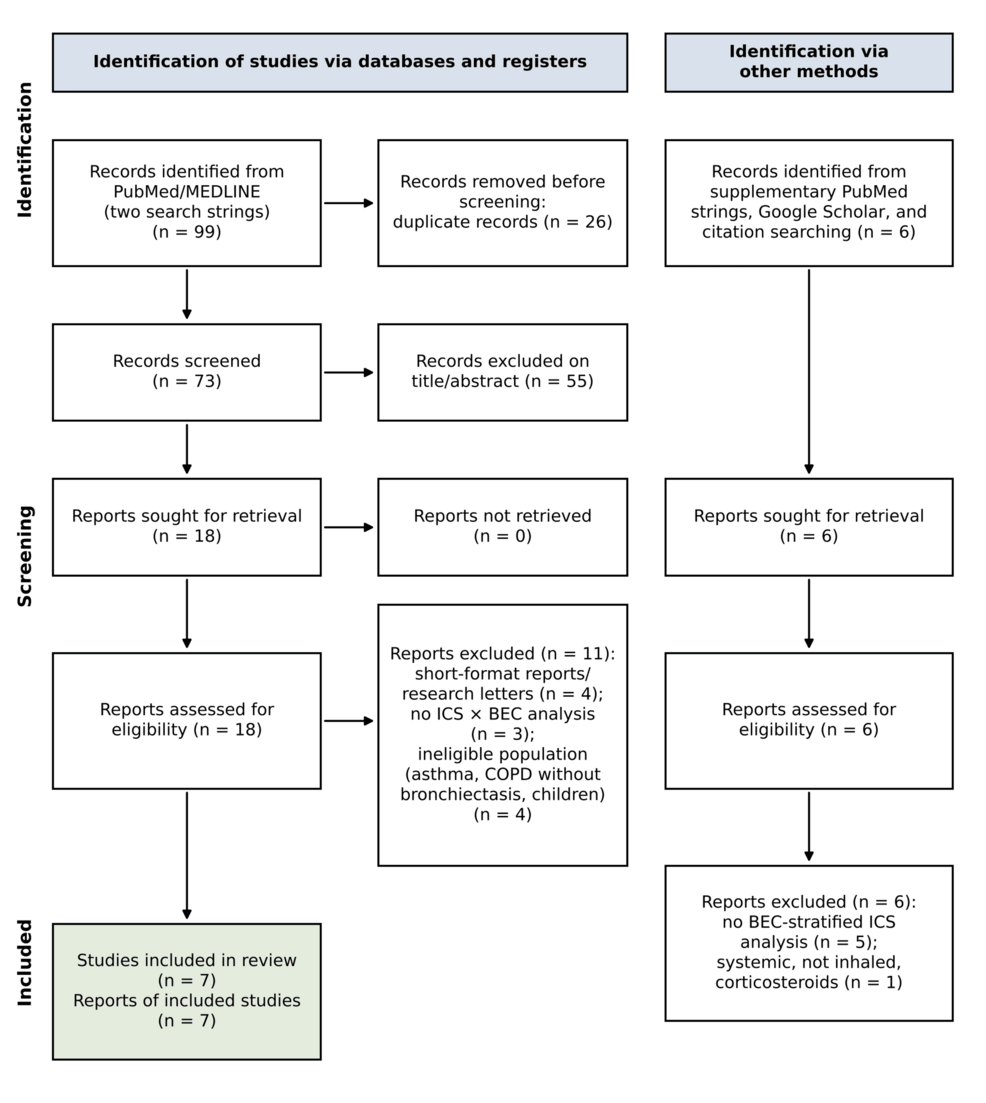
The review followed the PRISMA 2020 reporting standard, and the narrative synthesis was reported with reference to the SWiM guideline.
To qualify, studies had to involve adults (≥18 years) with non-cystic fibrosis bronchiectasis verified by computed tomography or a physician diagnosis, including cases where bronchiectasis coexisted with COPD; assess maintenance inhaled corticosteroids, whether given alone or alongside long-acting bronchodilators; contrast inhaled corticosteroid users against non-users or against inhaled regimens free of inhaled corticosteroids; and present a clinical outcome across at least two blood eosinophil count strata, a blood eosinophil count-by-inhaled corticosteroid interaction, or a blood eosinophil count threshold predicting inhaled corticosteroid response.
Only peer-reviewed original research qualified; reviews, meta-analyses, editorials, letters, conference abstracts, case reports, protocols, and preprints were excluded.
No meta-analysis was performed. Because the included studies varied in eosinophil thresholds, comparators, outcomes, and effect measures, the findings were combined through narrative synthesis, organized by outcome domain and by population: bronchiectasis without inhaled corticosteroid-responsive comorbidities, bronchiectasis-COPD overlap or bronchiectasis with airflow obstruction, and general bronchiectasis cohorts in which COPD was not an exclusion criterion.
The numbers behind the question
| Figure | Value | Origin |
|---|---|---|
| Bronchiectasis patients without asthma with eosinophils ≥300 cells/µL | ~20% | European multicohort study |
| Patients taking ICS without asthma, COPD, or eosinophilic disease | >50% | 2022 narrative review |
| UK prevalence, women (2004–2013) | 566 per 100,000 | UK epidemiological data |
| UK prevalence, men (2004–2013) | 486 per 100,000 | UK epidemiological data |
On process transparency, the review states that its protocol was defined a priori but was not prospectively registered.
Who should question inhaled steroids
For patients with bronchiectasis, international guidelines generally advise against the use of inhaled corticosteroids. Yet more than 50% of patients with bronchiectasis not due to asthma, COPD, or eosinophilic diseases take them anyway, according to the 2022 narrative review.
The infection risk is not hypothetical. Because inhaled corticosteroids are immunosuppressive, and because bronchiectasis is dominated by chronic bacterial bronchial infection, the drugs can induce an increase in bacterial infections.
Where the eosinophil hypothesis stands
What the new review deliberately refuses to do is presume that effect modification exists. By demanding direct comparisons of treatment effects across blood eosinophil count strata — and by separating bronchiectasis-alone evidence from bronchiectasis-COPD overlap — it tests the biomarker hypothesis on its merits.
The reviewers searched PubMed/MEDLINE from inception to November 4, 2026, supplemented by Google Scholar, additional free-text PubMed strings, and backward and forward citation screening.
References
- Blood Eosinophils as a Modifier of Inhaled Corticosteroid Treatment Effects in Adults With Non-Cystic Fibrosis Bronchiectasis: A Systematic Review
- Inhaled Corticosteroids in Adults with Non-cystic Fibrosis Bronchiectasis: From Bench to Bedside. A Narrative Review (2022), indexed via Europe PMC
