
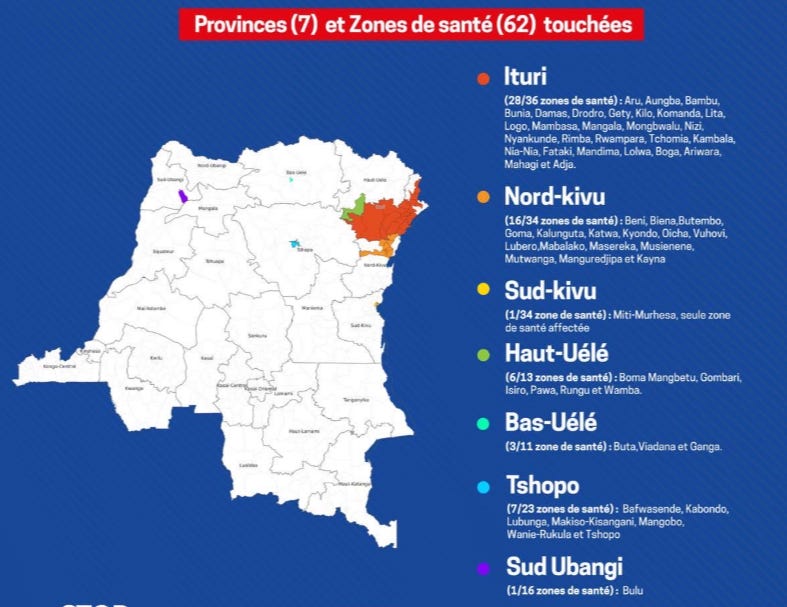
Public health authorities report that the ongoing Ebola outbreak in the Democratic Republic of the Congo (DRC) and Uganda—spanning mid-May through mid-September—has become the largest Bundibugyo outbreak on record, prompting cautious optimism from the World Health Organization (WHO) as infection rates begin to slow amid complex regional conflict.
In Plain English: The Clinical Takeaway
- The Strain: This outbreak involves the Bundibugyo outbreak, identified primarily through clusters originating among healthcare workers in Central Africa.
- US Risk Assessment: According to the Centers for Disease Control and Prevention (CDC), the overall risk of importation and secondary transmission within the United States remains low due to robust clinical infection control measures.
- Local Health Realities: Response efforts continue to battle significant barriers, including active regional conflict and limited healthcare infrastructure in the affected areas.
Navigating the Largest Bundibugyo Outbreak on Record
Between mid-May and mid-September, international public health agencies closely monitored an evolving Ebola crisis centered in the Democratic Republic of the Congo and neighboring Uganda. First detected among clusters of healthcare workers, this event officially marks the 17th Ebola outbreak in the DRC. According to CDC Incident Manager for the Ebola response, CAPT Satish K. Pillai, M.D., M.P.H., the situation remains serious due to the sheer scale of transmission and difficult on-the-ground conditions.
“This is an active Ebola outbreak, and CDC is working aggressively with federal and international partners to support response efforts,” Dr. Pillai stated during a media briefing. He emphasized that populations in the DRC and Uganda are navigating extraordinary challenges within communities already strained by conflict, limited health infrastructure, and severe barriers to care.
Assessing Global Spread and United States Risk Metrics
As international teams coordinated containment strategies, public health officials in Washington evaluated potential downstream effects on Western healthcare systems. Importation modeling conducted by federal forecasting partners indicates that the mathematical likelihood of the Ebola virus reaching the United States remains low. Furthermore, federal modeling suggests that if an isolated case were imported, the probability of sustained secondary transmission is similarly low, thanks to stringent clinical infection control protocols and modern hospital infrastructure.
To quantify these operational realities, federal health organizations published comprehensive notes detailing transmission dynamics and containment logistics:
| Metric Category | Reported Status / Finding | Primary Agency Attribution |
|---|---|---|
| Outbreak Scale | Largest Bundibugyo outbreak on record | CDC |
| US Importation Risk | Low likelihood based on current epidemiological modeling | CDC |
| Secondary Transmission Risk (US) | Low, backed by established clinical infection control measures | CDC |
| Primary Index Clusters | Initially detected among frontline healthcare workers | CDC |
Evolving International Perspectives: Progress and Caution
By late summer, multi-agency evaluations from the United Nations, Reuters, The Guardian, and STAT reflected a shifting trajectory on the ground. While the United Nations reported some progress in the fight against the virus in the Congo, authorities cautioned that declaring a definitive peak remains a delicate operational judgment. By mid-September, local authorities and STAT correspondents noted that infection rates had begun to slow, allowing the WHO to express cautious optimism regarding containment bids.
These developments highlight the intricate balance required in modern epidemiological responses. While slower transmission rates point toward eventual stabilization, the historical persistence of filoviruses in Central Africa necessitates continuous surveillance, community engagement, and resource allocation.
Contraindications & When to Consult a Doctor
For individuals residing in or traveling to non-affected regions, including the United States, federal health agencies emphasize that no changes to daily behavior or travel restrictions are recommended unless itineraries involve active outbreak zones.
Conclusion
The multi-month span from May to September underscores both the resilience of international public health networks and the persistent fragility of healthcare systems in conflict-affected zones. While current epidemiological trends in Central Africa demonstrate encouraging signs of deceleration, continued vigilance, funding, and cross-border cooperation remain essential to extinguishing the outbreak permanently.
References
- Centers for Disease Control and Prevention (CDC): Update on Ebola Outbreak in the Democratic Republic of the Congo and Uganda.
- World Health Organization (WHO): Situation Reports and Cautious Optimism Statements on DRC Outbreak Management.
- Reuters: United Nations Progress Reporting on Congo Ebola Fight.
- The Guardian: DRC Outbreak Peak Analysis and Infection Rate Tracking.
- STAT: WHO Optimism and Containment Bid Evaluations in Central Africa.
Disclaimer: This article is for informational and educational purposes only and does not substitute for professional medical advice, diagnosis, or treatment. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a medical condition.
Related reading
- Deadliest Ebola Outbreak in Congo History: Thousands Infected
- Actor Hyun Bong-sik Confesses Severe Burnout, Hair Loss, and Sleep Disorder
- Congo Starts Ebola Vaccinations for Health Workers in Outbreak Epicenter (world-today-news.com)
- Progress 96 Spacecraft Delivers Three Tons of Cargo to ISS (newsy-today.com)
