
Federal lawmakers are currently advancing legislation to cap monthly insulin out-of-pocket costs for privately insured Americans, building on momentum from state-level protections and the 2022 Inflation Reduction Act.
This policy shift targets the financial barriers faced by millions of U.S. adults who rely on insulin to manage blood glucose levels.
Nearly 29 million U.S. adults live with diabetes, and approximately 32% of them require insulin for survival and metabolic stability. For these patients, the high list price—or Wholesale Acquisition Cost (WAC)—often dictates their financial burden, particularly before they meet annual insurance deductibles. A 2024 KFF poll revealed broad bipartisan support for expanding cost-sharing protections, with 84% of Democrats and 70% of Republicans in favor of federal caps.
- Cost-Sharing vs. Price: A cap limits what a patient pays at the pharmacy counter (copayment), but it does not lower the underlying list price set by manufacturers or the negotiated rates between pharmacy benefit managers (PBMs) and insurers.
- Formulary Design: Insurance plans often favor high-list-price insulins because they generate larger rebates—discounts paid by manufacturers to PBMs—which can inadvertently disadvantage lower-priced biosimilars.
- Predictable Out-of-Pocket Spend: By standardizing copayments at $35 or less, these caps aim to prevent the “doughnut hole” effect where patients skip doses due to temporary financial spikes, directly impacting glycemic control and reducing the risk of acute hyperglycemic crises.
The push for federal intervention follows a Senate Finance Committee investigation identifying how manufacturers and the three largest PBMs—CVS Caremark, Express Scripts, and Optum Rx—interact. The committee said that manufacturers often raised list prices in lockstep, while PBMs utilized rebates to secure preferred placement on drug formularies.
This cycle has historically kept out-of-pocket costs high for patients whose insurance design relies on coinsurance, where the patient pays a percentage of the drug’s price rather than a flat fee.
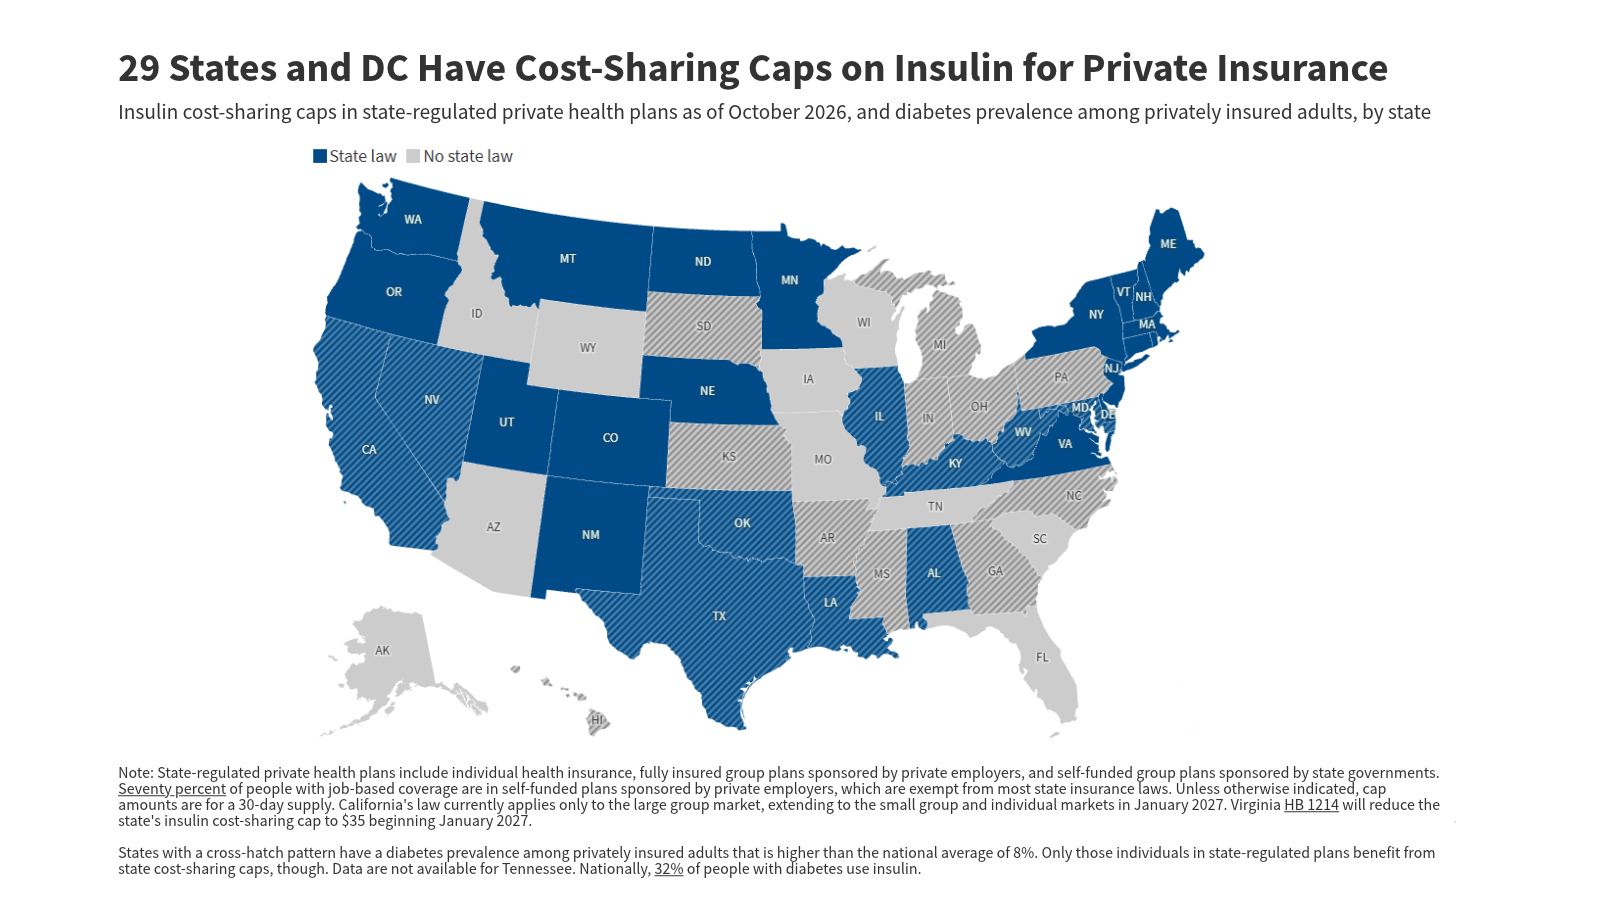
Recent federal actions have attempted to disrupt this dynamic. The Inflation Reduction Act successfully capped insulin at $35 for Medicare beneficiaries, leading to a 50% decrease in out-of-pocket costs for that demographic between 2020 and 2024. However, private sector coverage remains fragmented. As of October 2026, 29 states and the District of Columbia have enacted their own cost-sharing caps for state-regulated plans, but these do not reach the majority of Americans covered by self-funded employer plans.
“The practice of offering rebates in the insulin therapeutic class appears to be contributing to both increasing insulin WAC prices and limited uptake of lower-priced products.”
In 2019, the Senate Finance Committee began an investigation into rising insulin prices, which led to a 2021 report examining the roles of major insulin manufacturers and pharmacy benefit managers.
| Mechanism | Status/Impact |
|---|---|
| Medicare Part D | $35 monthly cap (Established by IRA 2022) |
| State-Regulated Plans | Caps enacted in 29 states ($0–$100 range) |
| Manufacturer Programs | Voluntary $35 caps via retail pharmacy programs |
| HSA-Qualified Plans | Pre-deductible coverage allowed for insulin |
Regulatory pressure is also mounting via the Federal Trade Commission (FTC). In 2026, the FTC reached settlements with Express Scripts and CVS Caremark, requiring them to modify rebate practices by 2028. These agreements may eventually let cash payments for insulin count toward a patient’s deductible—a major change for people who often use discount platforms like GoodRx or manufacturer coupons.
While alternative pathways like California’s CalRx biosimilar production and direct-to-consumer online pharmacies offer new avenues for access, their long-term impact on systemic affordability remains under observation.
- KFF’s issue brief examines the evolution of insulin cost-sharing caps, including existing state laws, proposed federal legislation, and policy considerations for improving affordability.
