
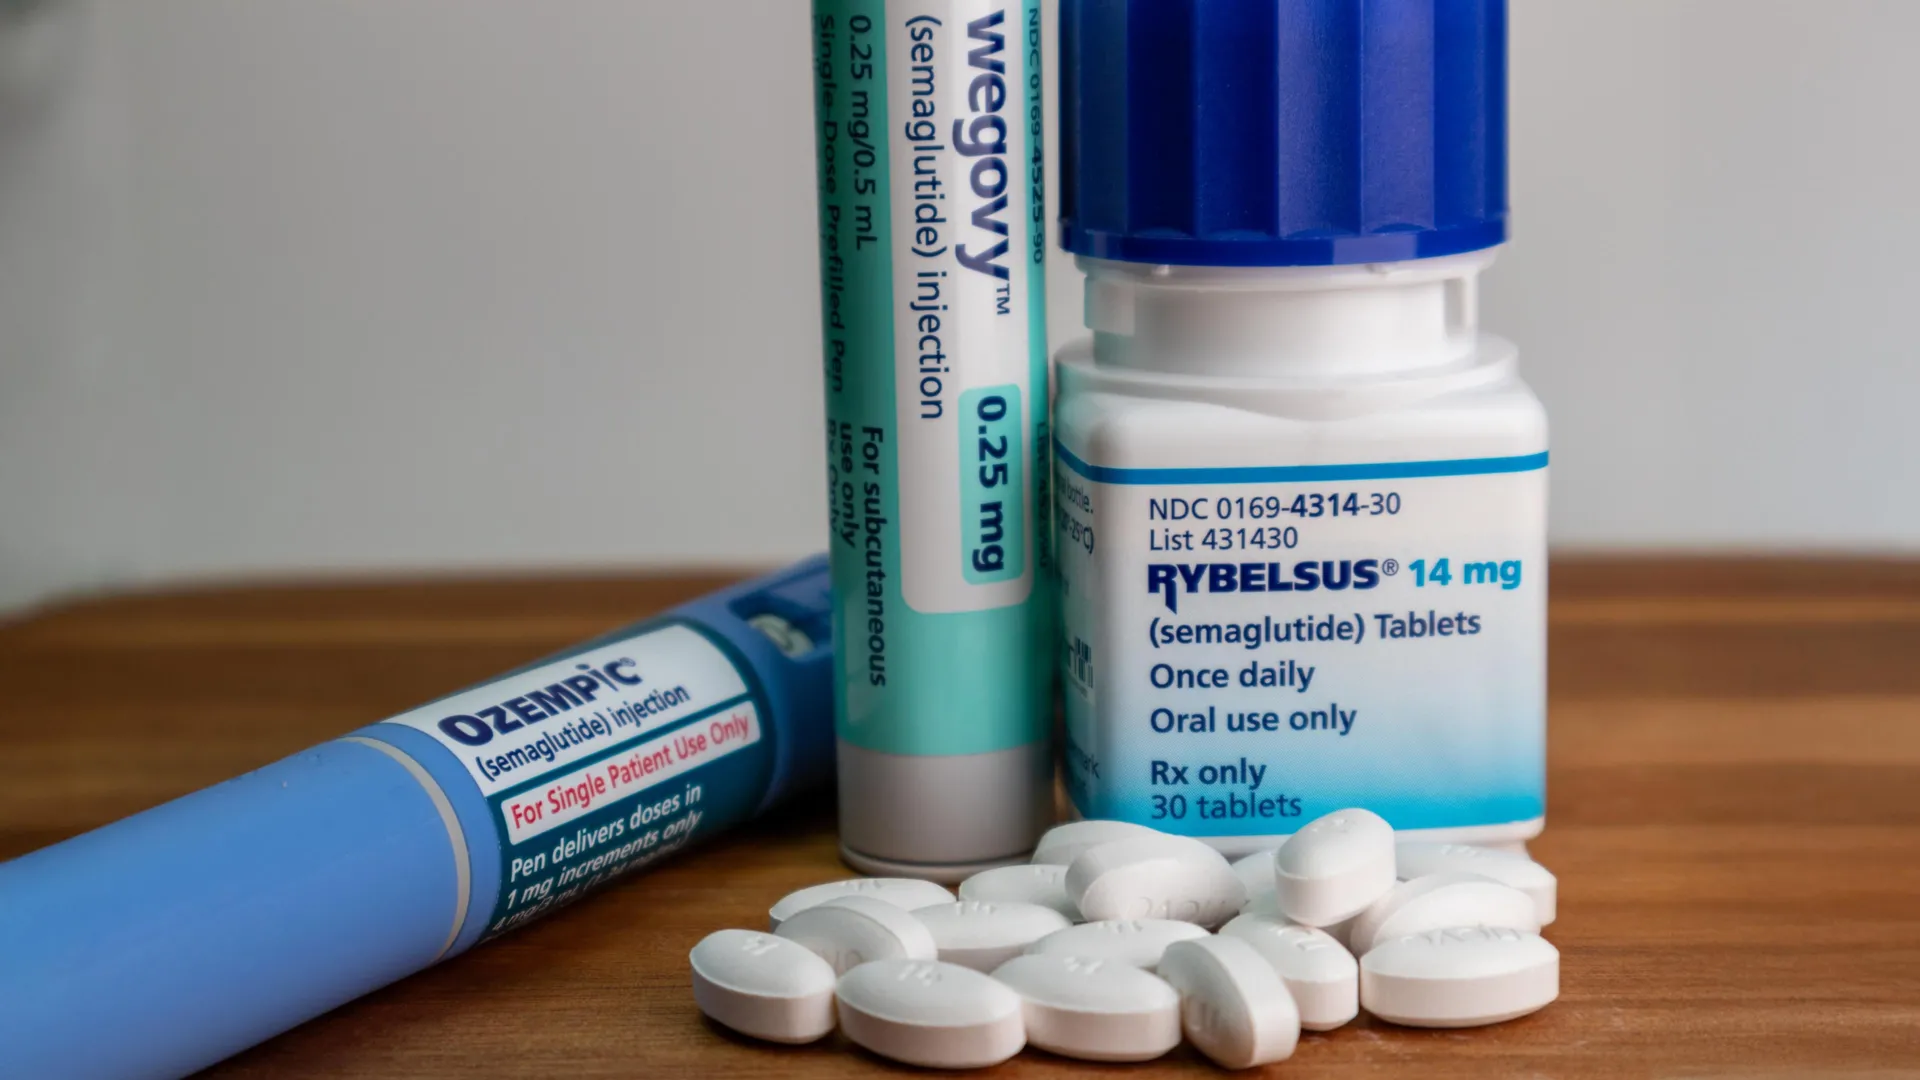
GLP-1 drugs like Ozempic and Wegovy cut body weight by an average of 15 percent over 68 weeks, yet they do not work the same way for everyone — and researchers point to metabolism, genetics and side effects as the reasons why.
That gap between responders and non-responders is the focus of a multidisciplinary team at the University of Alberta, which outlined its work to explain why semaglutide — the drug behind both Ozempic and Wegovy — fails some of the people it is prescribed for, ScienceDaily reported. The team is recruiting patients with insulin resistance or Type 2 diabetes who are about to start the medication and will track them for six months.
Their central hypothesis concerns energy metabolism: the balance between calories consumed and calories burned. When weight drops, the body needs less fuel — but sometimes it shifts into what researchers call metabolic adaptation, burning fewer calories than expected and stalling progress. Think of it like a light bulb that automatically dims to save electricity, the Alberta team explained in the report it published this week.
Prof. Roy Taylor, an emeritus professor of medicine and metabolism at Newcastle University, said that individuals vary in their response to drugs.
Why the scale stalls for some patients
Metabolic adaptation, also called adaptive thermogenesis, is one established reason weight loss slows over time. Both fat and fat-free mass burn energy even at rest, so as those tissues shrink, daily calorie expenditure falls with them. What remains unresolved — and what the Alberta team calls an open question — is whether semaglutide changes these processes differently in different people.

The team published a recent review of studies examining how GLP-1 therapies affect energy utilization and found only a handful of trials measuring resting energy use. Those findings were neutral or inconclusive. Hence the whole-room indirect calorimeter: a rare, hotel-suite-sized chamber that can isolate calorie burning at rest, after eating and during exercise, and track how each component shifts over six months of treatment.
Averages mask wide weight loss variation
- Average isn’t everyone. Semaglutide trials show about 15 percent average weight loss over 68 weeks — but averages hide people who lose far more and people who lose almost none.
- Weight loss isn’t the only success measure. The medications also improve blood sugar, cholesterol, strength and quality of life, so a “non-responder” on the scale may still be a responder clinically.
- Metabolic adaptation is real, not weakness. The body genuinely burns fewer calories as weight drops, which is why plateaus occur even when patients follow instructions.
What patients can control, what they cannot
Continuing to eat high-calorie foods can blunt the drugs’ appetite-dulling effect, and a 2024 study found that adding supervised exercise produced greater weight loss and better odds of keeping it off than medication alone.
Side effects are a bigger driver of failure than most patients expect. A New England Journal of Medicine trial found 74.2 percent of GLP-1 participants experienced nausea, diarrhea or vomiting, and 4.5 percent withdrew because of severe symptoms. Prof. Roy Taylor of Newcastle University warned that many people take these drugs without medical supervision, and that early nausea — which typically eases over time — should be explained upfront.
“If this is not explained – and especially so if people are taking these drugs without medical supervision, as many people are – then this is a really potent issue,” Prof. Roy Taylor, an emeritus professor of medicine and metabolism at Newcastle University, said.
Genetics plays a documented role too. A Nature study of nearly 28,000 users linked one genetic variant to a higher likelihood of nausea and vomiting, which in turn raises the odds someone abandons treatment before it takes hold. Taylor, however, dismissed poor sleep as a major factor, describing sleep’s metabolic effects as “trivial” and noting that disrupted sleep in heavier people frequently stems from their weight itself.
The head-to-head numbers behind the debate
| Outcome | Figure | Source |
|---|---|---|
| Average weight loss, semaglutide, 68 weeks with lifestyle changes | 15 percent | ScienceDaily |
| Average weight loss, tirzepatide, recent head-to-head trial | About 20 percent | EURweb / Science Focus |
| Average weight loss, semaglutide, same trial | About 14 percent | EURweb / Science Focus |
| Tirzepatide users losing 30 percent or more | About one in five | EURweb / Science Focus |
| GLP-1 participants with nausea, diarrhea or vomiting | 74.2 percent | New England Journal of Medicine, via EURweb |
| Participants withdrawing for severe symptoms | 4.5 percent | New England Journal of Medicine, via EURweb |
The head-to-head figures come from a comparative trial reported through Science Focus, and the symptom figures come from a peer-reviewed New England Journal of Medicine trial.
How this reaches the clinic — and when it will
Work like the Alberta calorimeter study aims at the next step — identifying likely non-responders early so clinicians can offer alternatives sooner rather than after months of failed treatment.
The team is currently recruiting participants with blood sugar regulation issues, including insulin resistance or diabetes, who are about to begin semaglutide. Six months of follow-up will track changes in weight, body composition and measured energy use.
“ensure that people are aware of what's about to happen,” Prof. Roy Taylor, an emeritus professor of medicine and metabolism at Newcastle University, said.
Consult clinician before starting or stopping
- Taylor specifically flagged people taking these drugs without medical supervision as a potent concern; consult a clinician before starting or stopping any GLP-1 medication.
- Nausea, diarrhea and vomiting affected nearly three-quarters of trial participants; if symptoms are severe enough to threaten hydration or cause withdrawal from eating, seek medical assessment promptly.
- Do not self-adjust the dose. Taylor said that with the right dose and clinician guidance, genetic and side-effect obstacles can usually be managed — a decision for a prescriber, not a patient alone.
The trajectory, if the Alberta work and comparable studies elsewhere bear fruit, is toward personalized obesity care: predicting before the first injection who will respond, and matching the small fraction who will not to alternatives earlier in their health journey.
References
- Wilding JPH et al., Once-Weekly Semaglutide in Adults with Overweight or Obesity, New England Journal of Medicine — doi.org/10.1056/NEJMoa2032183
- Lincoff AM et al., JAMA — doi.org/10.1001/jama.2025.24288
- JAMA Network Open — doi.org/10.1001/jamanetworkopen.2024.57232
- Molecular Metabolism (semaglutide CNS mechanism) — doi.org/10.1016/j.molmet.2019.09.010
- ScienceDaily, Why don’t weight-loss drugs like Ozempic and Wegovy work for everyone? (University of Alberta team); EURweb, drawing on Science Focus.
Consult a qualified healthcare professional before starting, stopping or changing any prescription medication.
