
A prospective study at Bangladesh Medical University found clinically diagnosed nosocomial infections in two-thirds of postoperative maxillofacial surgery patients requiring intensive care, with Klebsiella pneumoniae and Acinetobacter species driving a Gram-negative epidemic resistant to last-line carbapenems.
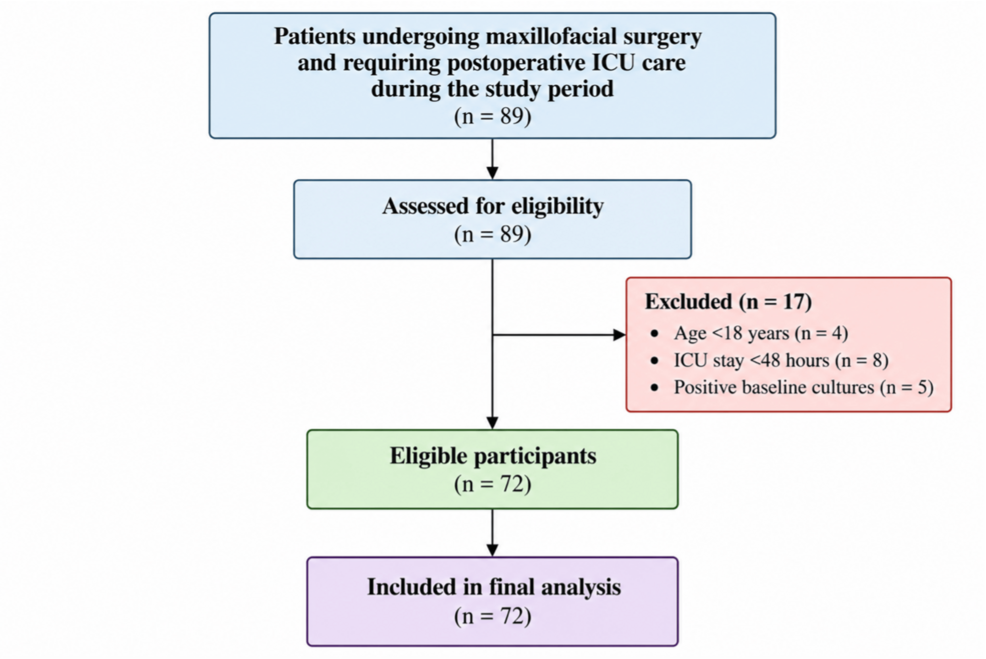
The research, published in Cureus, tracked 72 adult patients admitted to the ICU for at least 48 hours following maxillofacial procedures between July 2024 and July 2025. Investigators collected baseline cultures immediately after surgery and repeat specimens at or after 48 hours in the ICU to distinguish hospital-acquired infections from preexisting colonization.
Infections were identified in 48 patients, a frequency of 66.7%. Respiratory tract infections dominated, accounting for 42 cases (87.5%), while bloodstream infections comprised the remaining six (12.5%). Gram-negative pathogens constituted 93.8% of all isolates, led by Klebsiella pneumoniae (50.0%) and Acinetobacter spp. (25.0%).
“The predominance of Gram-negative bacilli, particularly Klebsiella and Acinetobacter, with high resistance to meropenem, severely limits empirical therapeutic options in our setting,” the study authors wrote. Meropenem susceptibility was confirmed in only 20.8% of K. pneumoniae isolates and 0% of Acinetobacter isolates.
Two-Thirds of ICU Patients Develop Resistant Infections
- Two out of three maxillofacial surgery patients in this ICU developed a new infection after 48 hours, mostly pneumonia caused by tough Gram-negative bacteria.
- The bacteria found — mainly Klebsiella and Acinetobacter — are often resistant to carbapenems, the “last resort” antibiotics, leaving very few treatment options.
- Every additional 30 minutes in the operating room raised the odds of infection by 74%, making surgical efficiency and strict sterile technique critical prevention targets.
Operative Duration Emerges as Independent Risk Factor
Mean operative duration was significantly longer in infected patients (200.1 ± 45.5 minutes) versus non-infected patients (156.1 ± 54.4 minutes). In multivariable logistic regression adjusting for comorbidities and device use, each additional 30 minutes of surgery carried an adjusted odds ratio of 1.74 (95% CI: 1.21–2.51; p = 0.003) for nosocomial infection.
The association aligns with established surgical literature linking prolonged tissue exposure, hypothermia, and impaired immune function to surgical site and systemic infections. Maxillofacial procedures often involve complex reconstruction, tumor resection, or trauma repair requiring extended operative times and postoperative airway management.
Microbiological Profile Mirrors Regional Resistance Crisis
The pathogen distribution reflects a broader South Asian antimicrobial resistance (AMR) epidemiology. Surveillance data from the region consistently identify Klebsiella pneumoniae and Acinetobacter baumannii as leading ICU pathogens with escalating carbapenem resistance, driven by widespread carbapenemase production (NDM, OXA-48-like).
A 2023 systematic review of ICU-acquired infections in South Asia reported pooled carbapenem resistance rates exceeding 70% for K. pneumoniae and 80% for A. baumannii, comparable to the near-total meropenem non-susceptibility observed in this cohort. The absence of Pseudomonas aeruginosa among the leading isolates in this study contrasts with some Western ICU datasets but aligns with local Bangladeshi reports where Acinetobacter often surpasses Pseudomonas in ventilator-associated pneumonia.
Prospective Design Strengthens Inference but Sample Size Limits Precision
The prospective design with baseline microbiological screening strengthens causal inference by excluding patients with positive preoperative cultures. However, the authors acknowledge several limitations. The sample size calculation targeted infection frequency estimation (anticipated proportion 26.9%, precision 11%) rather than power for multivariable analysis, potentially limiting precision of adjusted odds ratios.
Susceptibility testing methods, CLSI/EUCAST breakpoints, and quality-control procedures were not standardized or retrospectively reinterpreted; laboratory-reported classifications were accepted as recorded. The single-center design at a tertiary referral hospital may not generalize to district-level facilities with different case mixes and microbiology capacity.
The operational definition relied on clinical diagnosis plus culture positivity at or after 48 hours post-ICU admission. While this captures ICU-associated infections, it does not definitively prove ICU acquisition versus postoperative manifestation of intraoperative contamination.
Implications for Antimicrobial Stewardship and Infection Control
The findings reinforce the need for bundled interventions: strict adherence to ventilator-associated pneumonia prevention bundles, minimized operative duration through surgical planning and team coordination, and strong antimicrobial stewardship programs guided by local susceptibility data.
Empirical carbapenem therapy for suspected ventilator-associated pneumonia in this setting would be ineffective in 80–100% of Gram-negative cases. Alternatives such as colistin, tigecycline, or novel beta-lactam/beta-lactamase inhibitor combinations (ceftazidime-avibactam, meropenem-vaborbactam) remain limited by cost, availability, and nephrotoxicity in resource-constrained environments.
Contraindications & When to Consult a Doctor
This study describes observational epidemiology, not a therapeutic intervention. Patients undergoing maxillofacial surgery should discuss infection prevention protocols with their surgical and anesthesia teams preoperatively. Postoperatively, any new fever, purulent sputum, hemodynamic instability, or worsening oxygen requirements after ICU admission warrant immediate clinical evaluation for nosocomial infection. Self-medication with antibiotics is contraindicated and accelerates resistance.
Bangladesh Medical University, established in 1965 as the Institute of Postgraduate Medicine and Research, serves as the country’s premier postgraduate medical institution and a tertiary referral hospital. A 750‑bed super‑specialised hospital opened on its Dhaka campus in 2022, expanding capacity for complex surgical care such as the maxillofacial procedures tracked in the study.
The research team plans to extend surveillance to include molecular characterization of resistance mechanisms and clinical outcome correlation in a multicenter cohort.
References
- Cureus. Nosocomial Infections and Associated Risk Factors Among Postoperative Maxillofacial Surgery Patients in Intensive Care: A Prospective Observational Study. Published 2025.
- World Health Organization. Global Antimicrobial Resistance and Use Surveillance System (GLASS) Report 2023.
- Khan MA, et al. Antimicrobial resistance patterns in ICU-acquired infections across South Asia: A systematic review and meta-analysis. J Hosp Infect. 2023.
- Centers for Disease Control and Prevention. Ventilator-Associated Pneumonia (VAP) Prevention Guidelines. Updated 2022.
- Clinical and Laboratory Standards Institute (CLSI). Performance Standards for Antimicrobial Susceptibility Testing. 34th ed. CLSI supplement M100. 2024.
