
Bacterial antimicrobial resistance was estimated to have directly caused approximately 1.27 million deaths worldwide in 2019, and a new meta-analysis published in Cureus finds that newer antibiotic combinations outperform the toxic legacy drugs long used as a last resort. The review, registered with PROSPERO and completed in June 2026, pools comparative evidence on ceftazidime-avibactam, cefiderocol and related regimens against colistin-based therapy for these infections.
Carbapenem-resistant Enterobacterales, or CRE, are gut bacteria that have grown impervious to carbapenems — the drugs doctors reach for when little else works. The CDC classifies CRE as an urgent threat, and the WHO ranks these pathogens as critical priorities needing new treatments, Cureus reported in the review.
What the pooled evidence shows is consistent across eight comparative studies: the newer agents, chiefly ceftazidime-avibactam, produced higher clinical cure rates and far less kidney damage than colistin-based regimens, which remain in widespread use because they are cheap and generic.
Newer drugs match or beat older therapy for CRE infections
- CRE infections are hard to treat because the bacteria make enzymes — carbapenemases — that destroy last-line antibiotics.
- Newer drugs like ceftazidime-avibactam matched or beat older salvage therapy in cure and survival across the studies reviewed, with less harm to the kidneys.
- The right drug depends on which enzyme the bacteria carry; matching the drug to the mechanism matters more than adding more antibiotics blindly.
Ceftazidime-avibactam outperforms colistin where it counts
The single clearest signal comes from studies of bloodstream infections. In a matched Italian cohort of 208 patients with KPC-producing Klebsiella pneumoniae bacteremia, 30-day mortality was 36.5% with ceftazidime-avibactam salvage therapy versus 55.8% with conventional regimens — a difference the Cureus review reports as statistically significant.
A US cohort from the University of Pittsburgh Medical Center of 109 patients with carbapenem-resistant K. pneumoniae bacteremia showed 30-day survival of 92% with ceftazidime-avibactam versus 69% with older combinations, with less nephrotoxicity favoring the newer drug.
Kidney injury is where the older therapy loses most visibly. In a Saudi multicenter cohort of 230 patients, acute kidney injury occurred in 15% of ceftazidime-avibactam recipients versus 33% of those on colistin-based regimens, Cureus reported. Colistin — a polymyxin antibiotic from the 1950s — works but damages the kidneys and nerves, which is why the newer β-lactam/β-lactamase inhibitor combinations have displaced it in many centers.
The resistance mechanism decides which drug works
Not every new agent covers every enzyme. Ceftazidime-avibactam disables serine carbapenemases such as KPC and some OXA-48-like enzymes, but it has no activity against metallo-β-lactamases — NDM, VIM and IMP — which are prevalent in South Asia and spreading worldwide.
For those organisms, the evidence points to a combination strategy. In an Italian and Greek prospective cohort of 102 patients with bloodstream infection from metallo-β-lactamase-producing Enterobacterales, ceftazidime-avibactam plus aztreonam cut 30-day mortality to 19.2% versus 44% with other active antibiotics. Aztreonam is the one β-lactam these metallo-enzymes cannot destroy, and pairing it with a protected partner closes that gap.
Cefiderocol, a siderophore cephalosporin that tricks bacteria into importing the drug through their iron-uptake machinery, showed comparable efficacy to best available therapy in the Enterobacterales subgroup of the CREDIBLE-CR randomized trial across 16 countries — clinical cure of 66% versus 45% — though the trial-wide mortality imbalance was driven mainly by Acinetobacter infections, not CRE.
What the evidence still cannot say
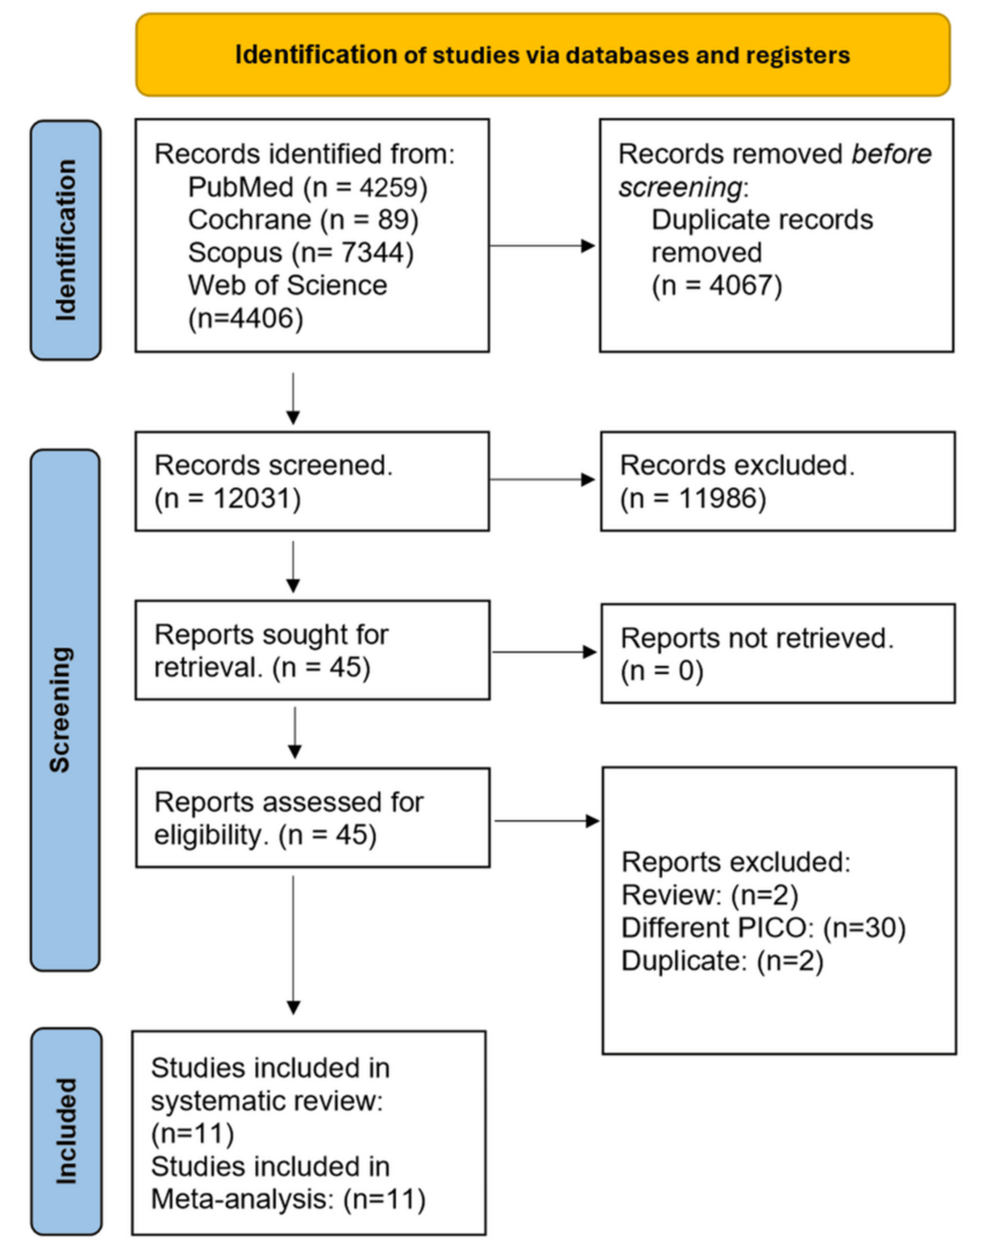
The review’s own methods section is candid about the limits. Most comparative data, particularly for ceftazidime-avibactam, come from observational cohorts rather than randomized trials, and the pooled analyses used unadjusted event counts. Regimen-specific and carbapenemase-specific meta-analyses were not performed because too few comparable studies existed in each category.
The search covered PubMed/MEDLINE, Cochrane CENTRAL, Web of Science and Scopus through June 2026; Embase was not searched, and the authors acknowledge studies indexed only there may have been missed. Emerging resistance to the newer agents themselves is already reported, which strengthens the case for mechanism-directed therapy and antimicrobial stewardship rather than reflexive escalation.
How the numbers compare
| Study | Population | Intervention outcome | Comparator outcome |
|---|---|---|---|
| Tumbarello et al. | KPC bacteremia, Italy | 36.5% 30-day mortality | 55.8% 30-day mortality |
| Shields et al. | CRKP bacteremia, US | 92% 30-day survival | 69% 30-day survival |
| Almangour et al. | Mixed CRE, Saudi Arabia | 15% AKI | 33% AKI |
| Falcone et al. | MBL bloodstream infection | 19.2% 30-day mortality | 44% 30-day mortality |
Access differs by system. Ceftazidime-avibactam and cefiderocol carry premium pricing and, in the US, Food and Drug Administration approval for complicated urinary and intra-abdominal infections and hospital-acquired pneumonia; European regulators through the EMA have approved comparable indications.
In lower-income settings where NDM enzymes are endemic, the drugs that cover those mechanisms may simply not be on the formulary — which is why the review’s finding that targeted ceftazidime-avibactam reduced 30-day mortality in leukemia patients in Lima, Peru, matters as much as any pooled ratio.
These drugs need renal dose adjustment and allergy review
These agents are intravenous hospital therapies for confirmed or strongly suspected CRE infections; they are not outpatient or preventive options. Ceftazidime-avibactam and cefiderocol require renal dose adjustment, and patients with known β-lactam allergy, prior anaphylaxis to cephalosporins, or active kidney disease should have the regimen reviewed by an infectious-diseases physician before starting.
Anyone being treated for a CRE infection who develops decreasing urine output, swelling, rash or new breathing difficulty should tell the treating team promptly — these can signal kidney injury or drug reaction. Decisions about therapy belong with the clinical team and a microbiology report identifying the carbapenemase type; no finding in this review changes that.
The journal carrying the review, Cureus, began life in 2009 under the name PeerEMed and adopted its current name in December 2012. It is a web-based, open-access general medical journal known for an unusually fast review process and for publishing articles with pre-publication peer review followed by optional post-publication commentary, scored through its trademarked Scholarly Impact Quotient.
Its founding editors-in-chief are John R. Adler of Stanford University and Alexander Muacevic of LMU Munich, and since December 2022 it has been part of the Springer Nature group.
The journal has also drawn scrutiny: in 2025, Clarivate removed Cureus from its Master Journal List, ending its indexing in Web of Science, and it has carried out large retractions, including 56 papers in January 2024.
The next evidence step the review itself points to: randomized trials comparing mechanism-directed regimens head-to-head, which the authors say the current literature — dominated by cohorts — has not yet delivered.
References
- Effectiveness of Novel Therapeutic Alternatives for the Treatment of Carbapenem-Resistant Enterobacterales Infections: A Systematic Review and Meta-Analysis, Cureus (2026)
- Centers for Disease Control and Prevention, CRE as an urgent public-health threat
- World Health Organization, Bacterial Priority Pathogens List
- Shields et al., cohort of carbapenem-resistant K. pneumoniae bacteremia, University of Pittsburgh Medical Center
- Bassetti et al., CREDIBLE-CR phase 3 randomized trial of cefiderocol
