
A novel surgical approach called intermediate component separation (ICS) allows surgeons to repair medium-to-large incisional hernias without entering the peritoneal cavity or disrupting neurovascular bundles. The technique provides broad mesh coverage while preserving core abdominal wall anatomy for complex hernia patients.
New Surgical Method Reduces Risks for Massive Hernias
- What it is: A new surgical method to fix large hernias in the abdominal wall by placing a large supportive mesh between muscle layers without cutting into the main gut cavity.
- Why it matters: It reduces the risk of bowel injuries and visceral adhesions that often happen with older, more invasive hernia repairs.
- Who it’s for: Patients with massive, complex hernias—such as a 65-year-old male case study patient who developed a 16 cm by 25 cm defect following severe necrotizing pancreatitis.
Anatomical Innovations in Abdominal Reconstruction
Incisional hernias remain a major global health burden, driving a high demand for surgical intervention while imposing substantial financial strain on healthcare systems. Inadequate repair techniques often lead to high recurrence rates, chronic pain, and severe postoperative complications. Surgeon-dependent variables, particularly mesh dimensions and the anatomical plane selected for implantation, heavily influence these outcomes. Achieving an adequate mesh-to-defect area ratio (MDR) of 16 or greater significantly reduces ventral hernia recurrence by ensuring proper tension distribution and tissue contraction.
Traditional repair methods present distinct clinical limitations. The gold-standard retro-rectus (sublay) placement, popularized by Rives and Stoppa, minimizes wound morbidity but restricts transverse mesh width to roughly 10 to 12 cm. This makes it challenging to achieve sufficient mesh overlap in larger defects. Conversely, intraperitoneal onlay mesh (IPOM) placement positions the synthetic material directly inside the abdominal cavity, against the parietal peritoneum.
To bypass these anatomical bottlenecks, surgeons developed the intermediate component separation technique. By connecting the pre-rectus subfascial plane medially with the avascular intermuscular space between the external and internal oblique muscles laterally, ICS creates a continuous compartment capable of housing a 45 cm by 30 cm mesh. Crucially, the procedure avoids entry into the peritoneal cavity entirely, minimizing the risk of visceral adhesions while keeping the deep inferior epigastric vessels intact.
Surgical Execution in a Giant Incisional Hernia Case
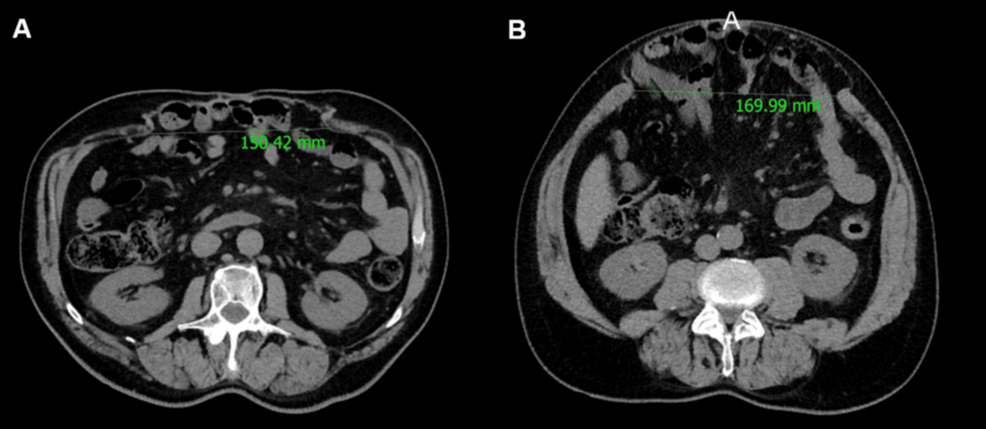
The clinical feasibility of the ICS technique was demonstrated in a 65-year-old male patient presenting with a giant midline incisional hernia categorized under the European Hernia Society classification as EHS M1-M3, W3, L25. Measuring 16 cm in width and 25 cm in length, the defect developed after multiple open necrosectomies and debridements for severe necrotizing pancreatitis. Given the extensive history of intra-abdominal inflammation, standard entry into the peritoneal cavity carried an exceptionally high risk of enterotomy and complications associated with extensive adhesiolysis.
Surgeons incised the anterior rectus sheath bilaterally, developing a subfascial plane between the sheath and the rectus abdominis muscle.
Dissection then proceeded laterally toward the EIT ambivium—the convergence zone of the external oblique, internal oblique, and transversus abdominis aponeuroses at the lateral margin of the anterior rectus sheath. Under direct visual guidance, the anterior rectus sheath was incised from within, 5 mm medial to the EIT ambivium. This precise step granted direct access to the avascular intermuscular plane between the external and internal oblique muscles without disrupting the two deeper layers of the lateral abdominal wall. The patient experienced an entirely uneventful 90-day postoperative follow-up.
| Hernia Repair Parameter | Traditional Retro-Rectus (Rives-Stoppa) | Intermediate Component Separation (ICS) |
|---|---|---|
| Peritoneal Cavity Entry | Frequently required or exposed | Avoided completely |
| Maximum Transverse Mesh Width | Strictly bounded at 10–12 cm | Accommodates meshes up to 30–45 cm |
| Neurovascular Injury Risk | Moderate to high in extensive lateral releases | Eliminated |
| Visceral Adhesion Risk | Present if posterior sheath is compromised | Minimized |
ICS Technique Requires Specialized Surgical Expertise
While the ICS technique offers a compartment-preserving alternative for complex ventral defects, it requires specialized surgical expertise in abdominal wall anatomy.
The successful deployment of intermediate component separation changes how surgeons manage massive abdominal wall defects. By marrying broad prosthetic coverage with strict compartment preservation, the technique addresses the historical compromise between achieving adequate tension distribution and courting severe visceral complications.
References
- First Description of Intermediate Component Separation: A Novel Compartment-Preserving Technique for Medium and Large Incisional Hernia Repair
- European Hernia Society (EHS)
