
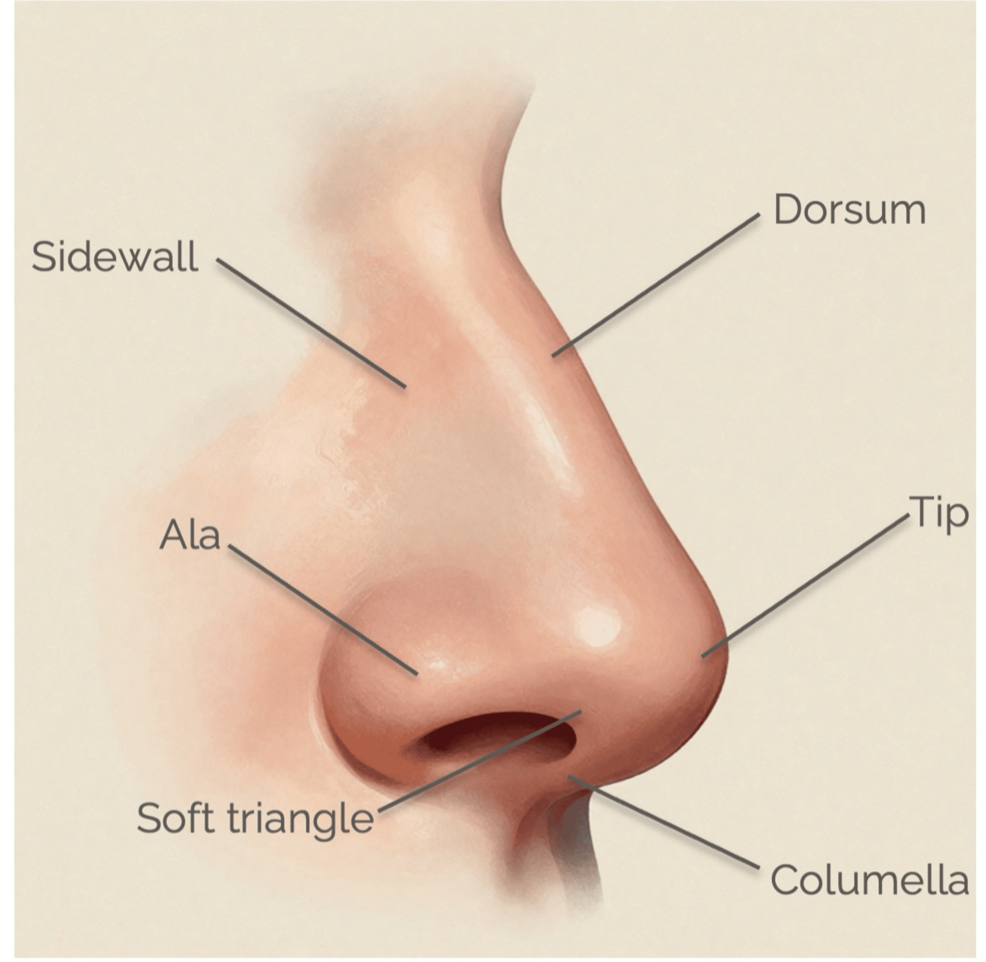
Nasal soft-tissue defects present complex challenges in facial reconstruction due to the nose’s intricate three-dimensional architecture, requiring simultaneous restoration of skin cover, contour, and airway function. According to a narrative review, managing acute traumatic defects demands distinct early decision-making protocols compared to planned oncologic procedures.
In Plain English: The Clinical Takeaway
- Layered Restoration: Full-thickness nasal injuries require simultaneous repair of the internal mucosal lining, the structural cartilage framework, and the external skin envelope.
- Preserving Native Tissue: Unlike elective cancer surgeries that routinely replace entire aesthetic subunits, acute trauma care prioritizes keeping viable native tissue to prevent unnecessary tissue loss.
- Timing Guided by Wounds: Definitive surgical repair depends entirely on the cleanliness and viability of the wound, meaning heavily contaminated or crush injuries require staged debridement before final reconstruction.
Anatomical Realignment and Tissue Salvage in Acute Trauma
The management of acute traumatic nasal injuries differs fundamentally from oncologic resections, which are executed under controlled surgical conditions. Traumatic defects often feature irregular wound margins, tissue contamination, uncertain tissue viability, and avulsion or amputation of nasal segments. Initial emergency department assessments must focus on patient stability, thorough wound irrigation, debridement, and exploration to uncover underlying skeletal or septal fractures.
Whenever local and systemic conditions permit, preserving viable native tissue remains the primary objective. In avulsion or amputation injuries, primary reattachment or layered anatomical realignment can successfully preserve native contours. When amputated segments are retrievable, composite grafting or microsurgical replantation represents a viable option dependent upon tissue composition and surgical expertise.
Applying the Aesthetic Subunit Framework to Traumatic Defects
Reconstructive planning historically relies on the aesthetic subunit concept, dividing the nose into distinct anatomical regions including the dorsum, sidewalls, tip, alae, soft triangles, and columella. In elective oncology cases, standard protocol dictates that if a defect involves more than 50 percent of an aesthetic subunit, the remaining normal tissue should be excised and the entire unit reconstructed.
The narrative review highlights that this paradigm should not be applied rigidly to acute trauma. Discarding healthy native skin solely to satisfy the 50 percent rule is discouraged when viable tissue can be retained to preserve nasal contour and airway function. Partial-subunit reconstruction is frequently appropriate for acute injuries, provided skin thickness, color, and texture are factored into donor tissue selection.
| Defect Characteristic | Primary Clinical Consideration | Standard Reconstructive Approach |
|---|---|---|
| Small, Superficial Defects | Concave surface areas where contraction is less noticeable | Secondary intention healing, primary closure, or full-thickness skin grafting |
| Larger Skin-Only Defects | Greater tissue mobility on the dorsum and sidewalls | Local or regional flap reconstruction |
| Full-Thickness Composite Defects | Involvement of cartilage, internal lining, and external envelope | Simultaneous structural support, mucosal restoration, and skin coverage |
Timing Determinants and Staged Management Strategies
The timing of definitive reconstruction is dictated by wound conditions rather than sheer defect dimensions. Early definitive repair is indicated when patients are clinically stable, wounds are thoroughly irrigated and debrided, and contamination is controlled. Clean, sharply defined lacerations and selected bite injuries managed with meticulous debridement are typically suited for early intervention.
Conversely, high-energy ballistic injuries, severe crush wounds, and heavily contaminated environments produce evolving zones of tissue necrosis. These complex presentations necessitate initial debridement, temporary wound care, and delayed reassessment. Staged management protocols allow clinicians to sequentially restore the soft-tissue envelope, skeletal framework, and internal nasal architecture without risking flap necrosis or chronic infection.
Contraindications & When to Consult a Doctor
Immediate definitive soft-tissue reconstruction is contraindicated in wounds exhibiting uncontrolled bacterial contamination, active infection, or unverified tissue viability. Patients presenting with progressive tissue ischemia, expanding septal hematomas, or compromised nasal airways require immediate otolaryngology or plastic surgery consultation prior to any skin-level repair. Any acute facial trauma accompanied by clear cerebrospinal fluid rhinorrhea, unstable midface fractures, or signs of systemic shock necessitates emergency stabilization before elective or semi-urgent reconstructive planning.
The Future Trajectory of Acute Nasal Reconstruction
While established principles from the broader reconstructive literature guide current interventions, trauma-specific literature remains heavily weighted toward individual case reports and small case series. The synthesis of a trauma-oriented, subunit-based algorithm provides a practical framework for clinicians managing acute facial injuries. Future clinical investigations must focus on establishing standardized, prospective guidelines to optimize functional and aesthetic outcomes in emergency facial reconstruction.
References
- Reconstructive Strategies in Acute Nasal Soft-Tissue Trauma: A Narrative Review and Subunit-Based Algorithm.
- Burget and Menick [12].
- Ghosh SK. One-stage reconstruction of a complex facial avulsion injury. J Plast Reconstr Aesthet Surg.
