
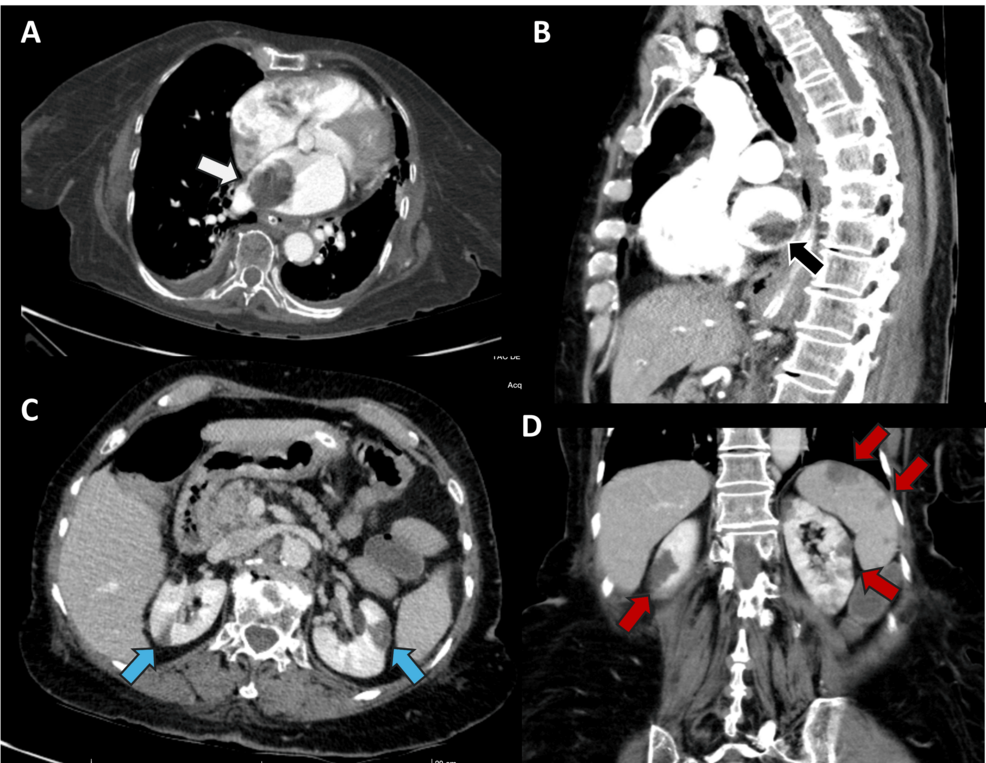
An 86-year-old hypertensive woman experienced multiterritorial systemic embolization across five vascular beds following an initial misdiagnosis of left atrial myxoma as a thrombus on computed tomography, as detailed in a case report published by Cureus.
The patient presented to the emergency department after a fall from standing height triggered by a syncopal episode, which is a temporary loss of consciousness caused by a drop in blood pressure.
Over a subsequent two-week hospital stay, she developed embolic injury in the brain, both kidneys, the spleen, the ileocolic mesenteric territory, and both lower limbs. Contrast-enhanced computed tomography initially suggested an intracavitary thrombus, which is a blood clot formed within a heart chamber, set against a background of electrocardiographically documented atrial fibrillation and left atrial enlargement.
Transthoracic echocardiography, a non-invasive ultrasound of the heart, later characterized a mobile 50 by 32 millimeter mass suggestive of myxoma, a primary non-cancerous heart tumor. Histopathologic examination of the resected mass and material retrieved at embolectomy ultimately confirmed cardiac myxoma. The patient later died of septic shock secondary to anastomotic dehiscence and fecal peritonitis.
Differentiating Tumor from Blood Clots
- Atrial Myxoma: A rare, benign primary heart tumor that can mimic a standard blood clot on initial scans, shedding tissue fragments that cause blockages throughout the body.
- Systemic Embolization: Occurs when a mass or clot breaks loose from the heart and travels through the bloodstream to obstruct blood flow in distant organs like the brain, kidneys, and limbs.
- Multimodality Imaging: The clinical necessity of combining computed tomography, magnetic resonance imaging, and echocardiography to correctly differentiate between a tumor and a blood clot when multiple organ infarcts appear simultaneously.
Identifying Cardiac Myxoma on Imaging
Primary cardiac tumors are exceedingly rare, with a reported prevalence of 0.001% to 0.03% in autopsy series. Since the World Health Organization’s 2021 classification designated papillary fibroelastoma as the most frequent, cardiac myxoma now holds the position of the second most common benign primary cardiac tumor among adults. Myxomas typically arise in the left atrium near the fossa ovalis and predominate in women between the third and sixth decades of life.
During the patient’s evaluation, a contrast-enhanced computed tomography scan of the chest and abdomen showed an oval intraluminal mass in the left atrium measuring 45 by 30 millimeters. Radiologists initially interpreted the mass as an intracavitary thrombus because the patient suffered from atrial fibrillation. Wedge-shaped hypodense areas in both kidneys and the spleen confirmed established infarcts, which are areas of dead tissue resulting from a failure of blood supply.
Before echocardiography could be performed, the patient developed sudden left hemiparesis, mild dysarthria, and left facial palsy. Brain magnetic resonance imaging demonstrated multiple acute lesions with restricted diffusion in both frontoparietal regions, the right occipital, and periatrial regions. The involvement of noncontiguous territories strongly supported an embolic mechanism and pointed toward a proximal cardiac source.
| Imaging Modality | Initial Findings | Retrospective/Corrected Interpretation |
|---|---|---|
| Computed Tomography (CT) | Interpreted as left atrial thrombus | Size, lobulated contour, and heterogeneous enhancement favored myxoma |
| Transthoracic Echocardiography | Not initially performed prior to stroke | Identified mobile, heterogeneous 50 x 32 mm mass attached to interatrial septum |
| Brain MRI | Acute lesions in noncontiguous territories | Confirmed multi-infarct cardioembolic stroke pattern |
Multiterritorial Embolic Progression and Surgical Intervention
Transthoracic echocardiography eventually revealed a mobile, heterogeneous 50 by 32 millimeter mass in the left atrium attached to the interatrial septum. Almost simultaneously, the patient lost bilateral pulses from the popliteal level distally, presenting with cold extremities and sensory deficits. Computed tomography angiography of the lower limbs confirmed acute embolic occlusion of the popliteal segments and tibioperoneal trunks bilaterally.
Abdominal imaging also displayed segmental hypodensity with absent mucosal enhancement of the cecum and distal ileum, indicating segmental ischemia in the ileocolic territory. Exploratory laparotomy revealed transmural necrosis of the cecum and ileocecal valve with thrombosed ileocolic vessels. Surgeons performed a partial right colectomy with distal ileostomy alongside bilateral lower limb embolectomy, retrieving yellowish, friable, and gelatinous material confirmed as myxomatous tissue.
Seeking Emergency Medical Evaluation
Intravenous thrombolysis, a medication-based clot-busting treatment, is strictly contraindicated in patients with active gastrointestinal bleeding and ongoing therapeutic anticoagulation. Mechanical thrombectomy requires large-vessel occlusion visible on neurovascular imaging. Patients experiencing sudden neurological deficits, unexplained multi-organ infarcts, or peripheral vascular ischemia must seek immediate emergency medical evaluation.
Clinicians must maintain a high index of suspicion for cardiac myxoma when an intracavitary filling defect coexists with systemic infarcts across multiple vascular beds, overriding assumptions of simple thrombus.
The patient died of septic shock following surgical complications, illustrating the severe morbidity associated with delayed diagnosis in elderly patients presenting with atypical cardiac tumors and multiorgan embolization.
References
- Rueda Góez S, Zapata Naranjo M, Suárez Poveda T, et al. Left Atrial Myxoma Mimicking Thrombus on Computed Tomography With Multiterritorial Systemic Embolization in an Elderly Woman: A Case Report. Cureus. 2026;18(11):e119666.
- World Health Organization. WHO Classification of Tumours of the Heart. 5th ed. International Agency for Research on Cancer; 2021.
- Medicine (Baltimore). 2001;80(3):159-172.
