
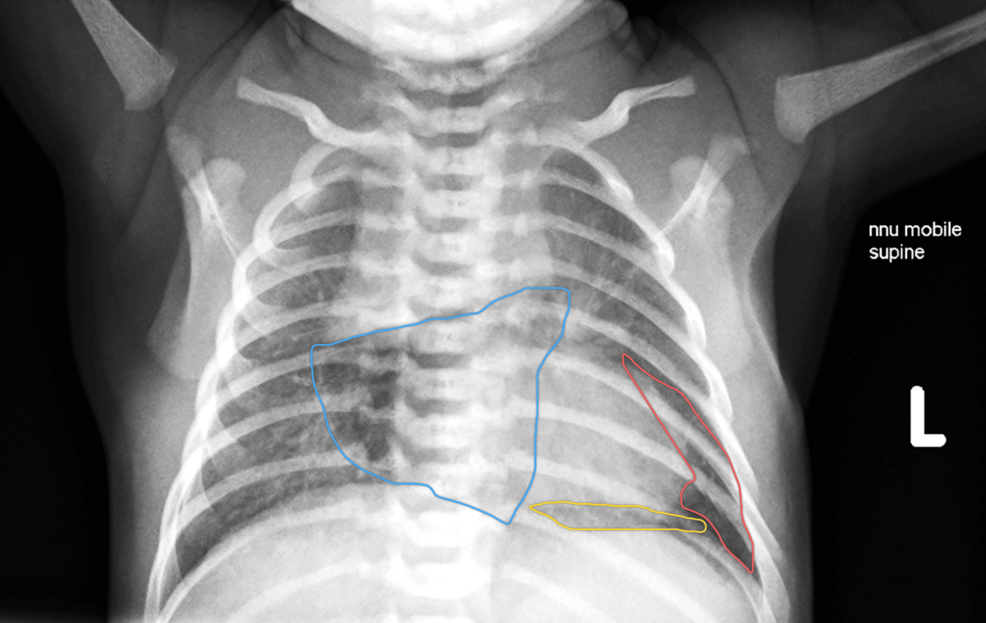
A term neonate delivered via category 2 caesarean section developed concurrent pneumothorax, pneumomediastinum, and pneumopericardium after receiving brief positive end-expiratory pressure support for transient respiratory distress, Cureus reported. Diagnosed incidentally on day 4 of life via chest radiograph during an evaluation for persistent tachypnoea, all three air leaks resolved conservatively without invasive intervention.
In Plain English: The Clinical Takeaway
- Multi-compartment air leak syndrome: A condition where air escapes the lungs and collects in multiple surrounding chest cavities simultaneously, such as the pleural space and the pericardium.
- Positive end-expiratory pressure (PEEP): A breathing support method that keeps airways open using mild air pressure, which carries a known risk of causing iatrogenic pulmonary air leak in newborns.
- Conservative management: Treating a condition safely through close observation, vital sign monitoring, and serial X-rays rather than performing invasive surgery or inserting chest drainage tubes.
Diagnostic Challenges in Newborns Presenting with Persistent Tachypnoea
Respiratory distress remains one of the presentations in the neonatal intensive care unit. Transient tachypnoea of the newborn (TTN)—caused by delayed clearance of fetal lung fluid—frequently accounts for these early complications. In this case, a term infant born at 39 weeks and 2 days of gestation experienced early cyanosis at three minutes of life. Medical staff administered positive end-expiratory pressure (PEEP) at 5 cmH2O for roughly one hour to assist cardiorespiratory transition.
Although the infant stabilized, persistent tachypnoea continued across the following days, with respiratory rates ranging from 44 to 79 breaths per minute. Because the mother experienced prolonged rupture of membranes lasting 34 hours and developed intrapartum pyrexia of 37.8°C, clinical teams initially suspected neonatal sepsis. A partial septic screen was initiated on day 3 of life. Laboratory markers showed a C-reactive protein (CRP) level of 4.6 mg/L, and blood cultures showed no bacterial growth at five days.
Radiographic Confirmation of Multi-Compartment Barotrauma
Because rapid breathing persisted into day 4 of life, clinicians ordered a diagnostic chest radiograph alongside a repeat capillary blood gas and an updated CRP measurement, which dropped to 1.5 mg/L. The imaging unexpectedly revealed a complex multi-compartment air leak: a left anterior pneumothorax, pneumomediastinum, and pneumopericardium.
The underlying mechanism involves barotrauma and alveolar overdistension. Positive pressure ventilation in neonates carries an inherent risk of iatrogenic pulmonary air leak. Pneumopericardium is the rarest of the three, but is of clinical significance, as even a modest volume of pericardial air can precipitate tamponade in the neonatal heart.
Contraindications & When to Consult a Doctor
While this specific patient recovered safely via conservative observation, healthcare providers must remain vigilant for clinical decompensation. No invasive intervention (needle decompression, chest drain, or pericardiocentesis) was required at any point.
Clinical Resolution and Outpatient Follow-Up
Empirical intravenous antibiotics administered on day 4 were discontinued after 48 hours as blood cultures remained negative and inflammatory markers declined. Throughout the hospitalization, the infant remained clinically stable without requiring further respiratory support. Serial chest radiography demonstrated progressive improvement, with complete radiological resolution confirmed at follow-up.
