
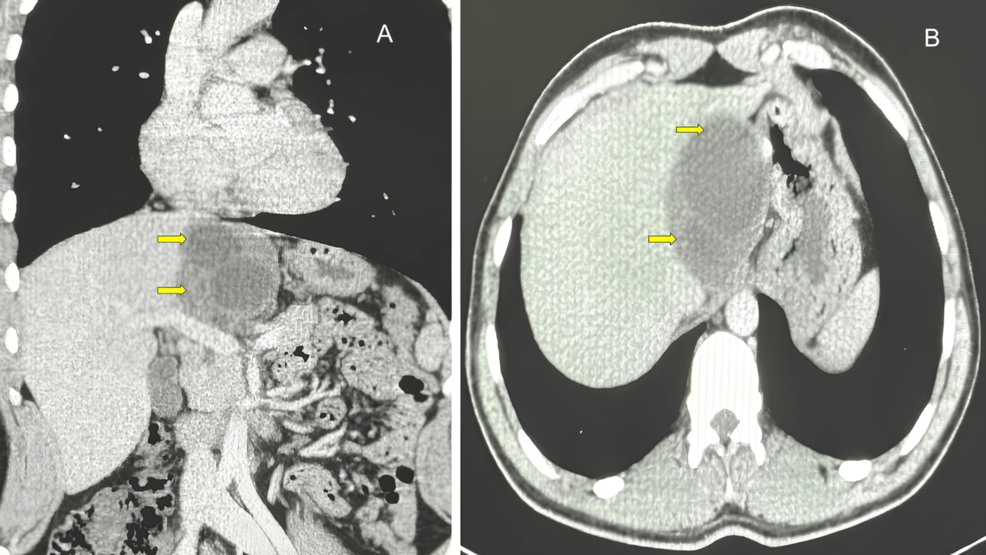
A 32-year-old man presented with a primary peritoneal hydatid cyst adjacent to the hepatic hilum, a rare manifestation of the zoonotic infection caused by Echinococcus granulosus. Reported in Cureus, the case demonstrates how extrahepatic peritoneal lesions can mimic exophytic liver masses on preoperative computed tomography.
Hydatid disease remains a major public health concern in endemic pastoral regions. While the liver and lungs represent the vast majority of primary infection sites, isolated peritoneal involvement accounts for roughly 2% to 13% of abdominal presentations. In this patient, the lesion’s close anatomical relationship to the left hepatic lobe and major vascular structures created a distinct diagnostic hurdle that required careful surgical planning and postoperative medical management.
In Plain English: The Clinical Takeaway
- What happened: A patient developed a parasitic cyst inside the lining of his abdominal cavity (the peritoneum) right near his liver, which initially looked like it was growing out of the liver itself.
- Why it matters: Because the cyst sat directly against vital blood vessels like the inferior vena cava, doctors had to modify their surgical approach to avoid dangerous bleeding while fully clearing the infection.
- The treatment path: Surgeons removed the protruding dome of the cyst (a partial pericystectomy) and prescribed a three-month course of the anti-parasitic drug albendazole to prevent recurrence.
Anatomical Mimicry and Diagnostic Challenges at the Hepatic Hilum
The patient presented to clinicians with a one-year history of intermittent, dull abdominal pain localized to the right upper quadrant and epigastrium. Initial laboratory findings—including complete blood counts, liver enzymes, and C-reactive protein levels—all fell within normal limits. However, contrast-enhanced computed tomography revealed a large 100 by 80-millimeter multiloculated cystic lesion characterized by multiple daughter cysts, corresponding to a Gharbi type 3 classification.
Hydatid Cyst Rupture (caused by Echinococcus granulosus infection, leading to Anaphylactic Shock).Key Clinical Factors Hydatid Disease / Cystic Echinococcosis: Caused by the larval stage of the tapeworm Echinococcus granulosus, which commonly forms fluid-filled cysts in the…
The mass exerted a compressive effect on the left hepatic lobe, the lesser curvature of the stomach, the left portal vein, and the inferior vena cava. Yet, imaging failed to show any definitive radiological signs of vascular invasion. It was only during exploratory laparotomy via a right subcostal incision that surgeons identified a clear cleavage plane between the mass and the liver parenchyma. This intraoperative finding confirmed that the cyst originated entirely from the peritoneum, leaving the liver tissue itself uninfected.
The exact biological mechanism governing primary peritoneal infection remains clinically unclear, with multiple competing hypotheses existing in medical literature. Some researchers suggest that larval dissemination occurs via systemic or lymphatic pathways, while others propose the silent migration or microscopic rupture of undetected visceral cysts without compromising surrounding membranes.
Surgical Strategy and Pharmacological Intervention Near Major Vessels
Complete surgical excision stands as the primary objective in managing abdominal hydatid disease to eliminate the risk of recurrence. However, performing a total pericystectomy carries severe procedural hazards when a lesion adheres tightly to vital structures like the hepatic hilum and major abdominal blood vessels.

To balance complete evacuation with vascular safety, the surgical team performed a partial pericystectomy. After carefully aspirating the internal contents—which yielded numerous daughter cysts and germinal membranes—the residual cavity was irrigated with regular saline and hydrogen peroxide to sterilize the site against secondary spillage. Two closed-suction drains were placed in the subhepatic space and residual cavity before closure.
Following a successful operation, the patient recovered without complications and was discharged on the fifth postoperative day. Medical therapy with albendazole, administered at 400 milligrams twice daily for three months, was initiated to eradicate any microscopic residual parasitic tissue.
Contraindications & When to Consult a Doctor
Patients diagnosed with cystic echinococcosis must avoid unmonitored self-management or premature cessation of anti-parasitic medications like albendazole. Albendazole therapy is contraindicated in patients with known hypersensitivity to benzimidazole derivatives and requires strict monitoring of liver function tests and blood counts due to potential hepatotoxicity and bone marrow suppression. Furthermore, pregnant patients must consult infectious disease specialists immediately, as albendazole carries teratogenic risks during the first trimester.
Anyone residing in or traveling through endemic pastoral regions who experiences persistent, unexplained right upper quadrant abdominal pain, palpable mass sensations, or progressive abdominal distension should seek prompt medical evaluation. Advanced cross-sectional imaging, such as contrast-enhanced computed tomography, is necessary to differentiate primary peritoneal hydatid disease from mesenteric cysts, enteric duplication cysts, and benign cystic neoplasms.
References
- Cureus: Primary Peritoneal Hydatid Cyst Adjacent to the Hepatic Hilum Mimicking a Hepatic Hydatid Cyst: A Rare Diagnostic and Surgical Challenge. PubMed
- World Journal of Surgery: Surgical Treatment of Hydatid Disease. SpringerLink
- PMC
Disclaimer: This article is for informational purposes only and does not substitute for professional medical advice, diagnosis, or treatment.
