
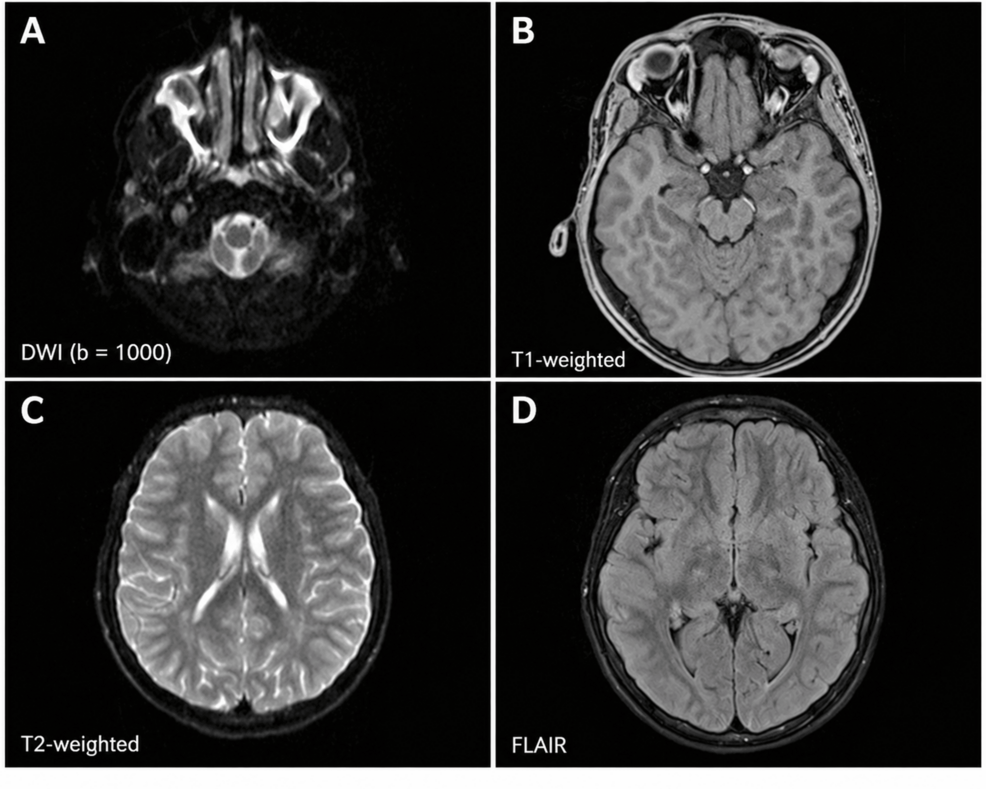
A new case report details an acute-onset episode of bipolar I disorder with severe psychotic features in a 15-year-old adolescent who lacked any recognizable prodromal symptoms. The patient, previously treated long-term for attention-deficit/hyperactivity disorder (ADHD), experienced rapid psychiatric decompensation following a reduction in his risperidone dosage.
Risperidone Reduction Triggers Acute Bipolar Psychosis
- Acute-Onset Bipolar Psychosis: Unlike typical presentations that feature gradual behavioral changes, this adolescent developed severe mania and psychosis without warning.
- Medication Transitions: Reducing the dose of the atypical antipsychotic risperidone triggered an immediate recurrence of acute psychiatric symptoms.
- Differential Diagnosis: Extensive neurological and infectious evaluations, including brain MRI and lumbar punctures, ruled out organic causes such as autoimmune encephalitis and Lyme neuroborreliosis.
Patient Presents with Behavioral Disorganization and Psychosis
The patient presented to the emergency department with marked behavioral disorganization, recurrent disrobing, fecal smearing, echolalia, and repetitive pacing. One month prior, he completed a three-week psychiatric hospitalization for new-onset confusion and decreased need for sleep. During that initial stay, his dexmethylphenidate extended-release (Focalin XR) 10 mg daily—a stimulant he had taken for nine years for ADHD—was discontinued.
Clinicians initiated risperidone at 1 mg daily, titrating it to 1 mg twice daily. This intervention yielded temporary stabilization. However, approximately two weeks after discharge, an outpatient provider reduced the risperidone dosage due to sedation and concentration difficulties. Within a week, severe manic and psychotic symptoms returned, prompting readmission.
Given the abrupt nature of the presentation, hospitalists launched an exhaustive medical evaluation to exclude organic etiologies. Neurological testing revealed below-age cognitive functioning that contrasted sharply with his baseline academic success in accelerated classes. A brain magnetic resonance imaging (MRI) scan with contrast and an electroencephalogram (EEG) returned normal results.
Cerebrospinal fluid (CSF) analysis via lumbar puncture demonstrated a mildly elevated white blood cell count with a predominance of lymphocytes (46 total nucleated cells/µL, 96 percent lymphocytes), but negative oligoclonal bands and negative anti-N-methyl-D-aspartate receptor (anti-NMDAR) antibodies. Initial serum testing returned a positive Lyme serology, but infectious disease specialists confirmed it to be a false positive after repeat testing. Comprehensive autoimmune encephalitis panels sent to the Mayo Clinic were entirely negative.
Treatment Course and Antipsychotic Optimization
While diagnostic tests ruled out infectious and autoimmune encephalitis, the patient received no antimicrobial therapy. Clinicians restarted his risperidone regimen, initially at 1 mg nightly, while avoiding guanfacine due to prior sedative side effects. Because clinical response remained insufficient, the medical team titrated the antipsychotic dose to 1 mg in the morning and 2 mg nightly.
Following this upward titration, the patient demonstrated progressive clinical stabilization over the course of one week. Echolalia diminished, spatial orientation improved, and paranoia regarding potential harm from others resolved. This stabilization allowed him to actively participate in unit programming, including art therapy and psychiatric occupational therapy, prior to a successful discharge.
| CSF Parameter | Patient Result | Reference Range |
|---|---|---|
| Glucose (mg/dL) | 54 | 40–70 |
| Protein (mg/dL) | 44 | 15–45 |
| White blood cells (cells/µL) | 5 | 0–5 |
| Lymphocytes (%) | 96 | N/A |
| NMDAR Antibody | < 1:1 | < 1:1 (Negative) |
Differential Diagnosis Challenges in Pediatric Bipolar Disorder
Early-onset bipolar disorder, defined as onset before the age of 18, frequently complicates psychiatric care due to high rates of comorbidity. Attention-deficit/hyperactivity disorder shares a lifetime prevalence of 61.2% among pediatric patients with bipolar I disorder. Because ADHD often precedes bipolar diagnoses, many adolescents maintain long histories of stimulant treatment.
Retrospective clinical data indicate an association between prior stimulant treatment and an earlier age of bipolar disorder onset. However, researchers emphasize that these datasets cannot definitively distinguish whether stimulants directly influence disease trajectory or merely unmask an underlying vulnerability in patients with shared genetic predispositions. In this case, the patient’s long-term stability on dexmethylphenidate for nine years, coupled with symptom recurrence long after stimulant cessation, suggests that stimulant exposure alone does not account for the acute presentation.
Abrupt Antipsychotic Dose Reductions Risk Clinical Relapse
Abrupt dose reductions of atypical antipsychotics such as risperidone carry a documented risk of clinical relapse in patients recovering from acute mania and psychosis.
References
- Cureus: Acute-Onset Bipolar Psychosis in an Adolescent Without Prodromal Symptoms: A Case Report.
- DelBello, M.P., et al.: Prior stimulant treatment and age of onset in adolescent bipolar disorder.
